Antibiotics, child microbiota and long-term health effects

Antibiotic therapy is a cornerstone of the modern therapeutic arsenal but it displays a number of side effects, in particular a detrimental action on the human microbiota and the creation of a reservoir of antibiotic resistance genes (resistome). While the resistome is still under-investigated, the impact of dysbiosis caused by antibiotics is increasingly understood through scientific research, particularly in children. Let’s explain further.

The gut microbiota Can fecal transplantation restore the microbiota of Caesarean-born infants? Microbiota, breastfeeding and early puberty Peripartum prophylactic antibiotic therapy decreases bifidobacterium levels in breast milk
Santé-infantile-bandeau1

Scientific literature has confirmed that perinatal exposure to antibiotics disrupts the establishment of the intestinal microbiota and has potential consequences on the child’s health throughout his/her growth.

GUT MICROBIOTA HOMEOSTASIS AND HEALTH

The intestinal microbiota is a complex and diverse ecosystem composed of microorganisms coexisting with their host in a collaborative relationship. This microbiota plays an important part in the proper functioning of the digestive system, but also in metabolic and immune homeostasis. Its particularities made it a key component in human health and a significant research field aiming at exploring the consequences of antibiotics-induced dysbioses. A literature review provided a better understanding of the effects of antibiotics on the intra- and postpartum development of the intestinal microbiota in children.1 During that period, exposure to antibiotics can take many different forms: mother treatment during pregnancy, cesarean delivery, postpartum treatment (especially in premature children), and even breastfeeding since antibiotics can change breast milk microbiota and/or be transmitted to the child.

THE GUT RESISTOME: AN AVENUE WORTH EXPLORING

  • The resistome designates all microbiota genes potentially coding for antibiotic resistance.
  • The growth of this gene reservoir has hardly been studied, but early acquired resistance could be related to the exposure to maternal and environmental microbes during and after birth.
  • The role of the resistome in the composition of the intestinal microbiota and its impact on individual or collective human health have yet to be defined.

HOST-MICROBIOTA INTERACTIONS: A SMALL WINDOW OF OPPORTUNITY

Several publications emphasize the importance of early intestinal colonization and the existence of a perinatal window of opportunity during which microbial exposure defines the “basic programming“ of the future microbiota, and consequently the long-term health of the child. The beginning and duration of this window of opportunity has not yet been documented and represents an active field of research. It is apparently short, however, and encourages a limited use of antibiotics to restrict adverse effects. Research shows that not all antibiotic drugs have the same effect on the microbiota and that individual sensitivity plays an important role in the impact on health. That being said, most children in developed countries are exposed to them during their first year of life. This observation calls for research to dig deeper into early dysbiosis caused by antibiotic therapies in order to better manage the associated metabolic and autoimmune disorders.

ANTIBIOTICS ARE PERINATAL DETERMINANTS

  • Newborns are colonized at a very early stage in life by aerobic bacteria and facultative anaerobic bacteria, and later, by strictly anaerobic bacteria from the maternal microbiota and the environment.
  • Antibiotics, as well as mode of delivery, gestational age or feeding method, have an impact on this colonization.
  • An antibiotic treatment of over 3 days is a risk factor for colonization by antibiotic resistant enteric bacteria, especially if a broad-spectrum drug is used.
[Source] : Marteau M, Doré J. Gut microbiota, a full-fledged organ. March 2017. John Libbey Eurotext
Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old sources


Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Pediatrics

Probiotics: what are the benefits?

Probiotics are intended to modulate the intestinal microbiota. However, their efficacy has yet to be defined, even though available data encourage continued research to identify the most effective strains in the treatment of FGIDs.

The gut microbiota What are the long-term effects of antibiotics on the gut microbiota? Role of the microbiota in gut-brain communication Antibiotic exposure during first six years of life disrupts gut microbiota and impairs child growth

ACTION IN IBS

The definition of probiotics, namely “a living microorganism which, when administered in sufficient quantity, exerts a beneficial effect on the health of the host”,20 refers, in practice, to three large families used in the health and food industries for over-the-counter products: lactobacillus, bifidobacterium and yeasts. The effect of probiotics on FGID symptoms has been the subject of a limited number of publications and it is difficult to identify commensal bacteria of particular value in FGIDs.21 In IBS, a positive effect is however observed; and results in animals suggest that the efficacy of probiotics is linked to effects that impact the pathways acting on visceral motility and hypersensitivity, inflammation and local immune activity, the integrity of the intestinal barrier, the composition of the microbiota and the gut-brain axis.

A PROBIOTIC FOR EACH SYMPTOM

The controversy remains regarding rhythm, urgency, rumbling, and the feeling of incomplete evacuation: inefficacy of probiotics in some studies, partial efficacy in others (no action on rhythm). However, in infantile colic, the use of probiotics based on bifidobacteria could help restore the balance of the gastrointestinal microbiota and exert a beneficial effect on immune defenses. Some studies have shown that supplementation with Lactobacillus reuteri could reduce colic.22, 23 Other microorganisms such as Bifidobacterium breve, a dominant species found in children fed on mother’s milk, might also represent approaches to be investigated.24 In children suffering from IBS, L. rhamnosus and L. reuteri would seem to reduce the frequency and severity of abdominal pain.25, 26 A meta-analysis confirms the efficacy of probiotics in adults on symptoms associated with IBS (more for IBS-D than IBS-C), without naming any strain in particular.27 The World Gastroenterology Organisation recommends the use of B. infantis to reduce abdominal pain, bloating, and normalize bowel movements.28 Functional constipation is thought to be improved by means of an Artichoke-L paracasei combination.29 These observations open the way to detailed research into intake of synbiotics (combination of pre- and probiotics).

Sources

20 FAO/OMS, Joint Food and Agriculture Organization of the United Nations/ World Health Organization. Working Group. Report on drafting  guidelines for the evaluation of probiotics in food, 2002.

21 Lee HJ, Choi JK, Ryu HS, et al. Therapeutic Modulation of Gut Microbiota in Functional Bowel Disorders. J Neurogastroenterol Motil. 2017;23(1):9-19.

22 Indrio F, Di Mauro A, Riezzo G, et al. Prophylactic use of a probiotic in the prevention of colic, regurgitation, and functional constipation: a randomized clinical trial. JAMA Pediatr. 2014;168(3):228-233.

23 Savino F, Cordisco L, Tarasco V, et al. Lactobacillus reuteri DSM 17938 in infantile colic: a randomized, double-blind, placebo-controlled trial. Pediatrics. 2010;126(3):e526-e533.

24 Giglione E, Prodam F, Bellone S, et al. The Association of Bifidobacterium breve BR03 and B632 is Effective to Prevent Colics in Bottle-fed Infants: A Pilot, Controlled, Randomized, and Double-Blind Study. J Clin Gastroenterol. 2016;50 Suppl 2, Proceedings from the 8th Probiotics, Prebiotics & New Foods for Microbiota and Human Health meeting held in Rome, Italy on September 13-15, 2015:S164-S167.

25 Francavilla R, Miniello V, Magistà AM, et al. A randomized controlled trial of Lactobacillus GG in children with functional abdominal pain. Pediatrics. 2010;126(6):e1445-e1452.

26 Jadrešin O, Hojsak I, Mišak Z, et al. Lactobacillus reuteri DSM 17938 in the Treatment of Functional Abdominal Pain in Children: RCT Study. J Pediatr Gastroenterol Nutr. 2017;64(6):925-929.

27 Ford AC, Quigley EM, Lacy BE, et al. Efficacy of prebiotics, probiotics, and synbiotics in irritable bowel syndrome and chronic idiopathic constipation: systematic review and meta-analysis. Am J Gastroenterol. 2014;109(10):1547-1562.

28 WGO. World Gastroenterology Organisation Global Guidelines Irritable Bowel Syndrome: a Global Perspective

29 Riezzo G, Orlando A, D'Attoma B, et al. Randomised clinical trial: efficacy of Lactobacillus paracasei-enriched artichokes in the treatment of patients with functional constipation--a double-blind, controlled, crossover study. Aliment Pharmacol Ther. 2012;35(4):441-450.

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old sources


Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Pediatrics Gastroenterology

Dr. Marc Bellaiche: Managing FGIDs in children

Dr. Marc Bellaiche is a Pediatric Gastroenterologist at the Teaching Hospital Robert Debré for Mothers and Children (Paris, France). His expertise on FGIDs in children help us underline the diagnostic complexity and raise avenues for treating the disorders under investigation (targeted pro and pre-biotics), especially in the first two years of life.

The gut microbiota What are the long-term effects of antibiotics on the gut microbiota? Role of the microbiota in gut-brain communication Antibiotic exposure during first six years of life disrupts gut microbiota and impairs child growth

MANAGING FGIDs IN CHILDREN

What diagnostic difficulties do health professionals face?

As a reminder, Rome IV criteria include seven broad types of symptoms in newborns: regurgitation, cyclic vomiting, rumination, functional diarrhea, functional constipation, dyschezia, and colic (which is the most frequent FGID between 1 and 4 months of age). All health professionals are aware of the impact of FGIDs on the welfare of children and that of their parents, but general practitioners are less informed regarding Rome IV classification. Summarizing, clarifying, and spreading the criteria from the Rome Foundation would make it easier to implement current diagnostic tools, especially regarding treatment (be it medical or medico-psychological) of young children. After the age of two, childhood FGIDs look more like that of adults and are better addressed by practitioners.

Has the increasing awareness of the intestinal microbiota changed the situation?

I believe so. For instance, the definition of infant colic has been widened: etiological hypotheses are now based on the composition of the intestinal microbiota and not exclusively on standard clinical data. But treatment for FGDIs remains complicated in young children: there is more often a combination of disorders rather than a single one, as shown by a recent cohort study of 2,700 newborn children.30 Abundance of disorders explains the distress of some parents and increases difficulties to establish a diagnosis. For physicians, it is key to systematically refer to Rome IV criteria.

What are the priority therapeutic areas?

Beyond pain management, dysbiosis regulation with probiotics, is a promising therapeutic avenue. Swedish researchers were the first to work on the addition of specific strains of Lactobacillus (L. reuteri) and several studies and meta-analyses agree that these lactobacilli have proven their efficacy. According to a recent clinical study, the combination of two strains of Bifidobacterium breve could present a potential interest and decrease duration of crying in newborns with colic and fed with formula milk. Another novel concept: formulas that combine bifidogenic prebiotics (fructo-oligosaccharids and galacto-oligosaccharides) and that seem to reduce the duration of crying

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old sources


Old content type
pro_dossiers_article
Hide image
Off
Expert opinion Pediatrics Gastroenterology

FODMAP-free diet: not for all patients

Its use remains questionable in FGIDs, but a possible correlation between bacterial populations and response to the FODMAP-free diet could help refine the therapeutic choice.18, 19

The gut microbiota What are the long-term effects of antibiotics on the gut microbiota? Role of the microbiota in gut-brain communication Antibiotic exposure during first six years of life disrupts gut microbiota and impairs child growth

Healthy foods. Assorted selection of foods that are considered healthy.

TREATMENT OF IBS

The FODMAP-free diet (Fermentable Oligosaccharides Disaccharides Monosaccharides and Polyols) seems to represent an appropriate therapeutic response to IBS. The incriminated foods in fact cause intestinal disruption when they are fermented by bacteria via the production of gas and shortchain fatty acids. Restricting their intake provides benefits that are confirmed by the literature, but which must be weighed against potential negative effects to confirm the value of this type of diet as a first- line therapeutic option. The absence of FODMAPs can in fact cause eating disorders, deficiencies and biological disruption, directly or following dysbiosis of the intestinal microbiota. They should also not be used as a diagnostic test for IBS in place of recognized symptomatic criteria (those of Rome IV), note the experts, who also recall the importance of the gradual reintroduction of excluded foods, after checking that the organism will tolerate them.

THERAPEUTIC EFFICACY AND BACTERIAL PROFILE

A FODMAP-free diet could therefore be appropriate for some types of disorders or individuals, but not for others. This research area has been explored by a Norwegian team, who compared the composition of the intestinal microbiota of IBS patients with response to treatment. In this study, a patient was judged responsive if they showed a reduction of symptoms of at least 50% at 4 weeks on an IBS-SSS score. Out of 61 subjects, 32 (29 women, 3 men) were considered as respondents and 29 (25 women, 4 men) as non-respondents. The analysis of 54 bacterial markers by means of a specific test demonstrated significant differences between the two groups for 10 of these markers. From the data collected, a response index (RI) graduated from 0 to 10 and based on the median values of 10 bacterial markers of the responsive patients was created. Result: subjects with an RI higher than 3 were five times more likely to respond to treatment. A possible innovative therapeutic approach for the treatment of FGIDs.

AN ALTERNATIVE THERAPY, AMONG OTHERS

These reservations have led to the study of other non-pharmacological alternatives in FGIDs (hypnotherapy, gluten-free diet etc..). The literature tends to demonstrate that the conventional dietary advice given by health professionals provides less benefit: list of products to be avoided (fatty or spicy foods, coffee, alcohol, onions…) and eating habits to be adopted (eating at regular intervals, in reasonable quantities, chewing thoroughly…). On the contrary, hypnotherapy might offer the same physiological advantages as the low-FODMAP diet and a better psychological impact in patients suffering from IBS. Regarding the gluten-free diet, there is no comparative study with the low-FODMAP diet, but drawing comparisons between similar studies holds out the prospect of similar results.

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old sources


Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Pediatrics Gastroenterology

Modulation of the microbiota by FMT: controversial results

Fecal transplant, targeted diets, probiotic supplementation...: although the prospects are promising, the conclusions of some publications point not only to the complexity of the subject but also to its limitations.16,17

The gut microbiota What are the long-term effects of antibiotics on the gut microbiota? Role of the microbiota in gut-brain communication Antibiotic exposure during first six years of life disrupts gut microbiota and impairs child growth

The efficacy of fecal transplant in the treatment of dysbiosis seems proven, but its impact on FGIDs is more questionable.

REAL EFFICACY AGAINST DYSBIOSIS

A Danish study conducted in 2016 highlighted the efficacy of fecal transplant in cases of dysbiosis in IBS patients and revealed a significant improvement in the diversity of their gastrointestinal microbiota. The collection of fecal samples at each visit (enrolment, 1, 3 and 6 months) allowed the characterization of bacterial populations by sequencing. Analysis of the microbiota of the transplanted patients at 3 months revealed the presence of 11 species of interest. Two species displayed weak negative correlations with the IBS-SSS–or Irritable Bowel Syndrome Severity Scoring System–(both belonging to the Blautia genus which is associated with a healthy gastrointestinal microbiome) and three moderately positive (two belonging to the Bacteroides genus and one to the Ruminoccocaceae family). As of now, fecal transplant therefore appears to represent a technique for the treatment of dysbiosis in IBS patients, and potentially all FGIDs, although larger scale studies are required to define its clinical efficacy.

DIVERGENT RESULTS

The question is however raised: is fecal transplant also able to correct the pathological phenomena associated with dysbiosis? It is difficult to give a final answer regarding FGIDs, mainly because of the scarce number of randomized clinical studies. The few trials available in the scientific literature deal with IBS and do not yet allow a judgment to be made because of divergent conclusions.

IBS-SSS SCORE

Functioning

The IBS-SSS score is comprised of 5 parameters quantified on a 100-point analog scale.

The five items added together give a severity score between 0 and 500.

  • 0-75 > control or patient in remission
  • 75-175 > benign form
  • 175-300 > moderate
  • 300 and over > severe 


Criteria

  • Severity of abdominal pain;
  • Frequency of abdominal pain;
  • Severity of bloating;
  • Relief after defecation;
  • Interference with quality of life

PROS AND CONS

In Norway in 2015, 83 participants aged between 18 and 75 took part in a study: after an enema 2/3 of them received a fecal transplant and 1/3 a placebo (their own feces) in both cases via the colon. The reduction of symptoms at three months was evaluated using the IBS-SSS score. The difference was significantly in favor of transplant: 65% improvement against 43% for the placebo–a difference which was not confirmed at 12 months. The “loss of efficacy” could be explained by a powerful effect of the transplanted microbiota right after the administration, but a difficulty in grafting durably in its host due to the effect of exogenous and/ or endogenous factors. One year later in 2016, another study disproved the benefit of fecal transplant: after an enema, 52 patients with moderate or severe disease received a graft (orally) from healthy donors (n=26) or a placebo (n=26). The IBS-SSS score and quality of life were then evaluated. At 3 months, a significantly greater improvement in symptoms and quality of life was observed… in the placebo arm. Suggested hypotheses: the fecal transplant could counteract a positive effect of the enema; some pathogenic microorganisms could be removed by the enema then reintroduced by transplant; the duration of treatment or the quantity of re-implanted fecal bacteria might be insufficient.

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old sources


Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Pediatrics Gastroenterology

In adults

The FGIDs encountered in adults are functional diarrhea, functional bloating, and especially IBS and functional constipation. As in children, their etiology is poorly understood.13,14,15

The gut microbiota What are the long-term effects of antibiotics on the gut microbiota? Role of the microbiota in gut-brain communication Antibiotic exposure during first six years of life disrupts gut microbiota and impairs child growth

A MICROBIAL SIGNATURE

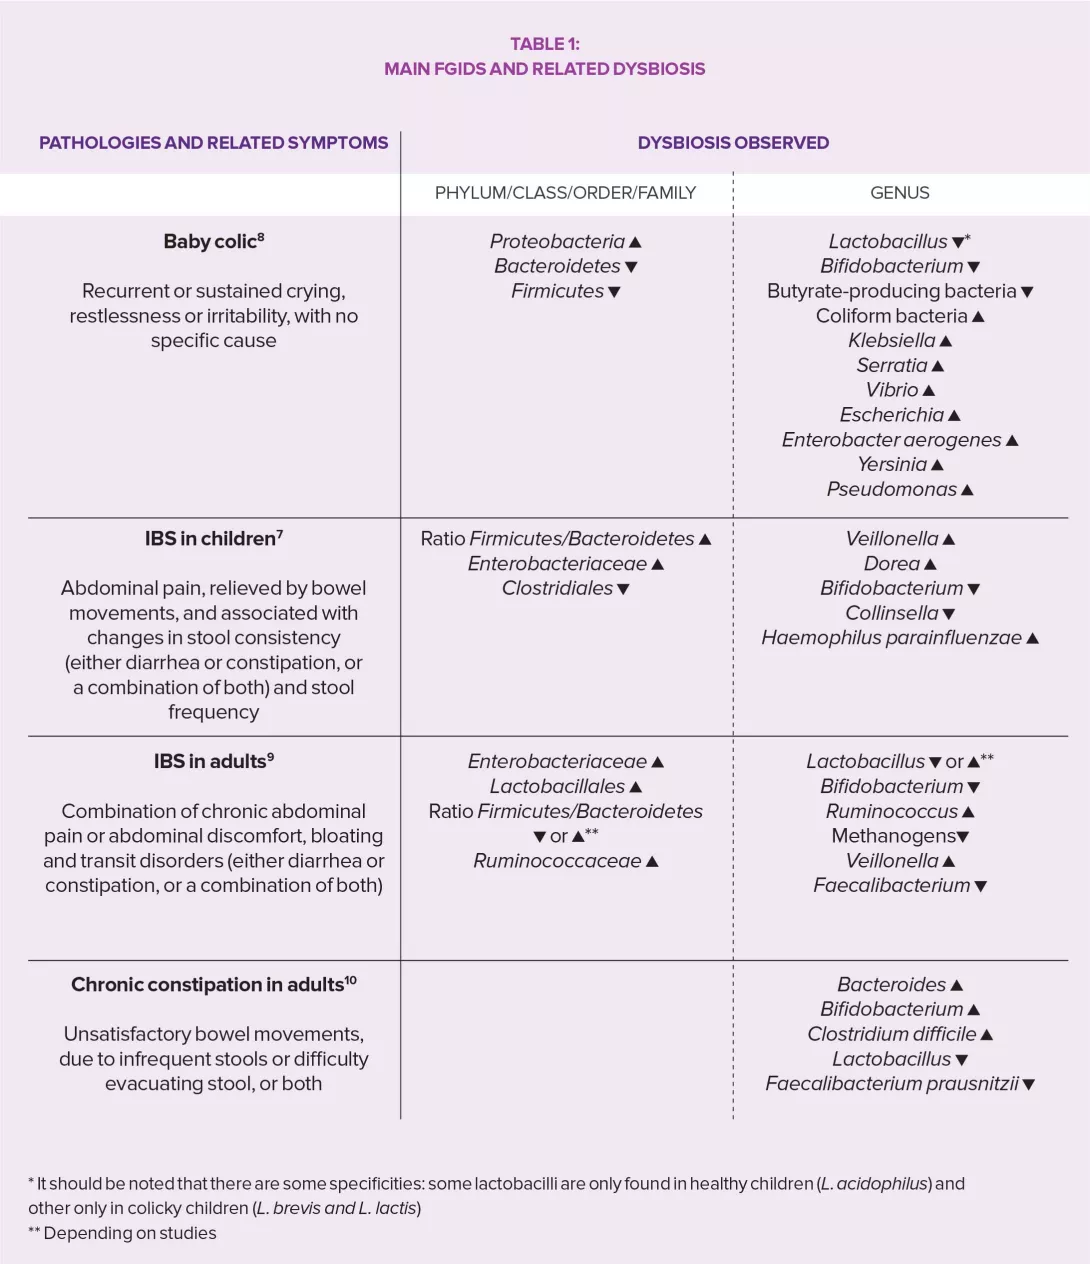
An Italian team has suggested the hypothesis that bacterial and biological markers (SCFA) could be used to discriminate between the different subtypes of IBS, a disorder that affects between 7% to 21% of the general population depending on the countries under consideration. Characterization of the fecal samples of 40 patients suffering from IBS (5 samples collected at 4 week intervals) demonstrated that certain bacterial species enabled the different IBS subtypes to be discriminated: in particular, greater abundance of bacteria belonging to the Ruminococcaceae and Lachnospiraceae families were observed in the IBS C subtype compared to the IBS-D subtype. Fecal concentrations of SCFA would also seem to be effective markers for discrimination of the different subtypes: among others, fecal concentrations of acetate, butyrate, propionate and valerate are significantly higher in patients with IBS-D compared to patients with IBS-C. Finally, for each pathological subtype, the bacterial signatures identified could be correlated with a specific fecal concentration of SCFAs, fecal cytokine levels as well as stool consistency.

IBS SUBTYPES ACCORDING TO ROME IV

  • IBS-D (associated with diarrhea)
  • IBS-C (associated with constipation)
  • IBS-M (mixed subtype)
  • IBS-U (unclassified)

The pathophysiological mechanisms that fall under one subtype rather than another remain obscure, but the clinical differences foreshadow the existence of specific biological markers capable of guiding diagnosis and management.

CHRONIC CONSTIPATION: THE SEROTONIN PATHWAY (5-HT)

Although chronic constipation in adults is less often mentioned, it does impact quality of life. The disorder affects between 2% and 20% of the population depending on the study; it is frequently accompanied by intestinal dysbiosis and could involve hormone-mediated interactions. An international team has investigated serotonin, a key neurotransmitter of the gut-brain axis, which is thought to be involved in gastrointestinal motility. The concentration of serotonin, 95% of which is secreted by enterochromaffin cells, could be regulated by the intestinal microbiota via the expression of the serotonin transporter (SERT). This hypothesis was tested through fecal transplants from human subjects with chronic constipation and healthy individuals to mice whose microbiota was weakened by antibiotic therapy. The mice that received a transplant quickly displayed reduced gut peristalsis, abnormal defecation parameters, overexpression of SERT in the colon and reduced serotonin concentrations. Characterization of bacterial populations in these mice showed a depletion of Clostridium, Lactobacillus, Desulfovibrio and Methylobacterium genera and an enrichment of Bacteroides and Akkermansia genera. This reflects a marked dysbiosis, which, according to the researchers, could trigger positive regulation of SERT expression, and consequently increase the reuptake of the serotonin responsible for a reduction in intestinal motility.

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Gastroenterology

In children and adolescents

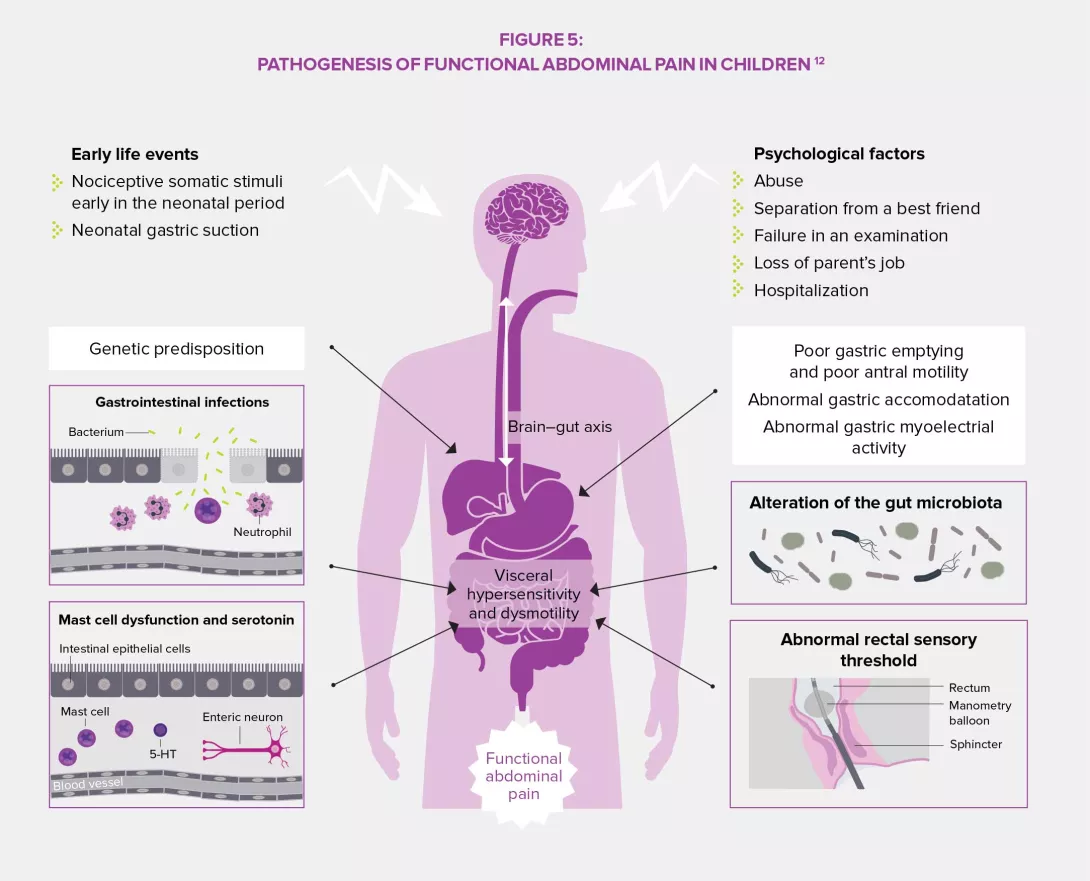
Functional abdominal pain associated with pediatric FGIDs may assume various forms which should be clearly identified for correct management. In many cases it is triggered by irritable bowel syndrome.7

The gut microbiota What are the long-term effects of antibiotics on the gut microbiota? Role of the microbiota in gut-brain communication Antibiotic exposure during first six years of life disrupts gut microbiota and impairs child growth

PATHOPHYSIOLOGY OF FUNCTIONAL ABDOMINAL PAIN

Functional abdominal pain is one of the most common syndromes in children, with an estimated global prevalence of 13.5% in 2014.11 Most causes are functional and involve changes in visceral sensation (hyperalgesia) and impaired gastrointestinal motility. The former are expressed as discomfort and pain, the latter as diarrhea or constipation, nausea, bloating, distension… The diversity of symptoms observed led the Rome Foundation to distinguish four broad categories of functional abdominal pain in children: irritable bowel syndrome, functional dyspepsia, abdominal migraine and functional abdominal pain not belonging to any of the above-mentioned categories.11

IBS: A CULTURAL PERCEPTION?

Even though irritable bowel syndrome is the most common FGID in children and a real public health issue at global level, it remains overlooked. The very perception of this condition seems to vary significantly between countries and studies, since its prevalence varies from 5.1% in the United States to 22.6% in Turkey, and ranges from 2.8% to 25.7% in some Asian countries. Such differences could possibly be ascribed to local particularities, but are more probably due to interpretations of the Rome IV diagnostic criteria that vary depending on culture, relationship to pain and what is considered a true disease–and not a simple change in bowel movements.

IBS IN CHILDREN: HOLISTIC MANAGEMENT

Characterized by a less diverse gastrointestinal microbiota (especially in contact with the mucosa), increased levels of some Clostridia and Firmicutes (Veillonella) and reduced levels of bifidobacteria (Table 1), IBS represents 40 to 45% of FGIDs in children. The therapeutic education of the parents occupies a central place in its treatment, as their anxiety can have a significant impact on the severity of symptoms and the efficacy of treatment, whether it is pharmacological or not. Standard drugs are those used to treat IBS in adults: gastrointestinal motility stimulants, antispasmodic agents, antacids, antihistamines, antireflux agents… whose efficacy has not been evaluated. A literature review suggests that among non-pharmacological treatments, some psychological approaches (mental imagery, hypnosis, cognitive behavioral therapy, yoga) could help improve the child’s health. In view of the disruptions of the microbiota identified in young IBS patients, the use of probiotics is also a promising therapeutic option.

Image
FGIDS-In-children-infography1

PREDISPOSITION AND PREVENTION

A multitude of factors predispose to the development of IBS: gender, age, psychological factors, neonatal trauma, gastrointestinal infections, asthma, atopic disorders, diet, socioeconomic, familial and environmental factors… Some of these may represent potential areas for the implementation of preventive actions which would aim to reduce the prevalence of disorders in children and adults weakened during their childhood, as well as decrease individual and societal healthcare costs. It is the responsibility of the different healthcare systems to prioritize their approaches and actions according to risks, needs, and possibilities.

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old sources


Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Pediatrics Gastroenterology

Pharmacokinetics: major role for gut bacteria

The gut microbiota seems to be involved in the metabolism of a large number of drugs administered orally, as demonstrated by American researchers based on genetic markers.

The gut microbiota Gut microbiota thought to block the effects of antidepressants Antibiotic exposure during first six years of life disrupts gut microbiota and impairs child growth What if manipulating the microbiota could improve the response to immunotherapy?


The impact of the gut microbiota on the metabolism of some drugs has already been reported: it could lead to the activation, deactivation, or increased toxicity of (sidenote: Some compounds Among others, activation of sulfasalazine, deactivation of digoxin, and increased toxicity of irinotecan ) *. However, the scope and mechanisms of this impact remain largely unstudied. An American team opened the way by studying the disposition of 271 drugs administered orally–except antibiotics–under the effect of 76 species or strains mainly from the human gut microbiota.

Selective bacteria

Primary trials have been conducted in vitro by incubating drugs and bacteria during 12 hours. Two thirds of drugs were metabolized at more than 20% and by at least one bacterial strain (each strain metabolizes between 11 and 95 drugs). Omeprazole, sulfasalazine, risperidone, or even lovastatin, were among the most targeted drugs, thus confirming previous results. Moreover, some chemical components seem to be the preferred targets of this bacterial metabolism: for instance, ester or amide groups of therapeutic compounds are the favorite target of Bacteroidetes. In the specific case of dexamethasone (a glucocorticosteroid), trying to associate a bacterial species to the drug was not very relevant: it is necessary to identity the genes directly associated to the enzymatic conversion. According to the authors, the experiment suggests that it would probably be the case for other glucocorticosteroids (prednisolone, prednisone…).

Combined biotransformations

The next step was performed in vivo and consisted in identifying the genetic markers of the observed bacterial biotransformations. This approach was first validated with the bacterium Bacteroides thetaiotaomicron. 16 other enzymes derived from this bacterium were identified, metabolizing 18 drugs into 41 metabolites. Extending this method to the 76 bacteria selected in this study showed that the transformation of a drug could require the combined effect of enzymes from several species; for example, tinidazole is metabolized by three different species. In total, the team identified 30 enzymes derived from the gut microbiota which, together, transform 20 drugs into 59 different metabolites. This confirms that pharmacokinetics is related to gut bacteria. One more step towards a tailored therapeutic approach capable of anticipating the response of an individual to a given treatment based on his/her microbiotic profile.


Summary
Off
Sidebar
On
Migrated content
Activé
Updated content
Désactivé
Old content type
pro_article
Hide image
Off
News Gastroenterology

In newborns

Functional gastrointestinal disorders are liable to manifest themselves from the first moments of life. The predominating pathologies vary according to age, but are accompanied by extensive involvement of the intestinal microbiota.

The gut microbiota What are the long-term effects of antibiotics on the gut microbiota? Role of the microbiota in gut-brain communication Antibiotic exposure during first six years of life disrupts gut microbiota and impairs child growth

The main FGID in infants is colic. This disorder, whose pathophysiology is poorly understood, could originate in the microbiota and is thought to warrant new therapeutic approaches, as the efficacy of standard treatments has proven variable from one individual to another.

A DISEASE WITH IMPRECISE BOUNDARIES

Baby colic has an estimated prevalence of 5% to 28% depending on the study, and is a benign syndrome characterized by recurring bouts of crying, often accompanied by physical symptoms: clenched fists, straightened legs, facial redness. Appearing classically at around two weeks old, it reaches peak severity between 5 to 8 weeks and resolves spontaneously at around the age of 4 months. Its pathogenesis is still unclear, and diagnosis is currently based on Rome IV criteria. Organic causes are thought to represent only a small proportion of causes involved (5%). Additional factors such as an allergy to cow’s milk protein, family tensions and anxiety, etc. are likely to play a part.

CURRENT TREATMENTS

The diversity of causes makes patient care complex and encourages the diversification of treatment options, rendering treatment non-specific. What are the main current approaches? Drugs (mucosal protective agents, antispasmodics…), diet (modified diets, especially formulas based on casein hydrolysate, whey or soy milk…), behavioral techniques (chiropractic, reduced stimulation of the child…) and some probiotics.

INNOVATIVE ETIOLOGICAL HYPOTHESES INVOLVING THE MICROBIOTA

An international team has proposed three etiological hypotheses which could lead to new therapeutic approaches: first of all, immaturity of the enterohepatic circulation and of the action of bile acids leading to malabsorption of fats and other nutrients, as well as possible side effects on the intestinal microbiota.8 Secondly, intestinal dysbiosis, triggering an increase in nutrient fermentation and reduced levels of dehydroxylated bile acids in the colon. Finally, immaturity of the enteric nervous system resulting in abnormal sensorimotor function in the intestines and colon. The future characterization of these three mechanisms, which display numerous potential interactions, could lead to a more specific diagnosis and personalized management based on targeted biomarkers.8

Image
FGIDS-In-newborns-infography1
Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old sources


Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Pediatrics Gastroenterology

Focus on the gut-brain axis

Psychic disorders influence the development of FGIDs, and conversely, through the gut-brain axis. In this regard, the intestinal microbiota could have an impact on the expression of psychiatric symptoms.

The gut microbiota What are the long-term effects of antibiotics on the gut microbiota? Role of the microbiota in gut-brain communication Antibiotic exposure during first six years of life disrupts gut microbiota and impairs child growth

GUT-BRAIN: BIDIRECTIONAL COMMUNICATION

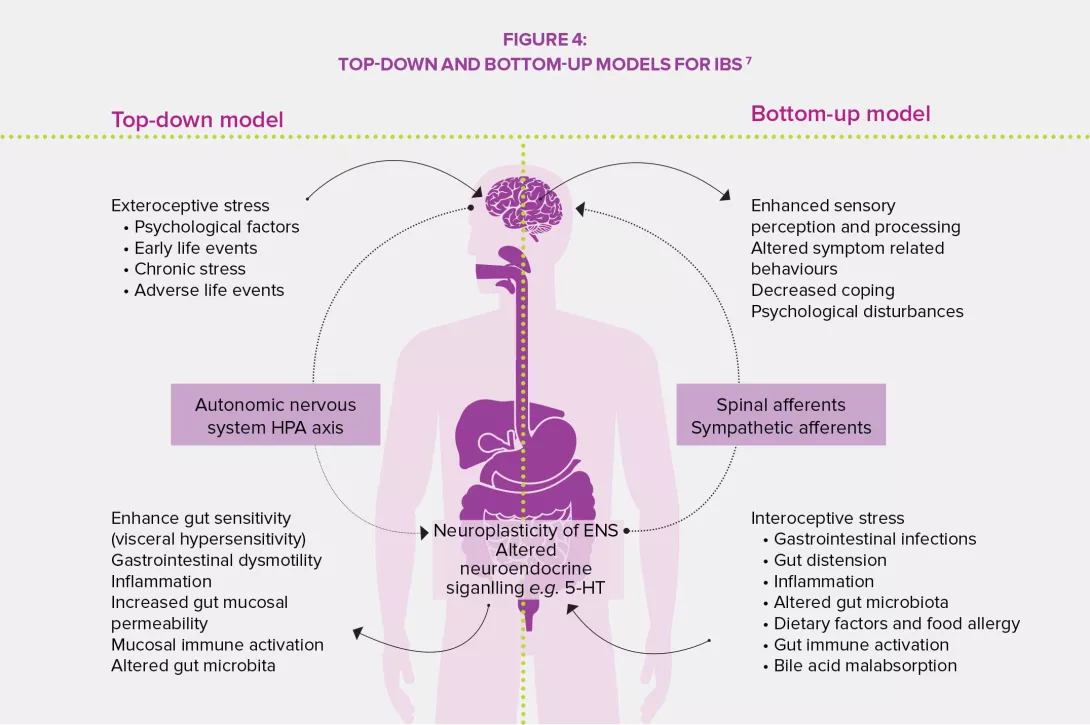
Psychological and psychosocial factors are key to understanding the pathophysiology of FGIDs. Psychic disorders (anxiety, depression, neurosis…) are frequent comorbidities in patients with FGIDs. It is however difficult to determine whether the former generate the latter, or if it is the opposite.4,5,6 Recent studies clearly concluded that bidirectionality is at play, i.e. a reciprocal influence. At a visceral level, exchanges are based on the enteric nervous system and substances produced by intestinal bacteria (SCFA, metabolites…). At a central level, the involved structures are those of the emotional motor system (anterior cingulate cortex, hippocampus, hypothalamus…).4,5,6

ROLE OF THE GUT-BRAIN AXIS IN IBS

Animal models have revealed that bidirectional communication was disrupted in patients with IBS, although mechanisms ensuring communication between microbiota and brain have not been elucidated. However, several elements that appear to contribute to this mechanism have been identified: the microbiota sends signals to the CNS through enteroendocrine cells (release of serotonin), dendritic cells and B-cells (release of cytokines), products of bacterial metabolism (SCFA, GABA…) and stimulation of vagal afferent fibers. In the other direction, stress and feelings affect the composition of the microbiota through stress hormones and sympathetic nervous system.4,5,6

Image
Focus-on-the-gut-brain-axis-infography1
Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Pediatrics Gastroenterology