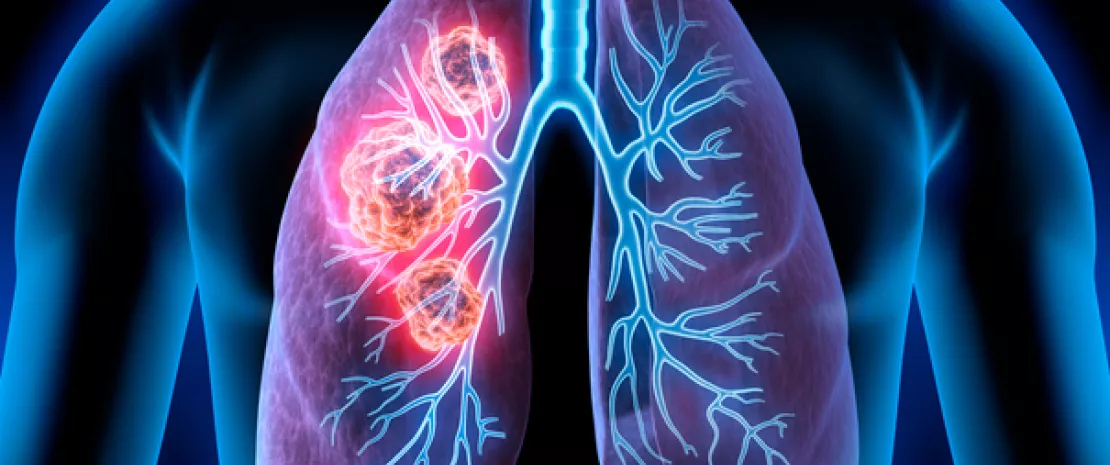
Gut microbiota could be an indicator of early-stage lung cancer

Intestinal dysbioses have been detected in patients with early-stage lung cancer. Could this lead to the development of an early-stage, non-invasive test that would speed up care and improve chances of survival?

The gut microbiota Can the lung microbiota reliably predict lung transplant rejection? Lung microbiota: a prognostic marker of COPD? Oral microbiota, a risk factor for lung cancer?
Photo : Gut microbiota could be an indicator of early-stage lung cancer

Often diagnosed at an advanced stage, lung cancer is associated to a high mortality rate. An earlier diagnosis would greatly improve both care and chances of survival. Can gut dysbioses serve as an indicator of lung cancer, as for many other diseases, including other types of cancer?

Specific gut dysbiosis signature as an indicator of the stage of cancer

The gut microbiota of 42 patients with (sidenote: Adenocarcinoma (37 patients), squamous cell carcinoma (3 patients), large-cell carcinoma (2 patients) )  of non-small-cell lung cancer (NSCLC) at an early stage (metastasis had taken place in only 3 patients), and that of 65 healthy control subjects, were analyzed using 16S rRNA sequencing. Intestinal dysbioses were observed in the patients with lung cancer: increased presence of species belonging to the Ruminococcus genus and the Lachnospiraceae and Enterobacteriaceae families, among others, compared to control subjects. Therefore, the composition of the microbiota may change as lung cancer develops. In addition, the composition of the intestinal microbiota was specific of each stage of the cancer, with some bacteria only present in the three patients displaying metastasis.

A diagnostic tool?

In order to develop a non-invasive diagnostic tool for early-stage lung cancer, 13 biomarkers based on (sidenote: Operational Taxonomic Unit groups of organisms usually not cultivated or not identified, classified on the basis of the similarity of the DNA sequencing of a given gene. Frequently used as an equivalent to the concept of species )  were identified. Together, these biomarkers made it possible to accurately predict the presence of lung cancer (97.6% of cases). This model was confirmed in a second cohort (34 patients and 40 control subjects), with its predictive power remaining high (76.4%), although lower than in the initial cohort. From this model it was possible to construct a “patient discrimination index” to identify patients with early-stage lung cancer. Based on a weighted score, the index is easy to use for clinical purposes. Its predictive power in the initial cohort (92.4%) was also higher than that measured in the validation cohort (67.7%). Larger cohorts could improve the model and its predictive power.


Summary
Off
Sidebar
On
Migrated content
Activé
Updated content
Désactivé
Old content type
pro_article
Hide image
Off
News Pulmonology Oncology Gastroenterology

MICROREVEAL: the new series on microbiota

As part of World Microbiome Day on June 27, and to celebrate microbiota diversity, the Biocodex Microbiota Institute is introducing a series on these high-impact microbial communities. A fascinating new world is open to you!

The vaginal microbiota What foods promote a balanced microbiota?
Actu GP : MICROREVEAL : la nouvelle série sur les microbiotes

Experts have the floor

You’ve surely already heard of microbiota. Did you know they’re essential to the proper functioning of the body? World Microbiome Day is a chance to celebrate them. It aims to raise general awareness about the importance of these microbial communities, highlighting advances in research. Our new MICROREVEAL series is part of this educational goal. On June 27 and for the rest of the year, the series will shine a new light on the diversity of microbiomes. In these video reports, journalist Louise Ekland will interview experts about the influence of the various microbiomes in our bodies.

Focus on the vaginal microbiota

This first episode will focus on the vaginal microbiota. Like Julie, you probably wish to know more about this microbiota which plays a key role in women’s health. Louise interviewed Dr. Jean-Marc Bohbot, andrologist and specialist in urogenital infections.

What infections are linked to an imbalance of the vaginal microbiota? What can be done on a daily basis to preserve this microbiota?

Image
Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old content type
article
Hide image
Off
News

Dr. Jean-Marc Bohbot : Complete therapeutic arsenal, the one that will also target microbiota

Dr. Jean-Marc Bohbot, an infectologist specializing in urogenital infections, is head of the Sexually Transmitted Infections Department at the Alfred Fournier Institute (Paris). He is also the author of books aimed at the general public on sexually transmitted infections and the vaginal microbiota.

The urinary microbiota Using recombinant endolysins to treat bacterial vaginosis Childhood immune system: the benefits of vaginal delivery Urinary microbiota in continent women: the effect of age

Complete therapeutic arsenal, the one that will also target microbiota

Do we not overestimate the importance of microbiota in the urogenital area?

In recent years we have come to understand the urogenital micro- biota more clearly. We now know that it can be a factor in infections, in urinary disorders related to the menopause and even in tumors. The urogenital microbiota and its disruptions must be taken into account in patient management and probiotics must be part of the therapeutic arsenal. Although probiotics are obviously not our only weapon, they are indispensable, since anti-infectious treatments do not treat the cause of recurrence, i.e. the dysbiosis.

What role do you think probiotics can play today against urinary tract infections?

Urinary tract infections are closely linked to imbalances in three microbiomes: the urinary micro- biota, since urine is not sterile; the vaginal micro- biota, with which the urinary microbiota shares many similarities; and the gut microbiota, from which the pathogens involved in urinary tract infections originate (e.g. E. coli, which passes from the anus to the vulvar vestibule and then to the bladder). Conventional antibiotic treatment is justified for single UTI episodes. On the other hand, for recurrent UTIs (more than four episodes per year), it is essential, after having ruled out functional causes (e.g. a tumor of the bladder), to question the pa- tient about possible disorders of the gut microbiota (constipation, etc.) and/or vaginal microbiota, the latter acting as a protective barrier between the digestive and urinary systems. The prevention of recurrence involves treatment for three to six months with intestinal probiotics administered orally, if a dysbiosis of the intestinal microbiota is present, and/or vaginal probiotics, ideally administered vaginally. These treatments may be combined with the use of cranberry, which reduces the level of E. coli in the bladder.

What about vaginal infections?

There are two types of vaginal infections: endogenous infections resulting from changes in endogenous microorganisms (bacteria or fungi) and exogenous infections contracted during sexual intercourse. For endogenous infections, in the case of a single episode, an antimycotic vaginal suppository or antibiotic treatment may suffice. However, where there is a risk of recurrence, the dysbiosis must be treated for several months with gynecological probiotics. Probiotics also have a role to play in exogenous infections, since the less balanced the vaginal microbiota, the greater the risk of acquiring a sexually transmitted infection (STI), and the higher the risk of an unfavorable outcome. For example, the papillomavirus is four to five times more likely not to be completely eliminated, and progresses more rapidly to potentially cancerous forms, when a dysbiosis exists. It is therefore important to test for an imbalance of the vaginal microbiota in infected women through a simple measurement of acidity (the pH should be between 3.5 and 4.5) and then by vaginal sampling where the pH is above 4.5. Where there is an imbalance, laboratory-tested and clinically approved probiotics should be prescribed. A vaginal dysbiosis also increases the risk of contracting HIV. Although the acidity of lactobacilli helps destroy the virus, an inflammatory state increases the presence of lymphocytes, the cells targeted by HIV.

Lastly, what can we expect from vaginal micro- biota transplants?

The results of just over twenty cases of vaginal microbiota transplants have been published. Al- though these results are interesting, they are not yet conclusive. The idea of treating recurrent bac- terial vaginosis through a microbiota transplant still raises concerns as regards the criteria for selecting donors–particularly since the absence of symptoms does not mean that the donor’s flora is balanced–and the indications for the recipient. It will most likely be known within a year or two whether vaginal microbiota transplants can be used as a last resort.

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old content type
pro_dossiers_article
Hide image
Off
Expert opinion Urology

Vaginal area: efficacy confirmed

In order to maintain a lactobacilli-dominated protective flora, the use of topical or oral probiotics to prevent or treat vaginal infections, as well as a first clinical trial focused on vaginal microbiota transplants, have been initiated. Results are positive.

The urinary microbiota Cervicovaginal microbiota: a marker for persistent papillomavirus infection? Using recombinant endolysins to treat bacterial vaginosis Childhood immune system: the benefits of vaginal delivery

Lactobacillus crispatus

41% Only 41% of women surveyed say they have taken probiotics and/or prebiotics (either orally or vaginally)

PROBIOTICS: IMPORTANCE OF BACTERIA AND YEASTS

Since a vaginal microbiota dominated by lactobacilli is considered optimal, vaginal probiotics unsurprisingly contain strains of this genus, which vary depending on the probiotic in question (L. acidophilus, L. crispatus, L. reuteri, L. rhamnosus). A review of 22 commercially available topical vaginal probiotics carried out in early 2019 highlighted their potential for the prevention and treatment of BV, but much less so for the prevention and treatment of vulvovaginal candidiasis.20 None of the studies reported any major safety concerns.

Probiotic strains have never been detected in the vagina beyond the period of administration, suggesting they do not colonize the environment in a sustained manner.

In addition to probiotics for local use, oral probiotics have gained considerable importance. Four strains (L. crispatus, L. gasseri, L. jensenii and L. rhamnosus) out of 127 vaginal lactobacilli studied are noteworthy for their ability, in vitro, to acidify the environment, inhibit the growth of G. vaginalis and C. albicans and survive gastrointestinal transit.21

Image

But what about in vivo? Consumed in the form of a yoghurt drink by patients suffering from BV (twice a day for four weeks), these same four strains led to a 100% recovery (Amsel criteria), compared to a 65% recovery in the placebo group.22 In addition to bacteria, certain yeasts may also be of interest, particularly against C. albicans. Saccharomyces boulardii, already used in the prevention and treatment of intestinal infections, naturally secretes capric acid, which modifies the structure of C. albicans, reducing its adhesion capacity, inhibiting its filamentation and hindering its ability to form biofilms.23

Since a vaginal microbiota dominated by lactobacilli is considered optimal, vaginal probiotics unsurprisingly contain strains of this genus

VAGINAL MICROBIOTA TRANSPLANTS: PROMISING FIRST CLINICAL TRIALS

In October 2019, the results of a first exploratory trial testing the transplant of vaginal microbiota from donors as a therapeutic alternative in five patients with symptomatic, untreatable and recurrent BV were published in Nature Medicine.24

Four patients showed a full long-term remission (sometimes requiring several transplants or even a change of donor) up to the end of the follow-up period (5 to 21 months after the transplant), with a marked improvement in symptoms, Amsel criteria and the microscopic appearance of vaginal fluids, as well as the reconstitution of lactobacilli-dominated vaginal microbiota.

The remaining patient is still in incomplete remission, while no adverse side-effects were observed. Accordingly, the researchers recommended further trials evaluating the therapeutic efficacy of vaginal microbiota transplants.

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Urology

Urinary area: efficacy to be confirmed in clinical trials

Since lower urogenital infections seem closely related to a dysbiosis of the urinary or vaginal microbiota, treatments attempt to regulate the microbiota in order to prevent or even cure these conditions.

The urinary microbiota Vaginal microbiota and predisposition to candidiasis Cervicovaginal microbiota: a marker for persistent papillomavirus infection? Urinary microbiota in continent women: the effect of age

Vaccinium macrocarpon

In order to endow the urinary microbiota with the diversity it requires to be in equilibrium and reduce the development of bacterial resistance to antibiotics, the use of probiotics and cranberry has also been considered.

Different strains of lactobacilli have demonstrated their potential, although further clinical trials are expected.

Popular with patients, alternative treatments to antibiotics aim to prevent recurrence and antibiotic resistance. They are in line with the recommendations of health authorities, including the Haute Autorité de Santé (HAS) in France, which works to “encourage the appropriate use of antibiotics in order to reduce bacterial resistance that can lead to therapeutic deadlock”.15 Cranberries, in the form of a 36 mg/day dose of proanthocyanidin, can be used to prevent the recurrence of UTIs linked to E. coli.16

The depletion of the urinary microbiota in women susceptible to UTIs has raised the question of whether an intake of microorganisms via probiotics can reduce UTI rates. An ideal probiotic should have the ability to adhere to cells, prevent and reduce the adhesion of pathogens, secrete acids (e.g. lactic acid), hydrogen peroxide and bactericides capable of reducing the growth of pathogens, be free of adverse side-effects (they should not be invasive, carcinogenic or pathogenic) and be capable of forming clumps to produce normal, balanced flora.17

According to the literature, probiotics have proven effective in the treatment and prevention of urogenital infections.17 Certain lactobacilli (L. rhamnosus, L. fermentum and L. reuteri) have been shown to have a beneficial effect in treating urinary tract infections.18 An inhibitory effect on E. coli has been demonstrated in vitro, with certain strains of lactobacilli (L. rhamnosus and L. plantarum) possessing antimicrobial properties against this bacterium.19

Therefore, the data increasingly suggests that probiotics may be used as a first step in the regulation of urinary microbiota in order to reduce the risk of, or treat, certain urinary infections, particularly since they are safe, better tolerated than antibiotics and frequently requested by patients.17 However, further clinical trials involving large numbers of patients will be required to obtain clear evidence on the preventive and curative role of probiotics in urinary tract infections.17

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Urology

Dysbiosis-related infections of the lower genital tract

Unlike the urinary microbiota and many other microbiotas, the vaginal microbiota, when healthy, has low diversity and is mostly dominated by a few lactobacilli. A dysbiosis where lactobacilli lose their predominance has been linked to infections of the lower genital tract (bacterial vaginosis, vulvovaginal candidiasis).

The urinary microbiota Vaginal microbiota: a marker for papillomavirus progression? Vaginal microbiota and predisposition to candidiasis Childhood immune system: the benefits of vaginal delivery

Candida albicans

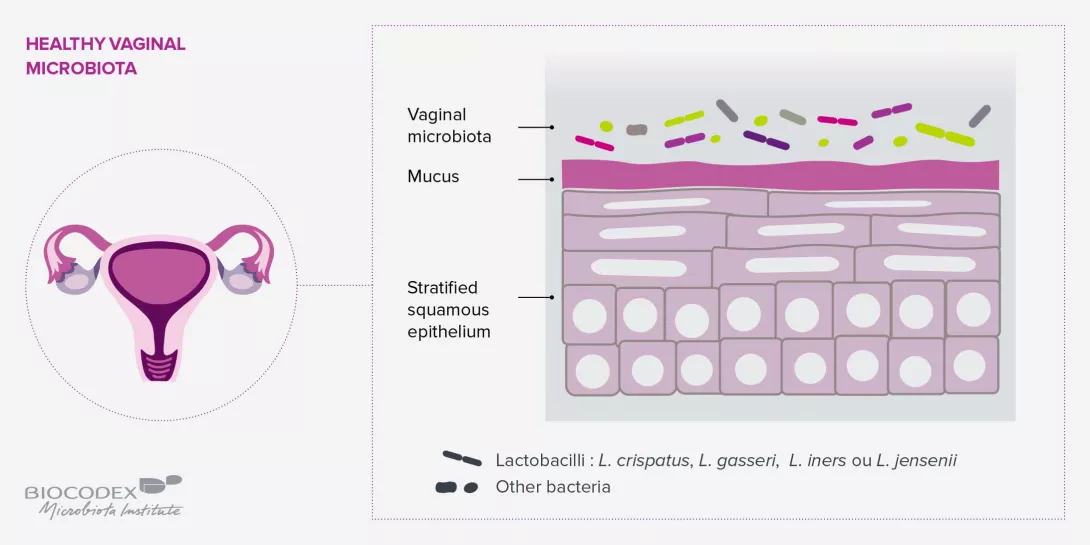
A HEALTHY VAGINAL MICROBIOTA: LOW DIVERSITY AND DOMINATED BY LACTOBACILLI

The vaginal microbiota consists mainly of lactobacilli with a protective role. Despite considerable variability among women, in general, five types of community have been categorized, depending on whether they are dominated by L. crispatus, L. gasseri, L. iners or L. jensenii, or have few or no lactobacilli and a significant quantity of strict anaerobic bacteria (Megasphera, Prevotel- la, Gardnerella and Sneathia) known to be characteristic of bacterial vaginosis.8

Therefore, while a high number of microbial communities is usually an indicator of health for several microbiotas (digestive microbiota, etc.), the vaginal microbiota is balanced when it has low diversity and is dominated by one or a few species of lactobacilli. In women of childbearing age, hormones promote the proliferation of lactobacilli. Estrogen levels induce the deposition of large amounts of glycogen, the main source of energy for lactobacilli, on the vaginal walls.8 From adolescence to the menopause, high estrogen levels promote colonization of the vagina by lactobacilli which metabolize glycogen, produce lactic acid and maintain intravaginal health by lowering the pH level.

the vaginal microbiota is balanced when it has low diversity and is dominated by one or a few species of lactobacilli.

BACTERIAL VAGINOSIS: WHEN G. VAGINALIS DRIVES OUT LACTOBACILLI

Despite more than sixty years of re- search, the etiology of BV remains unknown. Nevertheless, research seems to point more and more to the dysbiosis theory according to which dominant lactobacilli are replaced by polymicrobial flora derived from numerous bacterial genera (Gardnerella, Ato- pobium, Prevotella, etc.). G. vaginalis is in effect present in 90% of symptomatic subjects and 45% of normal subjects, whereas Lactobacillus sp. is found in 70% of apparently healthy subjects and 40% of symptomatic subjects.9 Consequently, G. vaginalis has been suspected of being the main pathogen in BV. However, there is long-standing disagreement in this regard, since this virulent bacterium has also been found in virgin girls and in sexually active wo- men with normal vaginal microbiota; in other words, colonization by G. vaginalis does not always lead to BV.10

Image
image1-article4-en

An explanation recently put forward may settle the debate: there is not one, but at least thirteen, different species of the genus Gardnerella, some of which may not be pathogenic. A mechanism for the development of the dysbiosis has even been suggested:10 G. vaginalis, transmitted sexually, spreads itself among healthy vaginal lactobacilli, such as L. crispatus, initiating the formation of a biofilm, a structure that further protects the pathogen from the hydrogen peroxide and lactic acid secreted by the lactobacilli. By reducing the redox potential of the vaginal microbiota, G. vaginalis gradually reduces the lactobacilli population in favor of strict anaerobic bacteria such as P. bivia and A. vaginae. G. vaginalis and P. bivia seem to facilitate each other’s development, the former providing amino acids to the latter and the latter ammonia to the former. Lastly, both pathogens produce an enzyme that destroys the mucus in the vaginal epithelium, facilitating the adhesion of different bacteria associated with BV, such as A. vaginae, and potentially causing a polymicrobial infection.

The vaginal microbiota also plays an important role in maintaining vaginal health and protecting the host against the acquisition and transmission of sexually transmitted infections.

VULVOVAGINAL CANDIDIASIS: A PROLIFERATION OF CANDIDA

Vulvovaginal candidiasis could be linked to an imbalance of the vaginal microbiota together with a proliferation of the fungus Candida, including C. albicans in 80%-92% of cases,11 and to a lesser extent C. glabrata, C. tropi- calis, C. parapsilosis and C. krusei.12 Exposure to antibiotics, whether local or systemic, is thought to be one of the main factors leading to vulvovaginal candidiasis.13 The reduction of certain bacterial species, lactobacilli or not, that control the replication and virulence of Candida yeasts apparently allows the Chlamydia tractomatis fungi already present in the vagina to multiply and induce infection. Future studies involving new sequencing technologies are needed to characterize in further details the interaction between vaginal microbiota, these yeasts and the occurrence and recurrence of vulvovaginal candidiasis.

HEALTHY VAGINAL MICROBIOTA: A SAFEGUARD AGAINST STIS

The vaginal microbiota also plays an important role in maintaining vaginal health and protecting the host against the acquisition and transmission of sexually transmitted infections. Vaginal microbiota with a small number of bacterial communities and dominated by lactobacilli (in particular Lactobacillus crispatus) are those most associated with vaginal health, whereas increased diversity seems to be associated with lower resilience to imbalances and higher susceptibility to STIs such as herpes (BV increases the risk of herpes and vice versa), papillomavirus (increased prevalence and likelihood of contracting HPV, delayed elimination, increased severity of cervical intraepithelial dysplasia), HIV (increased risk of acquisition and transmission), and other infections (gonorrhea, chlamydia and trichomoniasis).14

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Urology

Dysbiosis-related urinary tract infections

The microbiota seems to play an important role in infections of the lower urogenital system, whether it is the urinary microbiota (urine is not sterile) in the case of urinary tract infections, or the vaginal microbiota, in the case of bacterial vaginosis and vulvovaginal candidiasis. However, there is a difference: while diversity is favorable in the first case, it is unfavorable in the latter.

The urinary microbiota A gene catalog for the vaginal microbiota Vaginal microbiota: a marker for papillomavirus progression? Urinary microbiota in continent women: the effect of age

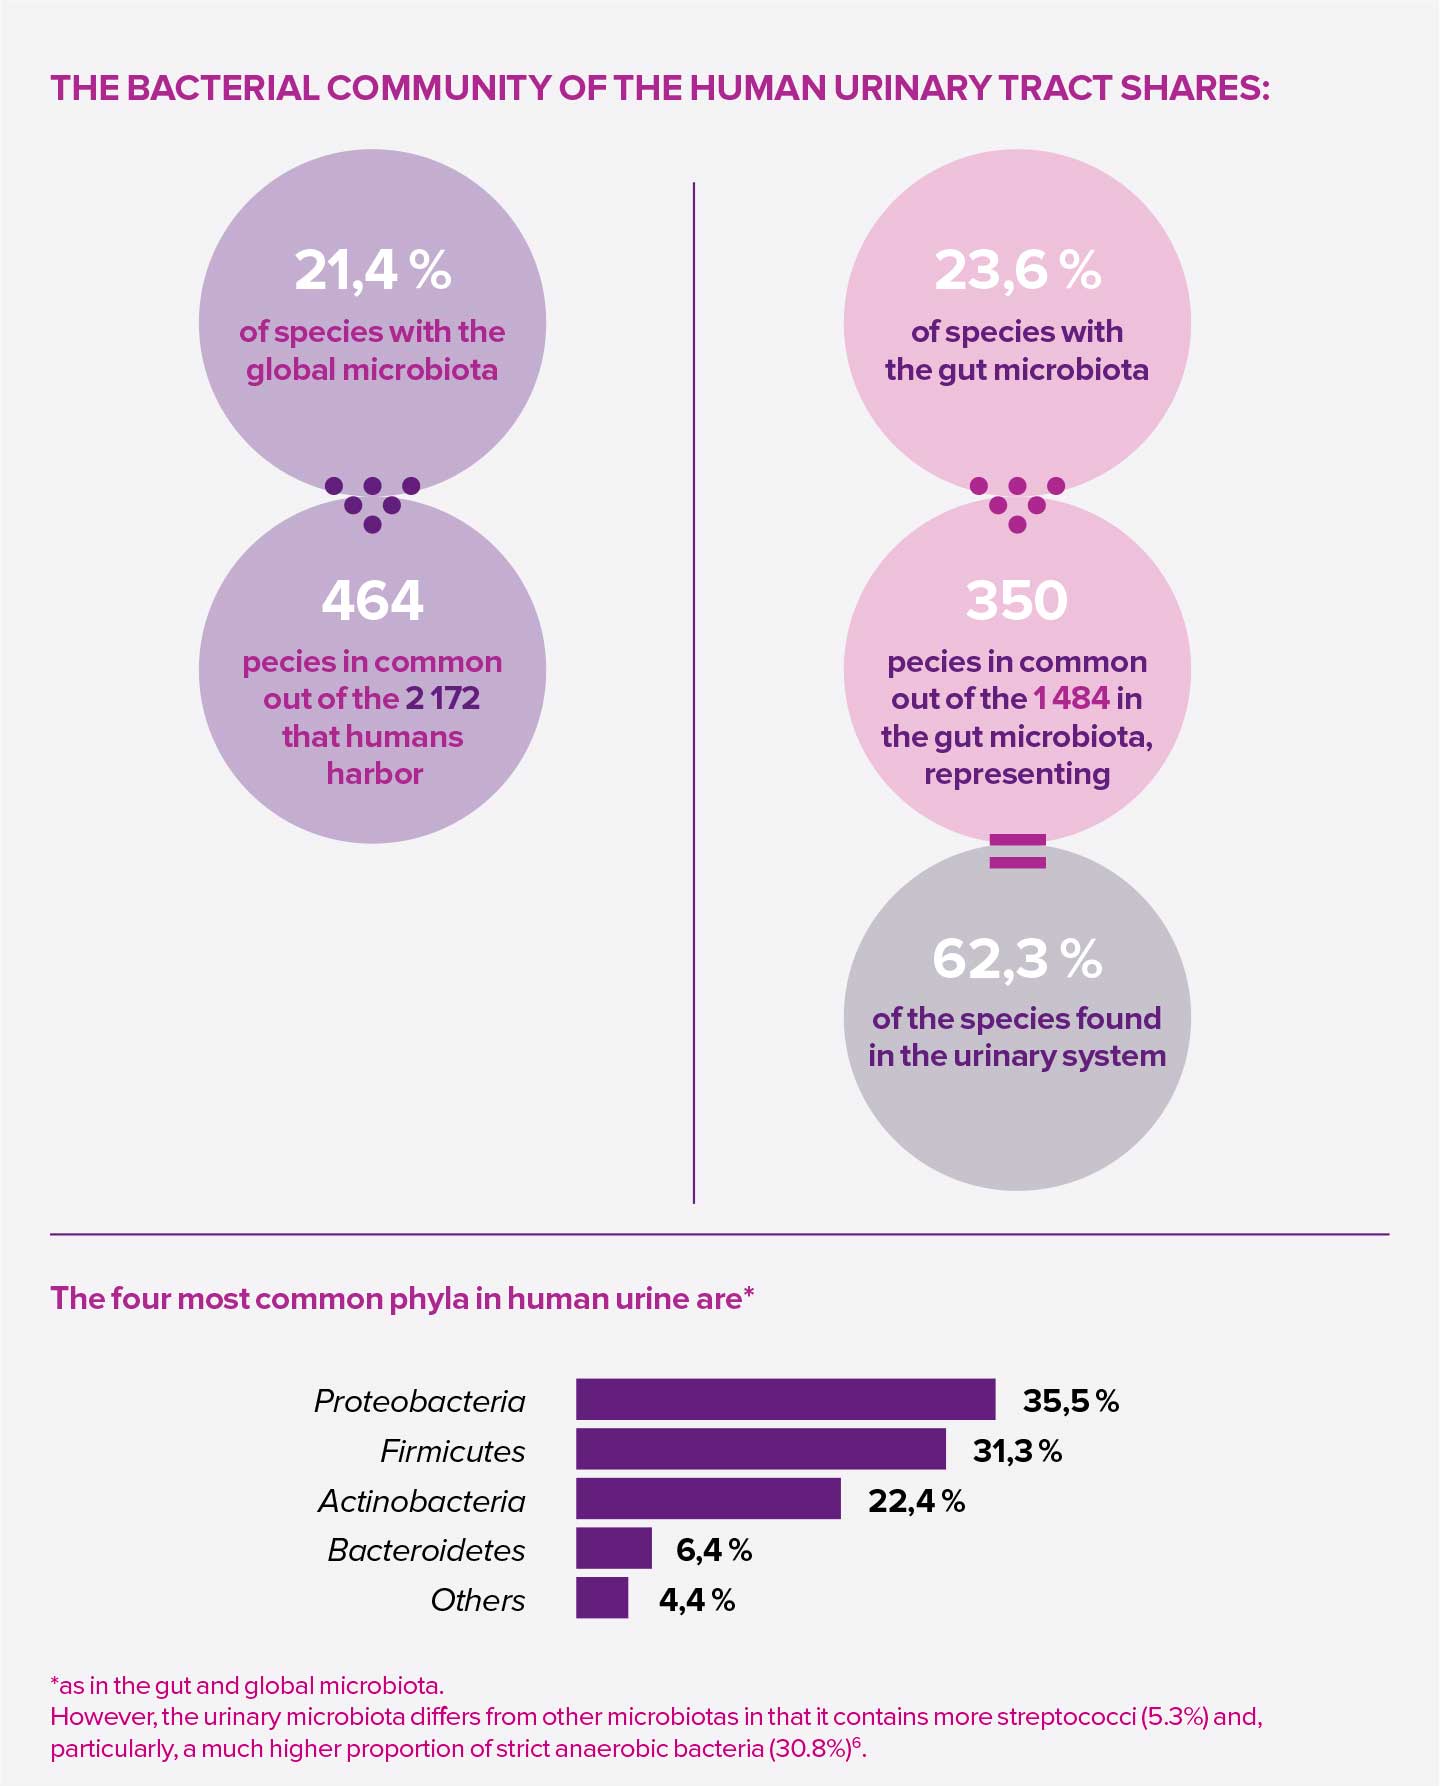
Although long considered sterile, the urinary tract is actually home to a microbiota containing over 500 bacterial species.

 A loss of diversity in this microbiota seems to be a risk factor for urinary tract infections.

URINE IS NOT STERILE

Historically, urine was considered sterile but recent scientific discoveries have shown that this is not the case: 562 bacterial species have been identified in the human urinary microbiota.6 Of these, 352 species (62.6%) have been linked to at least one report of infection among humans, including 225 (40.0%) described as the causal agent of urinary tract infections. The eight bacteria most commonly implicated in UTIs are Escherichia coli, Staphylococcus aureus, Pseudomonas aeruginosa, Chlamydia trachomatis, Neisseria gonorrhoeae, Klebsiella pneumoniae, Proteus mirabilis and Enterococcus faecalis.6 Conversely, bacteria that secrete lactic acid, namely Lactobacillus and Streptococcus, are believed to play a protective role against pathogens7: lactic acid lowers the pH of urine (≈ 4.5), resulting in a microenvironment that is unfavorable to most pathogenic bacteria, while lactobacilli produce antibacterial metabolites (hydrogen peroxide and bacteriocins).

GLOBAL, GUT AND URINARY MICROBIOTAS

image1-article3-en

WHEN DYSBIOSIS OPENS THE DOOR TO PATHOGENS

Studies published to date have demonstrated the clear role played by the urinary microbiota in urinary tract infections and responses to treatment.7 Several mechanisms have been put forward, for example, commensal bacteria acting as a barrier against uropathogens (secretion of inhibitory or bactericidal molecules), with a loss of diversity in the urinary microbiota leading to a urinary tract infection.6 Therefore, while most microorganisms colonize the human body without causing infection, they may be- come pathogenic under certain conditions (immunosuppression, antibiotic resistance, etc.). A urinary tract infection may therefore develop due to the action of commensal bacteria when a dysbiosis exists. Other potential factors include disorders of a traumatic (catheter), bio- chemical (acidity, etc.), hormonal (pregnancy), mechanical (constipation), or alimentary (food pathogen that reaches the urinary tract from the digestive system) nature.6 On the other hand, certain eating habits (consumption of fermented dairy products containing probiotic bacteria or of cranberry juice) may help reduce the risk of recurrent urinary tract infections by regulating the microbiota.6,7

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Urology

Vaginal infections

Bacterial vaginosis and vulvovaginal candidiasis are two very common gynecological infections. The first is a bacterial infection while the second is due to the spread of a fungus.

The urinary microbiota The vaginal microbiota as a predictor of the risk of premature delivery A gene catalog for the vaginal microbiota Childhood immune system: the benefits of vaginal delivery

BACTERIAL VAGINOSIS

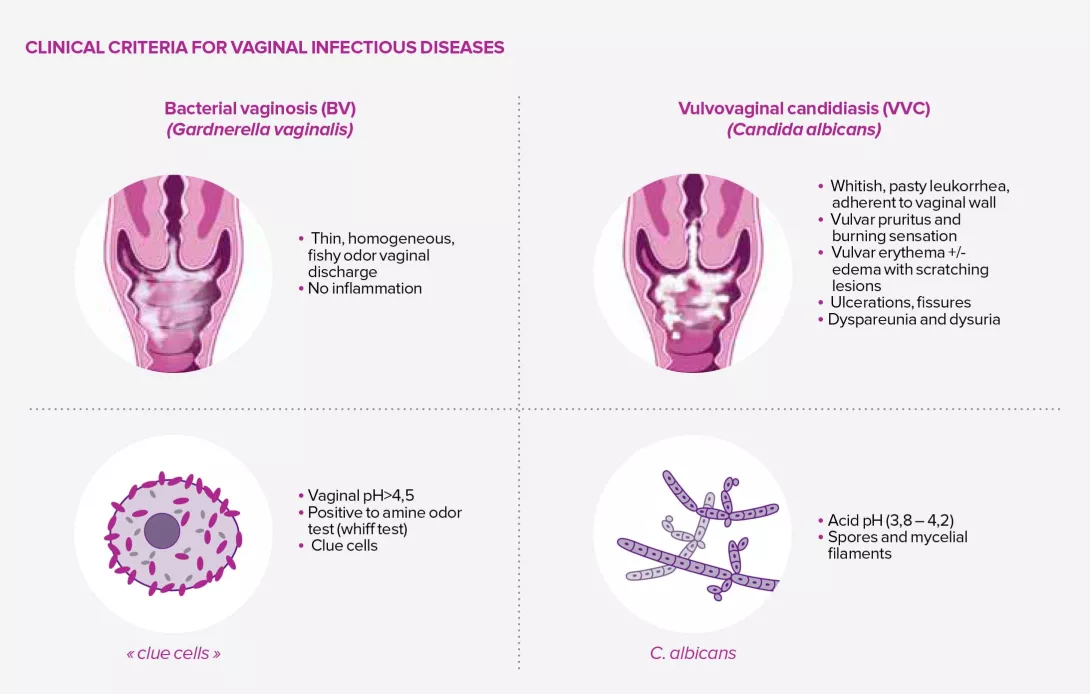
Bacterial vaginosis (BV) is the most frequently reported microbiological syndrome amongst women of reproductive age. The Amsel criteria, although controversial, remains the standard method for diagnosing bacterial vaginosis and is based on the presence of at least three of the following clinical criteria:3

  1. thin, homogeneous vaginal discharge;
  2. vaginal pH > 4.5;
  3. amine (fishy) odor on adding potassium hydroxide to a vaginal smear;
  4. presence of clue cells (cells of the vaginal epithelium to which a large number of bacteria adhere) on microscopy of vaginal secretions.

The Nugent score, a microscopic examination of a Gram stain of vaginal secretions, is also used in many countries and classifies the bacterial flora into three groups: healthy if the score is between 0 and 3, intermediate if the score is between 4 and 6, and indicative of bacterial vaginosis if the score is greater than 6. Some authors believe that BV may actually be a set of common clinical signs and symptoms caused by a wide range of pro-inflammatory bacteria, coupled with a host-dependent immune response. As a result, some experts prefer to refer to it as polymicrobial vaginosis.3

35% Only 1 in 3 women know that bacterial vaginosis is associated with an imbalance in the vaginal microbiota

Image
image1-article2-en

VULVOVAGINAL CANDIDIASIS

Vulvovaginal candidiasis (VVC), so called because it is linked to the spread of fungi (more specifically, yeasts) of the Candida genus, is considered the second most common vaginal infection after BV: 70%-75% of women are thought to have been affected at least once in their lifetime, 50% twice, and 5%-10% suffer from recurrent cases.

The symptoms and signs of vulvovaginal candidiasis are not clear, especially since colonization by the fungus is not a good indicator, with some women remaining asymptomatic despite colonization.4 The most common clinical signs are vulvar pruritus, a burning sensation accompanied by vaginal pain or irritation that may lead to dyspareunia or dysuria, and sometimes vulvar or vaginal erythema, edema, or lesions.4

Risk factors include pregnancy (and other situations where estrogen levels increase), diabetes mellitus, immunosuppression and the use of systemic antibiotics. Incidence increases with the commencement of sexual activity, but the links with different types of contraceptive remain unclear.5

Lastly, many Candida yeasts alternate between a unicellular phase and a much more virulent filamentous phase. The filamentous forms offer greater mechanical resistance, which assists the colonization and invasion of host tis- sues and confers increased resistance to phagocytosis.4

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Urology

Urinary tract infections

Infections of the lower urogenital tract are extremely common amongst women: seven out of ten women will suffer at least once from a urogenital infection or vulvovaginal candidiasis, while an even greater number will develop bacterial vaginosis at one point in their life.

The urinary microbiota The role of the vaginal, uterine and gut microbiota in endometriosis The vaginal microbiota as a predictor of the risk of premature delivery Urinary microbiota in continent women: the effect of age

Uncomplicated lower urinary tract infections are much more common amongst women than amongst men.

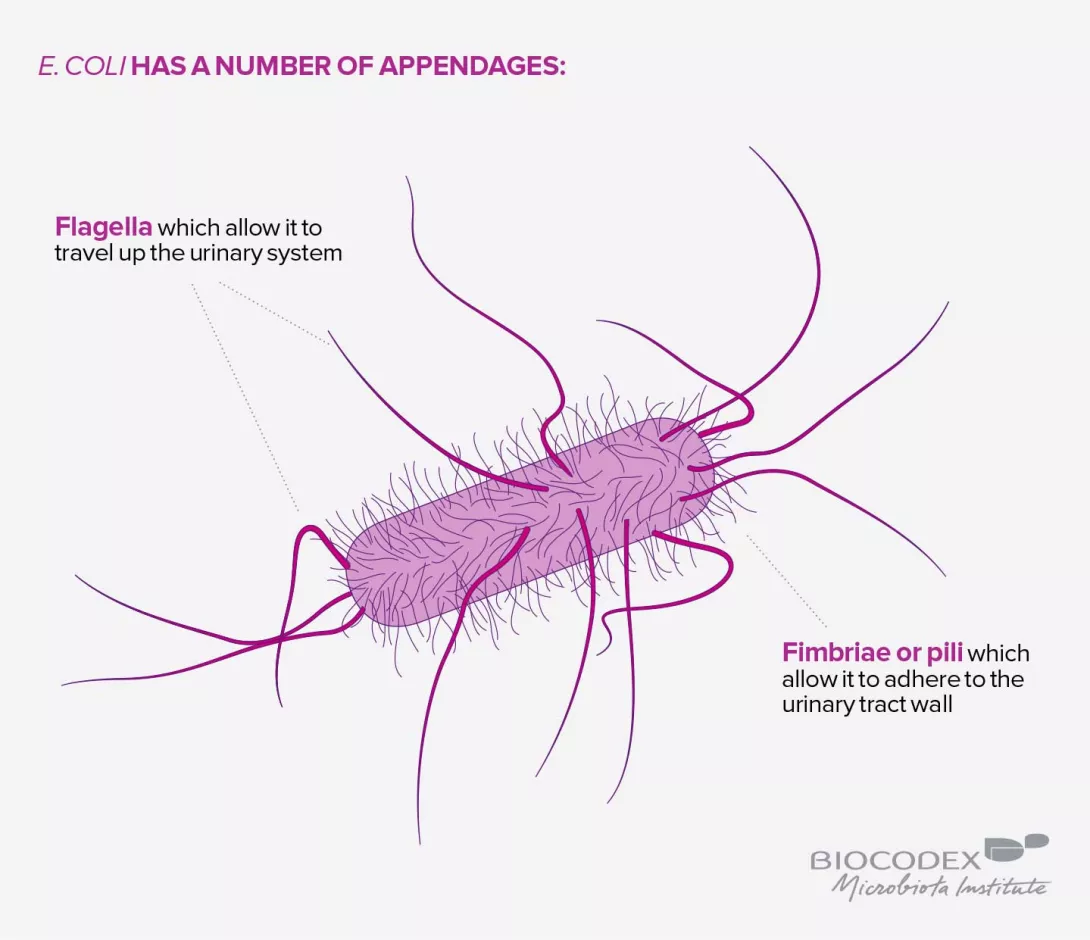
Rarely linked to a structural abnormality, they occur when a pathogen from the digestive system– often Escherichia coli–travels up the urinary tract and colonizes it.

SEVEN OUT OF TEN WOMEN

With 150 million new cases each year, urinary tract infections (UTIs) are a global health problem. A gender imbalance is evident in the case of UTIs, with women twice as susceptible as men in the same age group. One in three women is diagnosed before the age of 24, one in two before the age of 35, and up to seven out of ten once in their lifetime (30% on a recurrent basis).1

The frequency of UTIs increases with age and following two key events, the commencement of sexual activity and the menopause.2 Distinguishing complicated UTIs from uncomplicated cases is clinically important, since this will determine the duration and type of treatment. In general, uncomplicated UTIs are found in patients with no anatomical or functional abnormalities of the urinary tract, whereas complicated UTIs are more common alongside factors such as urinary tract obstructions, pregnancy, immunosuppression, fever, catheterization, renal failure, or diabetes mellitus. Prolonged symptoms (> 1 week), non-response to treatment and bacteria that persist despite treatment are also characteristic of complicated UTIs.1

Image
image1-article1-en

COLONIZATION BY DIGESTIVE SYSTEM PATHOGENS

Urinary tract infections are rarely the result of an underlying structural abnormality and are instead usually caused by a colonization of the vagina and periurethral area by uropathogens from the digestive tract which travel up the urinary tract. The virulence of pathogens, particularly E. coli, is mainly due to their adhesion capacity, which enables them to colonize the urinary system up to the point where biofilms form inside the urothelial barrier, protecting the pathogens from the host’s immune system.1

Summary
Off
Sidebar
Off
Migrated content
Activé
Updated content
Désactivé
Old content type
pro_dossiers_article
Hide image
Off
Dossier detail Urology