Parkinson’s disease is the second most common neurodegenerative disease in France. It progressively destroys the dopamine neurons in the brain. A link to a disruption in intestinal microbiota has been shown.
Parkinson’s disease affects 1% of people over 65 in France, which represents about 100,000 people. The substantia nigra in the brain, the area that controls movement, loses the neurons that produce dopamine. The result is progressive motor symptoms: slowness in movements, muscle rigidity, and tremors. People who have Parkinson’s also face non-motor problems, like sleep problems, depressive episodes, and incapacitating gastrointestinal problems (constipation, bloating, abdominal pain, nausea).
Age is implicated
The primary risk factor is obviously age. Although genetic predispositions have been proven, no single one is sufficient to explain the disease. Environment is also a factor, with pesticides playing a documented role.
Gut-brain communication
Intestinal microbiota participates in communication between the intestine and the brain. Some researchers have hypothesized that chronic intestinal infection by Helicobacter pylori could be the origin of Parkinson’s disease. However, it hasn’t been determined whether the infection triggers the disease or, on the contrary, the disease promotes the infection.
Dysbiosis, meaning a fault in the composition of microbiota, has been highlighted in patients with Parkinson’s disease. They have fewer “anti-inflammatory” bacteria and more “pro-inflammatory” bacteria than healthy people.
Controlling progression and testing
Treatment focuses on limiting the motor symptoms of the disease (tremors, rigidity, etc.) through the use of dopamine precursors. These treatments don’t prevent the progression of the disease, and complications reappear after 5 to 10 years of treatment. Currently, the primary goal is to detect the disease as early as possible and slow down neural degeneration. Manipulating microbiota is one option currently being studied.
Alzheimer's disease, whose factors are still poorly understood, still has no effective treatment. However, a hypothesis around the role of the intestinal microbiota is emerging, sparking hope for new therapeutic avenues.
Alzheimer's disease, which affects more than 35 million people around the world, is associated with memory loss, language and comprehension problems, attention and concentration problems, apraxia (loss of dexterity), and, in some cases, agnosia (problems recognizing objects or faces). Added to these cognitive symptoms, which worsen over time, are behavioral symptoms such as anxiety, apathy, irritability, sleep problems, disinhibition, and agitation.
Causes still unknown
Several genetic and environmental risk factors have been identified for the disease: hypertension, hypercholesterolemia, smoking, sedentary lifestyle, unbalanced diet, and lack of cognitive stimulation, among others. Lesions in the brain are also a well-known component of the disease, particularly the accumulation of amyloid beta plaques and neuron degeneration. However, the causes of the disease have yet to be clearly determined.
The hypothesis of intestinal microbiota
Researchers are considering whether the intestinal microbiota is involved in Alzheimer’s disease: certain proteins (amyloid peptides) produced by “negative” bacteria in the intestinal flora may favor the development of the disease. Conversely, “beneficial” bacteria may play a protective role, by slowing the formation of amyloid plaques.
Break the therapeutic deadlock
Intestinal microbiota could represent a new avenue for therapeutic research, as no current curative therapy exists for Alzheimer’s disease. Only a few medications lessen symptoms, and their effectiveness is very limited. Some researchers are, therefore, considering carrying out future work on the disease via the microbiota, through dietary changes or by ingesting probiotics.
Prostatitis is acute or chronic inflammation of the prostate. It can be caused by infection, in the case of acute inflammation. The responsible bacteria is most often Escherichia coli. Chronic pain, however, more likely implies an imbalance in the urinary microbiota.
Prostatitis affects around 10% of men. Symptoms, like in cystitis in women, include a burning sensation when urinating and the frequent need to urinate. Other symptoms may be present, such as pelvic, perianal, or rectal pain, and fever, which requires emergency treatment.
Acute prostatitis: an infectious origin?
The main bacteria responsible, Escherichia coli or other enterobacteria, come from the intestinal microbiota. Escherichia coli bacteria are implicated in 80% of cases of acute prostatitis. The infection most often starts in the urethra, which is the tube coming from the bladder. Sexually transmitted bacteria, like chlamydia or gonococci, can also cause prostatitis.
Urinary microbiota involved in chronic forms
In the case of chronic prostatitis, the origin is less clear; the bacteria are less frequently isolated. Recent studies suggest that an alteration in the urinary microbiota could play a role in the appearance of chronic prostatitis. In fact, we had long believed that urine was sterile, which is not the case. There is such a thing as the urinary microbiota. Furthermore, there is a difference in the composition of the urinary microbiota between patients with chronic prostatitis and that of healthy men. Modification of the urinary microbiota via antibiotic treatment may be the cause of chronic forms.
Antibiotic treatment
Treatment of acute prostatitis is based on the prescription of antibiotics and sometimes requires hospitalization in the event of serious symptoms. Treating chronic prostatitis remains more complicated. Probiotic options are still at a very preliminary stage.
Cystic fibrosis is a rare genetic disease that manifests through serious respiratory and digestive problems. There appears to be a connection between these symptoms and the gastrointestinal microbiota.
An estimated 105,000 people have been diagnosed with CF across 94 countries. France was the first country to introduce systematic testing at birth.
Alteration in the CFTR protein involved
Cystic fibrosis is caused by a change in the CFTR protein (Cystic fibrosis transmembrane conductance regulator), resulting from a mutation in its gene. The normal CFTR protein regulates exchanges of water and mineral salts across cell membranes. When it is defective, it leads to an increase in the viscosity of the mucus, causing it to accumulate in the respiratory and digestive tracts. This accumulation provides a foundation for bacterial infections in the respiratory tract and can eventually lead to respiratory failure. On the digestive side, cystic fibrosis leads to pancreatic insufficiency that affects digestion, the absorption of nutrients, growth, and presents with alternating diarrhea and constipation.
Imbalance in the microbiota
An imbalance in the intestinal microbiota may be associated with respiratory symptoms of cystic fibrosis. This dysbiosis, observed before the onset of the first signs, may be aggravated by the disease and accompanying antibiotic treatments. It contributes to undernutrition, growth delays, and, more generally, to digestive and respiratory complications in these patients.
Reducing symptoms
Treatment for these patients is given in specialist centers; its specific goal is to clear out the bronchi using bronchial decongestants and bronchodilators, combined with sessions of respiratory rehabilitation. Every three to four months, preventative antibiotic treatment is prescribed. Digestive problems are treated with a hypercaloric diet, supplemented with pancreatic extracts and vitamins.
In the future, new therapeutic strategies that aim to have an impact on the microbiota during the first weeks of life through nursing or the use of probiotics could delay the onset of respiratory damage, reinforce these patients’ immune systems, and, as a result, reduce the morbidity and mortality associated with cystic fibrosis.
Cold, bronchitis, strep throat... It’s hard to get through the winter without being affected by at least one of these respiratory infections. In terms of prevention, probiotic therapy may stimulate immune defenses.
Winter diseases, which are most often viral, sometimes have clinical signs very similar to the flu (Influenza virus), which is why they’re called influenza-like illnesses or flu-like symptoms.
Flu-like symptoms, often confused with flu
Flu-like symptoms include some or all of the following symptoms: fever < 38.5 C, chills, cough, fatigue, muscle ache, sore throat, headaches, runny nose, etc. Only blood tests can confirm infection with the influenza virus.
An overburdened immune system
Intestinal immune defenses protect you from attacks by pathogenic agents like bacteria and viruses. However, in winter, the immune system is attacked more often. We spend more time confined, and rooms are less well-aired. As a result, more circulating microbes are transmitted (exhaled air, coughs, sneezing).
Probiotic therapy being studied
The viral nature of winter respiratory infections immediately excludes the use of antibiotics. Treatment is symptomatic: acetaminophen, together with hydration and rest, is the basis of the medical prescription.
The use of probiotics has also been proven to be effective in clinical studies on winter respiratory diseases. The daily use of probiotics for several months reduced fever, runny nose, and coughing. It also led to a reduction in the prescription of antibiotics and the number of sick days.
The presence of a certain family of bacteria in the gut microbiota may be involved in the recurrence of Crohn’s disease following bowel resection. Can the presence of these bacteria predict recurrence?
Up to 70% of patients with Crohn’s disease undergo a bowel resection, two-thirds of whom experience a relapse requiring a further operation. The role of the microbiota associated with the intestinal mucosa in the recurrence of Crohn’s disease is well known, but there are currently few data on the luminal environment following bowel resection. A research team carried out a large randomized longitudinal prospective study on 130 patients with Crohn’s disease following surgery with the purpose to investigate the link between the intestinal microbiota and the risk of recurrence.
Enterobacteriaceae and risk of recurrence
An endoscopy was performed 6 months after surgery in two-thirds of the patients, and a colonoscopy at 18 months in all patients, in order to detect recurrence of the disease. Stool samples were taken two weeks before surgery and 6, 12 and 18 months after surgery in order to analyze the intestinal microbiota via sequencing of the 16S rRNA gene. According to the results, abundance of Enterobacteriaceae prior to surgery and 6 months after surgery is associated with an increased risk of recurrence of the disease at 18 months, whereas an increase in bacteria belonging to the Lachnospiraceae family is associated to a reduced risk. The results also showed that while the relative abundance of these bacteria families is important, increased species diversity within a family also contributes to the risk of recurrence.
An environment conducive to relapse
Following surgery, the intestinal environment is altered (exposure to oxygen, change in pH, antibiotics, etc.), leading to a decrease in Lachnospiraceae (obligate anaerobes), some species of which produce butyrate. This decrease is thought to modify the availability and metabolism of butyrate within the colonocytes, leading to a metabolic switch and an increase in oxygen, which, according to the researchers, is responsible for the proliferation of Enterobacteriaceae (facultative anaerobes). Integrating these new data with (sidenote:
De Cruz P, Kamm MA, Hamilton AL, et al. Crohn’s disease management after intestinal resection: a randomised trial. The Lancet. 2015;385(9976):1406–1417
) should provide a full understanding of the disease.
One of the main target organs for SARS-CoV-2 other than the lungs is the intestines, which also act as a potential dissemination route. Hence this review focusing on gastrointestinal disorders and the role of the gut microbiota in Covid-19 symptoms and mortality.
Although Covid-19 primarily affects the lungs, physicians and researchers have quickly focused on the role of the gut microbiota in the disease, particularly since intestinal symptoms (vomiting, nausea, diarrhea) appear to be more common in severe cases, with three meta-analyses involving around 4,000-10,000 patients reporting a prevalence of 10% to 17.6%. The infection triggers an inflammatory bowel reaction, evidenced by high fecal levels of a specific biomarker, calprotectin.
The virus is present in the digestive system
SARS-CoV-2 infects cells mainly by binding to the (sidenote:
Angiotensin-converting enzyme 2
) receptor, which is involved in the homeostasis of the renin-angiotensin-aldosterone system, crucial to the pathophysiology of all organs. ACE2 is strongly expressed in lung tissue, hence the vulnerability of this organ, but it is also expressed in the heart, liver, and intestines. The digestive system may therefore be a gateway for the virus via contaminated food. Fecal-oral transmission may follow. Actually, viral RNA is present in the stool of half of Covid-19 patients, even when the virus is absent from the respiratory tract. In addition, the virus appears capable of replicating in the gut.
Potential mechanisms
Several mechanisms may be involved in the gastrointestinal disorders observed:
• Weakening of the intestinal barrier due to local inflammation or virus replication.
• Deregulation of ACE2, whose deficiency increases gut’s susceptibility to inflammation. SARS-CoV-2 reduces the expression of ACE2 in the lungs and is likely to do so in the gut also.
• Alteration in the composition and functions of the microbiota as a result of hypoxia caused by Covid-19.
• Involvement of gut-brain axis. The enteric nervous system may be affected either via direct viral infection or through an (sidenote:
For example, inflammatory cytokines
), intensifying diarrhea and potentially stimulating the vagus nerve to provoke vomiting.
Dysbiosis of the gut microbiota
An ACE2 deficiency has been shown to alter the composition of the intestinal microbiota in mice, and Covid-19 patients develop an intestinal dysbiosis, with a loss of bacterial diversity and abundance. This dysbiosis has significant consequences: the gut microbiota can remotely stimulate the host’s response to respiratory viral infections; conversely, the dysbiosis can worsen the outcome of the disease, with reduced presence of commensal bacteria favoring the over-representation of pathogenic bacteria. Therefore, the role of the gut microbiota in Covid-19 infections remains to be determined, with the microbiota potentially constituting a biomarker of disease severity or offering therapeutic strategies.
We know that infants exposed to antibiotics are more likely to develop asthma at a later stage in life but science still struggles to explain the mechanisms behind this correlation. One clue seems to be right under our nose, or rather inside it! The nasal microbiota appears to play a central role.
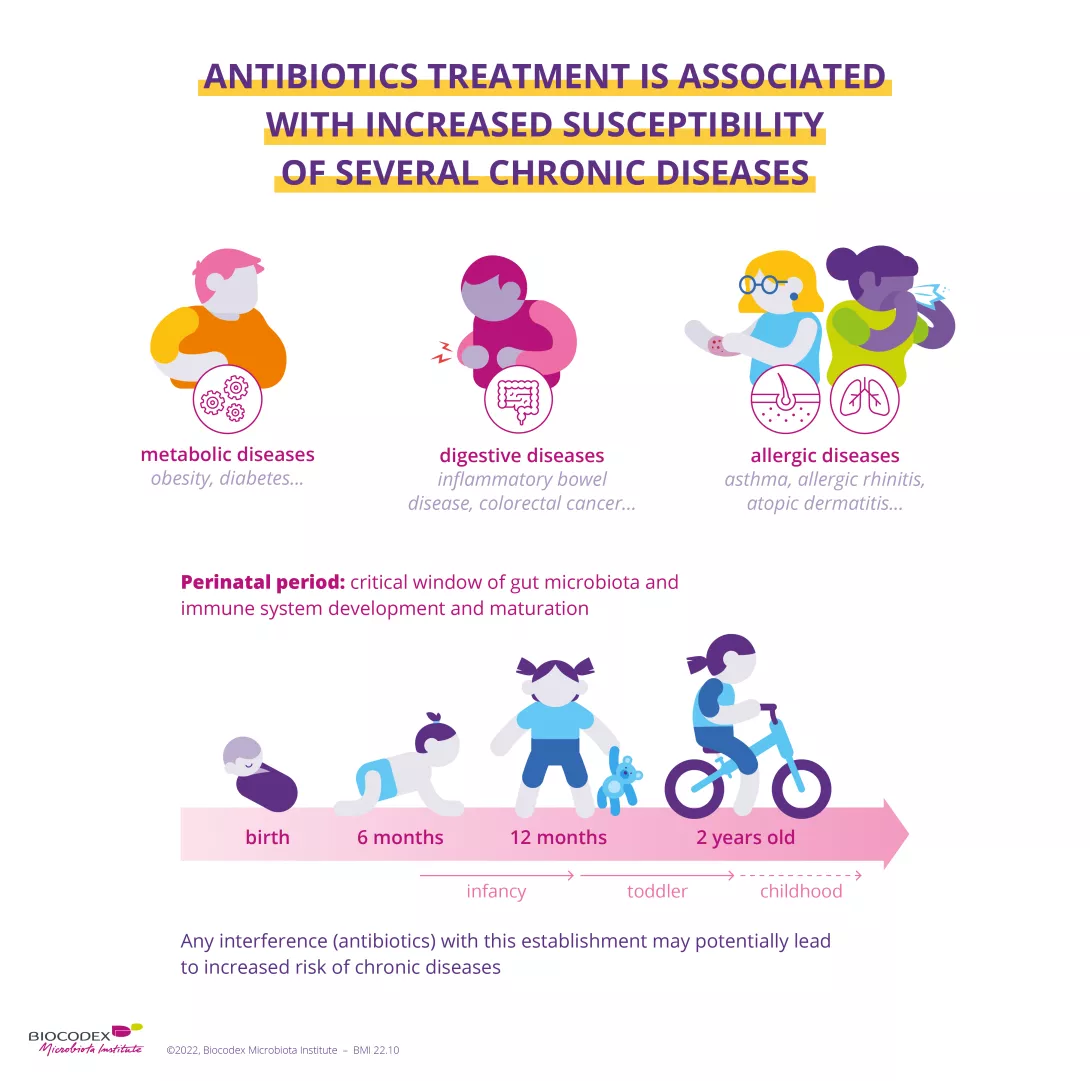
We are often told not to abuse antibiotics, but the use of antibiotics to treat conditions other than bacterial infections is still too common, with consequences for our health. Indeed, exposure to antibiotics during the first months of life may be associated with the subsequent development of asthma, an inflammatory disease of the (sidenote: https://www.who.int/news-room/q-a-detail/asthma). Alterations in the intestinal and nasal microbiota are recognized as a risk factor for the development of the disease and an indicator of its severity. Knowing that antibiotics alter bacterial communities, a team of researchers considered whether alterations of the nasal microbiota can explain the development of childhood asthma.
Image
Antibiotics save life! Did you know that they also have an impact on your microbiota? Did you know that the misuse and overuse of antibiotics can lead to antibiotic resistance? Have you heard about the World AMR Awareness Week (WAAW)? All the answers in this dedicated page:
A team studied a group of around 700 children to search for a link between antibiotic exposure before the age of one and the development of asthma at the age of seven. In total, half of the children had received antibiotics in their first eleven months and almost 8% of them subsequently developed asthma. This proportion rose to over 11% among those treated with two or more antibiotics before eleven months, an increase of 4% compared to the children not exposed to antibiotics.
The researchers observed that the nasal microbiota changes during the first two years of life and that antibiotic therapy before the age of one impacts babies’ nasal flora, with this impact growing as the number of treatments increases. In particular, the absence from the nose of Moraxella–a bacterium often associated with respiratory diseases–seemed to signal an early and significant exposure to antibiotics. Their use before the age of one may therefore have long-term harmful effects on the nasal microbiota, facilitating the cascade of events that lead to the development of asthma. Even if other factors, such as the intestinal microbiota or the immune system, are also involved, these results still support current recommendations for the prudent use of antibiotics, especially among infants.
What is the World AMR Awareness Week?
Each year, since 2015, the WHO organizes the World AMR Awareness Week (WAAW), which aims to increase awareness of global antimicrobial resistance.
Antimicrobial resistance occurs when bacteria, viruses, parasites and fungi change over time and no longer respond to medicines. As a result of drug resistance, antibiotics and other antimicrobial medicines become ineffective and infections become increasingly difficult or impossible to treat, increasing the risk of disease spread, severe illness and death.
Held on 18-24 November, this campaign encourages the general public, healthcare professionals and decision-makers to use antibiotics, antivirals, antifungals and antiparasitics carefully, to prevent the further emergence of antimicrobial resistance.
By short-circuiting the stomach or removing part of it, bariatric surgery significantly alters the gut microbiota. However, results seem to depend on the technique used.
Global prevalence of obesity almost tripled between 1975 and 2016 and now represents a major public health issue. Bariatric surgery is currently the best strategy for achieving lasting weight loss in patients suffering from morbid obesity1, with a five-year success rate of over 66%. It mainly consists of two techniques of comparable effectiveness: gastric bypass (or more precisely, laparoscopic Roux-en-Y gastric bypass) and sleeve gastrectomy, which involves removing two-thirds of the stomach. How do these interventions affect the bacterial ecosystem? Do the two approaches have the same impact?
Enriched and diversified intestinal microbiota
To find out, researchers compared two groups of around 100 patients, one subjected to gastric bypass and the other to sleeve gastrectomy. Six months later they observed a significant increase in bacterial abundance and diversity in the gut microbiota of all participants. 40% of bacteria were common to both approaches, including Akkermansia muciniphila–known to be negatively correlated with obesity–, as well as certain proteobacteria such as Escherichia coli, suspected of influencing both appetite and metabolism after surgery. However, only the gastric bypass caused a depletion of Faecalibacterium prausnitzii, a species associated with certain metabolic disorders and inflammatory bowel diseases.
Gastric bypass has a greatest impact
Both approaches also resulted in increased transport systems for vitamins B12 and B1, manganese, iron, and zinc, suggesting increased use of these nutrients by bacteria. According to the authors, the impact of gastric bypass was greater than that of sleeve gastrectomy in all aspects. However, they consider that a further three to five years will be required to establish whether these discoveries have the clinical ability to preferentially direct patients towards one treatment or the other.
1. Morbid obesity is defined by a body mass index (BMI) of over 40
Farin W, Oñate FP, Plassais J, et al. Impact of laparoscopic Roux-en-Y gastric bypass and sleeve gastrectomy on gut microbiota: a metagenomic comparative analysis [published online ahead of print, 2020 Mar 20]. Surg Obes Relat Dis. 2020;S1550-7289(20)30132-5. doi:10.1016/j.soard.2020.03.014
Inflammatory bowel diseases (IBDs) include Crohn’s disease and ulcerative colitis. These diseases don’t have an effect on life expectancy, but they do significantly alter quality of life. Treatment plans are starting to target microbiota.
IBDs, Crohn’s disease and ulcerative colitis (UC), are characterized by inflammation in the wall of part of the digestive tract, which is related to hyperactivity of the digestive immune system. During IBD flares, the most common symptoms are abdominal pain and diarrhea, which can sometimes be hemorrhagic. These diseases can also present signs in systems outside the digestive tract, including joints and the ophthalmic, cutaneous, and hepatic systems.
IBDs affect 1 person in every 1000 in Western Europe and most often appear between 20 and 40 years of age. These illnesses follow intermittent courses, with alternating periods of flares and remission. In Crohn’s disease, this inflammation can be localized at all stages of the digestive system, from the mouth to the anus, although it is most often found in the intestine. Ulcerative colitis is localized in the rectum and colon.
Multifactorial disorders
The causes of IBDs include genetic predisposition, environmental factors like pollution and diet, the immune system, and intestinal microbiota. IBDs may also be caused by a lack of exposure to microorganisms during childhood due to an excessive hygiene, for example.
Modified intestinal content
Intestinal microbiota seems to play an important yet still poorly understood role in the characteristic inflammation of IBDs. Numerous studies have observed dysbiosis in these patients, i.e. a change in the microbiota equilibrium, linked to genetic and environmental factors. Anti-inflammatory bacteria in particular are weakened. This imbalance changes the content of the intestine and can lead to chronic inflammation.
Hope for treatment
There is no curative therapy, but anti-inflammatories can limit painful flares. Treatment currently includes corticosteroid therapy, treatments called “immunomodulators” that can reduce the immune system’s reactions, like anti-TNFα, and surgery in 80% of Crohn’s cases and 20% of UC. It rarely provides a definitive cure. Researchers are currently trying to target the role of microbiota in IBDs, trying to reduce the presence of pathogens and boost the growth of good microorganisms.