Microbial colonization as a determinant factor for health during the first 1000 days of life

By Pr. Marie-Claire Arrieta
Departments of Physiology and Pharmacology & Pediatrics, Cumming School of Medicine, University of Calgary, Health Research Innovation Centre, Calgary, Alberta, Canada

The infant's gut at the heart of immunity
Microbiota mag 17_bandeau synthèse

Epidemiological and mechanistic studies during the past 20 years have demonstrated a role for the early-life microbiome in the pathogenesis of several non-communicable diseases (NCDs). This collection of trillions of microorganisms, residing mainly in the intestines, engages in a dynamic crosstalk with host cells. It is through this crosstalk that the host integrates microbial metabolites and structures to the early programming of immune, neurologic, metabolic and endocrine mechanisms that support host development. While this crosstalk occurs throughout life, there is a non‐redundant period in early development, known as a “window of opportunity”, during which microbial-host crosstalk sets the stage for host homeostasis, or deviations from it. This period lasts approximately 1,000 days, encompassing fetal growth and the first two years of human life, and it is at the center of intense investigation.

COMPOSITION AND FUNCTION OF THE EARLY-LIFE MICROBIOME

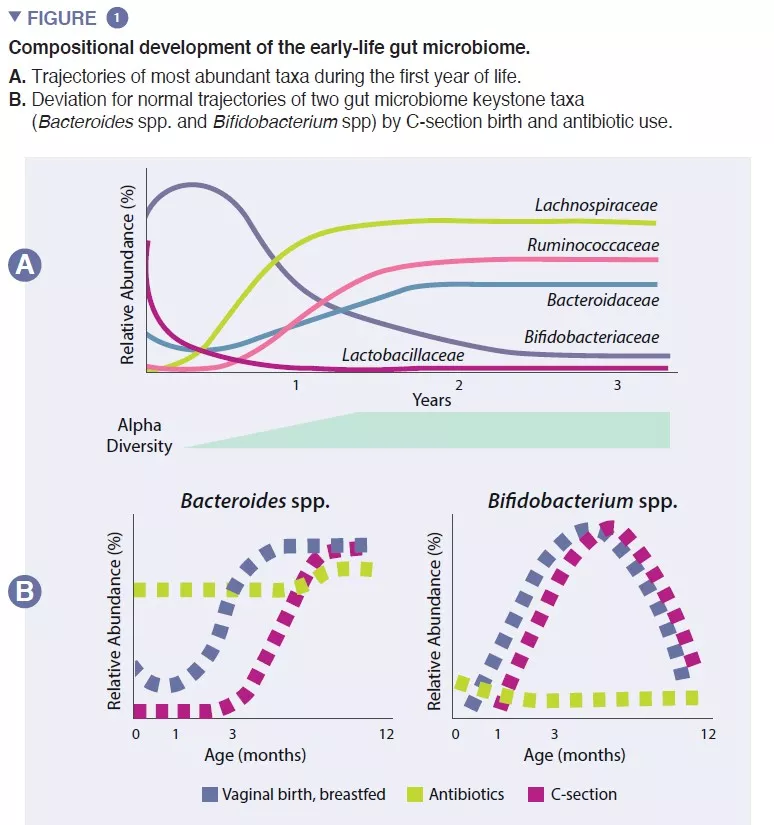
The infant gut microbiome starts developing at birth as a very simple ecosystem, gaining species diversity for about 2-3 years (box 1). This process occurs in a stepwise fashion, with common patterns identified across several human populations (Figure 1). Early colonization starts with pioneer species that primarily originate from the vaginal canal and maternal feces or the skin, depending on whether the infant is delivered vaginally or by Cesarean (C)-section, respectively. Vaginally-born exhibit higher abundance in Lactobacillus, Prevotella, and Sneathia, while those born by C-section are initially colonized by Staphylococcus, Propionibacterium, and Corynebacterium. Breastfed infants exhibit increased abundance of Bifidobacterium sp. and Lactobacillus sp., compared to formula fed infants, which display increased abundance of Bacteroides, Enterobacteriaceae and Clostridiaceae. As solid foods are introduced, the gut microbiome becomes increasingly diverse and shifts towards a state of Bacteroidaceae, Lachnospiraceae, and Ruminococcaceae dominance that persists into adulthood (Figure 1) [1].
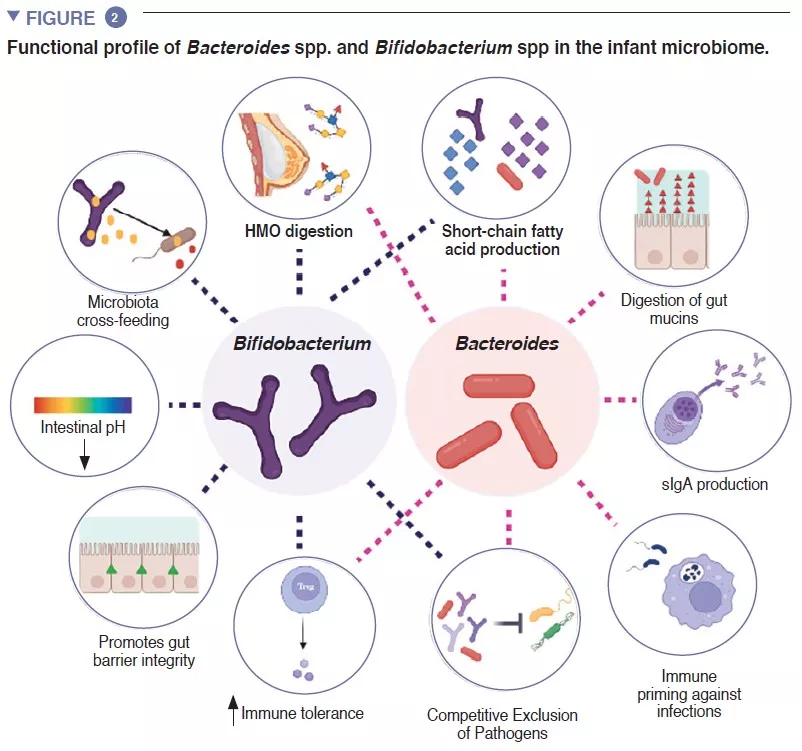
The infant gut is stage of an important metabolism that contributes to digestion, energy metabolism and immune education. Through microbial digestion of breastmilk components, Bifidobacterium species decrease the intestinal luminal pH through the production of lactate and acetate, which is considered a crucial strategy in increasing intestinal nutrient absorption. Acetate accounts for the majority of the short-chain fatty acids (SCFA) produced in the infant gut, and is involved in preventing infections with enteropathogens [2]. Bifidobacteria are also involved in a process known as cross-feeding, in which the production of acetate and lactate serves as substrates for the growth of other species, such as Roseburia, Eubacterium, Faecalibacterium, and Anaeroestipes, favoring microbiome diversity. Bacteroides species can also ferment breastmilk, and are important producers of the SCFA propionate. Bacteroides species have a unique capacity to also metabolize mucin-derived oligosaccharides [3]. This metabolic plasticity improves their adaptability to the fluctuating intestinal conditions between meals, as well after weaning and introduction of solid foods. Bacteroides species are also key for immune education, constituting an important source of the microbial component lipopolysaccharide, as well as prompting for the development of tolerogenic adaptive immune responses in the gut [4]. Given their special adaptability to the infant gut environment, their demonstrated mother-to-infant strain transmission, their dominance in the infant gut, their importance to other members of this microbial ecosystem, and the benefits to the host, both Bacteroides spp. and Bifidobacterium spp. are likely keystone species of the human infant microbiome (Figure 2).
FACTORS THAT SUSTAIN THE EARLY-LIFE MICROBIOME

Early pioneer species can have long-lasting consequences to the trajectory of the infant gut microbiome through priority effects. This ecological process dictates that early arrival to a new ecosystem plays a fundamental role in the assembly of the community. This process explains the influence of mode of birth on the initial composition of the infant microbiome. Large cohort studies have identified microbiome differences linked to C-section delivery that last for months after birth, likely impacting this critical period in host development [5]. These include a lower of abundance of Bacteroides and Bifidobacterium spp., as well as an increased abundance of potential pathogenic species.

Besides mode of birth, the availability and abundance of nutritional substrates imposes a determinant effect on the early-life microbiome. Breastmilk contains more than 10 g/L of human milk oligosaccharides (HMOs), with 2’fucosyl lactose (2’FL) and trifucosyllacto-N-hexaose (TF-LNH) as the most abundant HMOs [6]. The majority of HMOs are digested by bifidobacterial and Bacteroides spp. into SCFAs. Bifidobacteria have a large repertoire of genes for the digestion of HMOs. Several subspecies of B. longum are commonly found in the infant gut, with B. longum subsp. infantis (B. infantis), B. longum subsp. longum (B. longum), and B. longum subsp. breve (B. breve) commonly isolated from healthy breastfed infant feces, and formula-fed infants often colonized with B. adolescentis. Of these subspecies, B. infantis has the largest gene repertoire to digest all HMO structures in human milk [7]. Breastmilk also influences the composition of the infant microbiome through immune factors, such as antimicrobial compounds (lactoferrin and lysozyme), as well as immune effectors (sIgA, immune cells, and cytokines), which are critical for the immune exclusion of pathogenic microbes [1]. Notably, the lower abundance of Bifidobacterium in formula-fed babies is associated with a lower concentration of lactate, sIgA, and a higher gut luminal pH compared to breastfed babies.

Besides mode of birth and infant nutrition, other factors, such as maternal smoking, maternal body mass index, gestational diabetes, familial asthma and stress can influence the early-life microbiome [8]. The mechanisms underlying the associations between these factors and the infant microbiome remain unclear, but likely involve changes to the maternal microbiome and subsequent vertical transmission to the infant, as well as the increased risk of C-section rate and reduced success in breastfeeding linked to many of these factors. In general, the individual effects of factors such as birth mode, antibiotic use, and breastfeeding are relatively well characterized. However, the combinatory effects of these exposures remain poorly understood.

Is the infant colonized in utero?

  • Microbial DNA has been detected in the placenta, amniotic fluid and meconium, prompting for the speculation of in utero colonization.
  • Failure to culture microbes detected in utero, the consistent effect of mode of birth on the microbiome, and the successful generation of germ-free animals from embryos have led to the current consensus that healthy newborns start microbial colonization at birth [15].

EARLY-LIFE DYSBIOSIS AS A CAUSE OF NONCOMMUNICABLE DISEASES

As a young ecosystem, the early-life microbiome is inherently less resilient. Ecological resilience refers to the capacity of an ecosystem to revert back to its original state after a perturbance occurs. This places the infant microbiome at a higher risk of permanently altering its trajectory during a critical developmental stage. Peri- and post-natal antibiotic use induce drastic compositional and diversity shifts to the infant microbiome, known as dysbiosis, decreasing the abundance of bifidobacteria and overall microbiome diversity, and increasing pathogenic species. This effect is observed even when antibiotics are only given to the mothers during vaginal birth (to prevent B-Streptococcus infections), and is augmented when given to infants during the first year of life, in a dose response manner [9]. Notably, even a single course of amoxicillin to infants decreased bifidobacterial abundance for several months, highlighting the susceptibility of this important group of bacteria to these commonly used drugs [10].

Antibiotic exposure during gestation or in the pre-weaning stage of rodents can exacerbate allergic immune responses (IgE, Th2 and Th17 lymphocytes), adiposity and obesity, autoimmune responses, and chronic colitis [1]. These systemic responses to early-life dysbiosis are in line with consistent epidemiological findings associating early-life antibiotic use with several NCDs. For example, a systematic review and metanalysis of 13 studies identified a dose-response association between antibiotic use and obesity, which ranged between an 11% increased risk for infants receiving only one dose, to a 24% increased risk with more than one treatment [9]. More recently, a systematic review and metanalysis of 160 studies, encompassing over 22 million children, revealed significant associations between pediatric antibiotic use and atopic dermatitis, food allergies, allergic rhinoconjuntivitis, asthma, juvenile arthritis, psoriasis and autism spectrum disorder [11].

Establishing directionality and causality from epidemiological studies is very difficult. However, the combined results of preclinical studies, with the consistent and dose-response associations between antibiotic use with asthma and obesity, in particular, support for the application of more strict antibiotic stewardship measures. A recent study in Canadian children reported a parallel decrease in asthma incidence as antibiotic prescriptions decreased at the population level between the years 2000 and 2014. Importantly, the microbiome composition at 1 year of age mediated the association between antibiotic exposure and asthma diagnosis at five years [12]. This important study provides strong evidence for a causal relationship between antibiotic use and asthma in humans and reveals the need for a prudent antibiotic use as a strategy to reduce asthma rates.

RESTORING DYSBIOSIS – ARE WE THERE YET?

The detrimental consequences of early-life dysbiosis warrants further study, but also action. Decreasing C-section rates, formula feeding and antibiotic prescriptions, while a worthy goal, have limited potential as successful strategies given societal needs. Several avenues of microbiome restoration have been attempted, with mixed results. Two methods of ecosystem restoration have been tested in planned C-section deliveries: vaginal seeding and fecal microbiota transplantation (FMT). Vaginal seeding involves impregnating the skin and/or oral cavity of a newborn with collected maternal vaginal secretions. The three vaginal seeding trials currently published showed that this method does not restore the C-section microbiota into one resembling that of a vaginal birth [8]. In contrast, a mother-to-infant FMT (given once during the first feed) was sufficient to correct the C-section microbiome [13]. However, while authors carried out pathogen screening in the FMT samples, this controversial practice carries significant and unnecessary infectious risk to an otherwise healthy newborn infant, and it is unlikely to become a viable option.

The use of pre- and probiotics may provide a more practical and feasible approach to microbiome restoration, especially when informed from the studies summarized above. A recent study showed that depletion of bifidobacteria and HMO-utilizing genes could be ameliorated through the combination of administration of a strain of B. infantis and breast feeding [14]. This strategy also dampened pro-inflammatory responses conducive to allergy at 1-year, showing long-term beneficial immune mechanisms. Still, there is insufficient evidence that current microbiome restoration strategies will help curve the alarming rates of pediatric NCDs.

Conclusion

The early-life microbiome is an integral component of child health. Our knowledge on the compositional and functional patterns of early colonization, as well as the factors sustaining or perturbing these patterns has grown considerably. In contrast, the mechanisms that explain how dysbiosis contributes to disease pathogenesis are poorly understood. Ecologicallyinformed measures to replenish keystone species of the infant microbiome lost through antibiotic use, C-section of formula feeding, as well as their nutritional substrates, may prove as effective measures. However, current microbiome restoration strategies are insufficient, and have yet to show effectivity in reducing the risk of NCDs. This is the next crucial step to prompt changes in medical policies and practices.

Sources

1. Laforest-Lapointe I, Arrieta MC. Patterns of Early-Life Gut Microbial Colonization during Human Immune Development: An Ecological Perspective. Front Immunol 2017; 8: 788.
2. Fukuda S, Toh H, Hase K, et al. Bifidobacteria can protect from enteropathogenic infection through production of acetate. Nature 2011; 469: 543-7.
3. Sonnenburg JL, Xu J, Leip DD, et al. Glycan foraging in vivo by an intestine-adapted bacterial symbiont. Science 2005; 307: 1955-9.
4. Telesford KM, Yan W, Ochoa-Reparaz J, et al. A commensal symbiotic factor derived from Bacteroides fragilis promotes human CD39(+)Foxp3(+) T cells and Treg function. Gut Microbes 2015; 6: 234-42.
5. Penders J, Thijs C, Vink C, et al. Factors influencing the composition of the intestinal microbiota in early infancy. Pediatrics 2006; 118: 511-21.
6. Thurl S, Munzert M, Boehm G, et al. Systematic review of the concentrations of oligosaccharides in human milk. Nutr Rev 2017; 75: 920-33.
7. Underwood MA, German JB, Lebrilla CB, et al. Bifidobacterium longum subspecies infantis: champion colonizer of the infant gut. Pediatr Res 2015; 77: 229-35.
8. Korpela K, de Vos WM. Infant gut microbiota restoration: state of the art. Gut Microbes 2022; 14: 2118811.
9. Mc- Donnell L, Gilkes A, Ashworth M, et al. Association between antibiotics and gut microbiome dysbiosis in children: systematic review and meta-analysis. Gut Microbes 2021; 13: 1-18.
10. Korpela K, Salonen A, Saxen H, et al. Antibiotics in early life associate with specific gut microbiota signatures in a prospective longitudinal infant cohort. Pediatr Res 2020; 88: 438-43.
11. Duong QA, Pittet LF, Curtis N, et al. Antibiotic exposure and adverse long-term health outcomes in children: A systematic review and meta-analysis. J Infect 2022; 85: 213-300.
12. Patrick DM, Sbihi H, Dai DLY, et al. Decreasing antibiotic use, the gut microbiota, and asthma incidence in children: evidence from population-based and prospective cohort studies. Lancet Respir Med 2020; 8: 1094-105.
13. Korpela K, Helve O, Kolho KL, et al. Maternal Fecal Microbiota Transplantation in Cesarean-Born Infants Rapidly Restores Normal Gut Microbial Development: A Proof-of-Concept Study. Cell 2020; 183: 324-34.e5.
14. Henrick BM, Rodriguez L, Lakshmikanth T, et al. Bifidobacteria-mediated immune system imprinting early in life. Cell 2021; 184: 3884-98.e11.
15. Perez-Muñoz ME, Arrieta MC, Ramer-Tait AE, et al. A critical assessment of the “sterile womb” and “in utero colonization” hypotheses: implications for research on the pioneer infant microbiome. Microbiome 2017; 5: 48.
Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Gastroenterology Pediatrics

Insomnia in seniors: a link with the gut microbiota

While it is estimated that one in two seniors suffers from chronic insomnia, a recent study1 demonstrates a link between sleep, cognition, and the gut microbiota in elderly insomniac individuals.

Difficulty in falling asleep or in staying asleep, waking up early... insomnia affects one in two adults over 65 years of age. With serious consequences for health since this chronic disorder is often accompanied by cognitive decline and increased mortality. Although the mechanisms are still poorly understood, an explanation of the link between insomnia and cognitive decline could lie in the gut microbiota-brain axis. A team of researchers therefore studied the links between the gut microbiota and the cognitive performance of 72 chronic insomniacs (of which 56 were women) with an average age of 73.2 years. Two factors were assessed, which generally testify to an accelerated cognitive decline during aging: sleep quality (objective measurement by (sidenote: Actigraphy Objective method of measuring sleep based on a device similar to a watch, worn on the wrist or ankle, which detects movements of the body and therefore waking activity. This apparatus thus measures the time taken to fall asleep, any periods of wakefulness and their duration, etc. ) over 2 weeks and subjective measurement by self-questionnaire) and cognitive performance (15 variables measured including 2 finally retained as being more discriminating).

50% Insomnia affects around 50% of the adult population over 65 years of age.

Sleep quality associated with intestinal dysbiosis

Analysis of stool samples of patients by sequencing of the 16S rRNA gene demonstrates the presence of 45 different phyla. Bacteroidetes were predominant (48%), followed by Firmicutes and, a long way behind, Proteobacteria (6 %), that is a decrease in Firmicutes and Proteobacteria in favor of the Bacteroidetes in comparison with patients without sleep problems2.

But above all, in the 72 insomniacs monitored, sleep efficacy (that is objective sleep not perceived sleep) and cognition explained 7.5 to 7.9% of the total variation in the composition of the gut microbiota (in terms of (sidenote: Amplicon Sequence Variant (ASV) Term designating individual DNA sequences recovered from a marker gene analysis (“parasite” sequences induced by gene amplification and sequencing are eliminated by this technique). This method is therefore distinguished from OTU counts, (Operational Taxonomic Unit), more commonly used, where bacteria are grouped together based on similarities of a given gene serving as a taxonomic marker. ) ). That is a significant impact, comparable to that caused by medicines, blood parameters, intestinal transit, diet, state of health, and anthropometric data, according to a previous study3.

Lachnoclostridium and Blautia involved?

In addition, the correlation analysis showed that a strong presence of the genus Lachnoclostridium went together with effective sleep and higher cognitive performance (shorter response time). Conversely, decreased cognitive performance was associated with greater abundance of the genus Blautia.
This study provides a new building block in the relationship between insomnia, cognition, and the gut microbiota. Although it does not allow any causality to be inferred, it points the finger at the gut microbiota as a potential aid to the diagnosis of elderly persons suffering from sleep disorders and cognitive decline, even as a new therapeutic target in the field of aging.

Recommended by our community

"True!" - DOKI DE LAGOS (From Biocodex Microbiota Institute on X)

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Gastroenterology General Medicine

Periods & vaginal microbiota: Science in progress…

Recent scientific publications have provided new data highlighting the key role of the vaginal microbiota on women’s health. Biocodex Microbiota Institute is launching a set of expert interviews dedicated to microbiota, women and health. What do we already know about woman’s health and microbiota? What do we still have to discover? 

Second act: the menstrual cycle and the vaginal microbiota. Prof. Ina Schuppe Koistinen, microbiome researcher, tells us everything!

The vaginal microbiota Vaginal yeast infection Bacterial vaginosis - vaginal microbiota imbalance The gut microbiota What foods promote a balanced microbiota?
Periods & vaginal microbiota: Science in progress…

52% Only 1 in 2 women know that the vagina is self-cleaning

What is exactly the vaginal microbiota and what is its role?

Prof. Ina Schuppe Koistinen: The vaginal microbiota is defined as the complex ecosystem of (sidenote: Microorganisms Living organisms too small to see with the naked eye. This includes bacteria, viruses, fungi, archaea, protozoa, etc., collectively known as ’microbes’. Source: What is microbiology? Microbiology Society. ) , including bacteria, virus and fungi, that live inside the vagina and has biologically evolved to help protect the female reproductive system. 

The vaginal microbiota

Learn more

Unlike in the gut, a healthy vaginal microbiota has low diversity and is dominated by Lactobacillus species. Lactobacilli protect the vagina from overgrowth of other organisms by keeping the vaginal pH low by production of lactic acid, production of antimicrobials such as H2O2 and bacteriocins. They also compete for nutrients, adhere tightly to the mucosal membrane and modulate the local immune system.

How does the vaginal microbiota change during the menstrual cycle? 

I. S.-K.: We know that a healthy vaginal microbiota is resilient to changes such as menstruations, sexual activities and hormonal fluctuations. For most but not all women, the vaginal microbiota remains relatively stable during periods. Menstrual blood, increases pH and adds nutrients to vaginal bacteria like Gardnerella or Prevotella that are associated to an unbalanced vaginal microbiota (what we call a (sidenote: Dysbiosis Generally defined as an alteration in the composition and function of the microbiota caused by a combination of environmental and individual-specific factors. Levy M, Kolodziejczyk AA, Thaiss CA, et al. Dysbiosis and the immune system. Nat Rev Immunol. 2017;17(4):219-232.   ) ).

So, there is an effect during bleeding when the vaginal microbiota gets more diverse1 but normally, it will recover when the menstrual phase is over (that’s what we call “resilience”).

Do hygienic protections impact my vaginal microbiota?

I. S.-K.: There is little scientific data on the link between menstruation, hygienic protection method and the vaginal microbiota. We don’t know at this point if hygienic protections influence it’s composition. It is truly critical because half of the female population (around 26% of the global population2) are of reproductive age and concerned, but no large cohort studies have already compared different hygienic protections: tampon, pad, menstrual cup or absorbent pantie. In an ongoing research study, in Sweden we investigate the impact of hygienic protection on the vaginal microbiota of 2000 women. I can’t wait to see the results.

Periods: don’t underestimate the power of your diet!

Many women describe having gastrointestinal (GI) symptoms throughout their periods (bloating, abdominal pain, diarrhea…). Did you know that a healthy diet can relieve a painful digestive system associated with menstruation? Vegetables, fruits and fermented foods rich in Bifidobacteria and Lactobacilli, food rich in fibers and with anti-inflammatory properties can be beneficial for your gut microbiota. Perfect moment to test kimchi and sauerkraut if you are still not convinced!

Is there a link between painful periods and microbiota?

I. S.-K.: Once again, unfortunately there is very little research on that topic. In a study from Sweden3, 50% of adolescent girls reported pain during their periods, almost 40% severe pain. Research has shown that women with period pain have high levels of prostaglandins, hormones known to cause cramping abdominal pain.

50% of adolescent girls reported pain during their periods.

At this point, we don’t know if the microbiota is involved. We have to enhance research because girls have always been told that it is normal to have period pain. But it is not normal! We have to investigate factors associated with menstrual pain to relieve women and improve the diagnosis of endometriosis. According to Forbes, only 4% of all R&D funding in Pharma is dedicated to specific women’s health issues which is quite discouraging… I’m convinced that we need to raise awareness on this topic, it’s my mission!

Is there any risk of increased vaginal infections during the menstrual cycle? Is it linked to my microbiota? 

I. S.-K.: The risk of vaginal infections (Candida infections or bacterial vaginosis) increases during periods and this is linked to the vaginal microbiota. As I have already explained, the menstrual blood creates an environment that favors the growth of pathogenic bacteria, leading to (sidenote: Dysbiosis Generally defined as an alteration in the composition and function of the microbiota caused by a combination of environmental and individual-specific factors. Levy M, Kolodziejczyk AA, Thaiss CA, et al. Dysbiosis and the immune system. Nat Rev Immunol. 2017;17(4):219-232.   ) .

72 million women around the world have to manage their periods without a decent toilet.

According to (sidenote: Sources ) , 72 million women around the world have to manage their periods without a decent toilet. In addition, women may not be able to afford hygiene protection and are at increased risk for infections. Both resources and education are needed to improve the situation.

Sex during periods: does it have an impact on the vaginal microbiota and the risk of infections?

I. S.-K.: Having sex during periods is totally fine, but if your vaginal microbiota is more susceptible to dysbiosis, the use of condoms is recommended. All sex practices where body fluids are exchanged can worsen the vaginal dysbiosis. A dysbiotic vaginal microbiota makes you more susceptible to sexually transmitted infections by bacteria, such as chlamydia and gonorrhea, and viruses, such as human papillomavirus (HPV) or HIV4-6. 

Any advice on how to take care of your vaginal microbiota during periods? 

I. S.-K.: The first advice I will give is that every woman should choose the product she is comfortable with. It will help her to manage her periods in a good way, to feel comfortable and safe. It is important to choose a product that matches your blood flow.

Then, there are very simple rules to follow: change your tampon or your menstrual cup (you need to sterilize it before insertion) every 4-6 hours to limit the risk for (sidenote: Toxic-shock syndrome This is a rare but life-threatening condition caused by bacteria getting into the body and releasing harmful toxins, and associated with tampon and or cup use. Sources. ) 7. Wash your hands before inserting your hygienic protection, avoid tampons or pads with perfume and other kinds of chemicals. Your vagina cleans itself with its own discharge, there is no need for vaginal douching. Wash your vulva with lukewarm water, a soap-free cleaning solution or perfume free oils and do not use antimicrobials that can disturb your microbiota. Practice safe sex and be nice to your vulva and vagina, not too much soap and perfume, that is the best advice I can give!

Discover Prof. Ina Schuppe Koistinen's interview:

Image
Periods - Pr. Ina Schuppe Koistinen - Youtube (EN)
BMI 22.55

Recommended by our community

"I think this is a good idea to post because could read it in the privacy of your own home with nobody around" - Louis Strong (From My health, my microbiota)

Don't miss the other episodes

Menopause: new insights coming from microbiota?

Discover it now

Does microbiota play a role in infertility?

Discover it now
Summary
On
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News

Urethral microbiota: a better understanding of male urinary tract infections

Urethritis is generally caused by well-known bacteria. These include gonococci, responsible for the dreaded “clap.” However, the urinary tract has its own microbiota which has yet to be explored! This is how researchers discovered1 other bacteria potentially involved in this urinary tract infection in men, which differ according to sexual orientation.

The urinary microbiota
 Microbiote urétral : des infections urinaires masculines mieux comprises

Urethritis is an inflammation of the (sidenote: Urethra The tube that carries urine from the bladder and out of the person’s body. ) , the tube through which urine leaves the bladder. In men, it manifests as a burning sensation on urination, with itching and abnormal discharge. It can be caused by a sexually transmitted infection (STI) triggered by a bacterium, usually Neisseria gonorrhoeae (gonococcus), and sometimes Chlamydia trachomatis or Mycoplasma genitalium, or less commonly by viruses such as herpes. However, up to half of cases of non-gonococcal urethritis are considered “idiopathic,” meaning we do not know what caused them. Either the urethritis is not infectious, which is rare, or the pathogen responsible is not identified. If in doubt, doctors usually prescribe an antibiotic. But this type of non-targeted approach can result in inadequate or excessive treatment, which can in turn alter the microbiota.

Close-up on the urethral microbiota of men with idiopathic urethritis

Recent studies also suggest that the infectious agents responsible for non-gonococcal urethritis in men who have sex with women (MSW) are not the same as in those who have sex with men (MSM). Australian researchers therefore sought to determine which bacteria, apart from those already known, might contribute to infection in humans, taking into account their sexual practices. To do so, they analyzed the urethral and urinary microbiota of around one hundred men (MSW and MSM) with symptoms of idiopathic urethritis and compared them to around one hundred men without urethritis, as “control” subjects.

What is non-gonococcal urethritis?

Non-gonococcal urethritis is a sexually transmitted infection (STI). It is characterized by inflammation of the urethra with symptoms that include burning sensations on urination, itching, and abnormal discharge from the penis. The infection can be caused by a variety of bacteria, and less commonly by viruses. Non-gonococcal urethritis is not caused by gonorrhea.2

(Bacterial) genus and sexual orientation issues

Scientists found that the bacterium Haemophilus influenzae, which naturally colonizes the microbiota of the nasopharynx (in other words, the nose and throat), was more abundant in the urethral microbiota of MSM with idiopathic urethritis. The researchers believe that this infection may be transmitted by the act of having oral sex without a condom. The scientists found more of the bacterial genus Corynebacterium in affected MSW, which was surprising because it is considered normal in male genital microbiota. The authors suggest that some of these species may become pathogenic on multiplying. Other bacterial genera such as Ureaplasma, Escherichia, some streptococci and a staphylococcus were also more abundant in the urinary and urethral microbiota of the affected men. The scientists believe they may also promote urethritis.

Hope for more targeted treatments for male urethritis

The discovery of these new bacteria brings hope for patients. Thanks to these new bacteria, researchers can now identify possible causes of non-gonococcal infectious urethritis based on the sexual orientation of patients. If these results are confirmed, doctors could offer their patients more targeted treatments. A small step for science, a giant leap for sexually transmitted infections (STIs)?

The urinary microbiota

Learn more
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Off

Pregnancy: is vaginal dysbiosis responsible for complications in case of COVID-19?

Contracting COVID-19 during pregnancy increases the risk of complications, all the more so if the infection is severe. A study highlights the role of vaginal dysbiosis in this relationship.

Pregnancy: is vaginal dysbiosis responsible for complications in case of COVID-19?

35% Only 1 in 3 said their doctor had ever taught them what the vaginal microbiota was and what it was used for

Faced with COVID-19, pregnant women present an increased risk of developing a severe form and pregnancy complications, such as preeclampsia or premature birth. Well, the role played by a balanced vaginal microbiota in the optimal progression of pregnancy is known. And what if the harmful effects of COVID-19 in pregnant women required the intervention of the vaginal microbiota?
In order to check this hypothesis, researchers conducted a prospective case-control study including 28 non-infected pregnant women and 19 pregnant women suffering from COVID-19 (13 mild or even asymptomatic cases and 6 moderate to severe cases, including 2 that required the taking of antibiotics and antivirals).

More diversity and fewer lactobacilli among the COVID-19 pregnancies

A sample of the vaginal microbiota was obtained with a swab during the active phase of the disease in the month following recovery and evaluated by 16S rRNA gene sequencing. The COVID-19 group displayed significantly greater diversity than the control group. In addition, the Bacteroidetes had gained the upper hand over the Firmicutes, and, at bacterial genus level, the Lactobacillus sp. were significantly less abundant than in the control group. Well, previous studies showed that there was an increased risk of miscarriage or premature birth in pregnant women whose vaginal microbiota were depleted in Lactobacilli. These data corroborate this finding, since 3 women in the COVID-19 group gave birth prematurely (versus 0 in the control group).

Is the severity of COVID-19 related to vaginal dysbiosis?

Despite the small size of the sample, the investigators observed other differences in the composition of the vaginal microbiota in the COVID-19 group. In particular, the women suffering from moderate to severe forms of COVID-19 displayed much higher levels of Ureaplasma spp.: 2.05% vs 0.1% in case of asymptomatic to mild forms. The genus Ureaplasma is involved in different gynecological infections (salpingitis, urethritis, and cervicitis), its over-representation in case of severe COVID-19 also argues in favor of an association of vaginal dysbiosis both with SARS-Cov-2 infection and risks of pregnancy complications. All the more as, in the 3 premature births that occurred in this study, 2 were in the moderate to severe COVID-19 subgroup (n=6).

Thus, although this study does not allow the conclusion that a causal relationship exists, these results suggest that COVID-19 may trigger an unfavorable disruption of the vaginal microenvironment in pregnant women. This would be even more pronounced when the infection is severe, and could lead to an increased risk of complications, such as premature birth.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News

Xpeer course: The rationale behind why and how to choose a probiotic

Get free training on decision-making for choosing a probiotic from Mary Ellen Sanders, a consultant in probiotic microbiology. Delve into this course based on clinical recommendations and provide your patients with the best approach. Learn more!

Image

Synopsis of the course

In recent years, probiotics have gained enormous scientific relevance, as there has been an increasing number of studies supporting probiotic health benefits beyond the digestive tract, including oral, liver, skin, vaginal and urinary tract health. However, not all probiotics are the same. The decision of choosing a probiotic should be based on clinical recommendations based on their efficacy to treat certain pathologies. Among a wide variety of probiotic products, how to choose one? And why? This course will give you the clues and rationale behind selecting a probiotic. Moreover, do not miss the opportunity of learning from a renowned expert some misconceptions and practical recommendations regarding probiotics use!
 

Who is Mary Ellen Sanders?

  • Mary Ellen Sanders, PhD, is an internationally recognized consultant in the area of probiotic microbiology.
  • She was the founding president and is currently the executive science officer of the scientific society, ISAPP. Dr. Sanders has authored over 120 peer-reviewed, scientific publications on efficacy substantiation, microbiology and regulatory issues pertaining to probiotics. Since 2017, She is Chair of the United States Pharmacopeia’s Probiotics Expert Panel and o-Chair of World Gastroenterology Organisation Committee preparing practice guidelines for the use of probiotics and prebiotics for GI indications.
  • Conflicts of Interest Statement: The author declares receiving consulting fees by California Dairy Research Foundation, Church & Dwight, Mead Johnson, and PepsiCo; giving presentations in conferences sponsored by Kerry, Associated British Foods, Mead Johnson, Fairlife, GlaxoSmithKline, Trouw Nutrition, and serving on advisory boards for Cargill, Sanofi, Danone North America, Danone Research, Winclove Probiotics, and Yakult.

What is Xpeer?

Xpeer Medical Education is the first accredited medical education app in the market, with video microlearning engaging videos of just 5 minutes.

With a powerful algorithm to personalize the user experience and the contents as the most popular entertaining streaming platforms, it offers a brand new experience for the continuing education and professional development of the healthcare professionals.

Accredited by the European Union of Medical Specialists, it delivers high quality scientific medical education pieces. On Xpeer, you will find this curriculum on Microbiota and 500 hours of medical education in 2023 in your specialty, technologies and professional and personal skills.

Information on accreditation

The app Xpeer is accredited by the European Accreditation Council for Continuing Medical Education (EACCME) to provide official ECMEC credits recognized officially in 26 countries.

The credits for the users of the module will be 1 European CME credit (ECMEC®) for every hour (60 minutes of actual e-learning excluding introductions etc.) of use, provided that the users have completed a module and have passed the relevant assessment.

Recommended by our community

"I will be deeply interested in this course"  -@huutrong69 (From Biocodex Microbiota Institute on X)

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Off

Almonds: little effect on the gut microbiota

Finally, arguments supporting the health benefits of almonds will perhaps need to be revised downwards. For, against all expectations, a recent study showed that 2 snacks of almonds had little effect on the gut microbiota.

The gut microbiota

There is no doubt, diet is the most effective means of modulating the composition of our gut microbiota. But studies are often limited to one nutrient (the effect of a protein, fiber, etc.) without evaluating the effect of the whole foodstuff. Well, all nutrients in a foodstuff interact, with antagonistic and synergistic effects, so much so that in real life, the overall effect of a foodstuff is rarely the sum of the individual effects of each of its components. Thus, almonds, as all seeds, are rich in lipids and therefore in calories (incidentally oil is extracted from them!) but also in fibers which act on intestinal transit, in polyphenols with anti-aging properties, etc.

To evaluate the effects of almonds on the gut microbiota, American almond producers have just funded a study which represents, in terms of quality, the Holy Grail in nutrition: a (sidenote: Randomized trial Study in which the products tested are distributed randomly, between the participants. ) (sidenote: Controlled trial a study in which participants are given either a test product (capsule containing the active compound) or a placebo (control capsule not containing the active compound), thus allowing for comparison. ) . Thus, 87 young volunteers little inclined to eat fruit and vegetables were distributed randomly between 3 comparable groups. Their mission: to consume, every day for 4 weeks, two snacks in place of their usual snacks, comprising either 2 handfuls of whole almonds, or the equivalent in ground almonds, or 2 muffins with the same calorie content (controls).

26 g of almonds = around 20 almonds (1 handful)

Disappointing results, limited health benefits

The least that can be said, is that the results observed will not have matched the level of investment. The authors hoped to observe that the almonds had a boosting effect on the intestinal (sidenote: Bifidobacterium A genus of Y-shaped bacteria, most species of which are beneficial to humans. They are found in the gut of humans, and in some yogurts.

They:
- Protect the gut barrier 
- Participate in the development of the immune system and help fight inflammation 
- Promote digestion and improve symptoms of gastrointestinal disorders Sung V, D'Amico F, Cabana MD, et al. Lactobacillus reuteri to Treat Infant Colic: A Meta-analysis. Pediatrics. 2018 Jan;141(1):e20171811.  O'Callaghan A, van Sinderen D. Bifidobacteria and Their Role as Members of the Human Gut Microbiota. Front Microbiol. 2016 Jun 15;7:925. Ruiz L, Delgado S, Ruas-Madiedo P, et al. Bifidobacteria and Their Molecular Communication with the Immune System. Front Microbiol. 2017 Dec 4;8:2345.
)
. Well, rather the opposite happened... They wagered on an accelerated intestinal transit due to the fibers present in the almonds: but no, the oily nuts changed nothing. The study even called into question a principle accepted up until then by nutritionists, namely that, unlike finely ground almonds, whole almonds would continue, even after mastication, to retain the lipid droplets in their structure. Well, the results show that the commercial grinding of almonds produces practically no differences in terms of lipid accessibility. In other words, your body will be able to assimilate the fats and calories of whole almonds, practically as well as those of ground almonds.

The exception: a short-chain fatty acid

Only one positive note was observed: the consumption of almonds (whole and ground) led to a significant increase in the production, by the gut bacteria, of a (sidenote: Short chain fatty acids (SGFA) Short chain fatty acids are a source of energy (fuel) for an individual’s cells. They interact with the immune system and are implicated in communication between the gut and the brain.   Silva YP, Bernardi A, Frozza RL. The Role of Short-Chain Fatty Acids From Gut Microbiota in Gut-Brain Communication. Front Endocrinol (Lausanne). 2020;11:25. ) beneficial to our health, butyrate.

Sources

Creedon AC, Dimidi E, Hung ES et al. The Impact of Almonds and Almond Processing On Gastrointestinal Physiology, Luminal Microbiology and Gastrointestinal Symptoms: a Randomized Controlled Trial and Mastication Study. Am J Clin Nutr. 2022 Sep 20:nqac265.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Off

Almonds: limited effects on the gut microbiota

Against all expectations, the consumption of almonds seems to have no effect on the gut microbiota and intestinal transit. The only benefit observed: a rise in the level of butyrate which saves the day for the funders of the study.

The almond producers of California have once again treated themselves to the Holy Grail of studies: a randomized controlled trial (RCT). Aim: to evaluate the impact of almonds and of their transformation (ground or not) on intestinal bifidobacteria and, secondarily, on the overall composition of the gut microbiota and intestinal transit time. To do this, 87 adults in good health, avid snackers (crisps, chocolate, etc.) and little inclined to consume fiber (fruit, vegetables, etc.), took part in this 3-arm trial: over 4 weeks, they replaced their 2 usual snacks either by whole almonds (2*23 g/d), or by ground almonds (2+23 g/d) or by 2 muffins with the same calorie content (control).

26 g of almonds = around 20 almonds (1 handful)

Almonds: the end of a nutritional myth?

Outcome? Contrary to the main hypothesis, bifidobacteria were not more abundant in the stools of the whole almond (8.7%) or ground almond (7.8 %) groups compared with the control (13.0 %), the opposite was the case. Nevertheless, the slight difference does not withstand an adjustment to the test. Almonds also have no effect on the gut microbiota, intestinal transit time (which the researchers thought was accelerated), stool consistency or intestinal symptoms. The particle size of ground almonds was finer than that of almonds after mastication: for all that, the effect of grinding on the release of lipids and therefore their accessibility by the organism proved smaller than anticipated, to the point that the researchers concluded that the commercial grinding of almonds does not lead to clinically significant differences in terms of nutrient bioaccessibility.
The only significant difference observed: the consumption of almonds (whole and ground) led to an increase in the production of butyrate by the gut bacteria (24.1 μmol/g vs 18.2 μmol/g for the control), a short-chain fatty acid with recognized health benefits, which, according to the authors would suggest a modification of the functions of the gut microbiota. 

No prebiotic effect 

It is without doubt a disappointment for the American producers but, according to this RCT, the consumption of almonds does not exert a prebiotic effect on the fecal bifidobacteria, produce major changes in the microbiota, or affect transit. Could the predominance of women (86.2%) and young people (27.5 ± 6.2 years) in the volunteers have biased the results? Perhaps. In the meantime, other studies are expected targeting a more uniform population to confirm these results. 

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Gastroenterology

Fat, sugar, and metabolic disease: links between the gut microbiota and immunity

We already knew that too much fat and sugar promotes obesity and type 2 diabetes. Now we also know that the gut microbiota and its immune system play a role in regulating the metabolism. Deciphering the mechanisms involved has been no small task, but researchers have recently succeeded in doing so1, revealing the major role played by excessive sugar.

The gut microbiota

It’s all common sense. Often too rich in fat and sugar, the “ (sidenote: Western diet Diet rich in processed foods, refined sugar, salt, saturated fats (red meats) and trans fats (pastries) Zinöcker MK, Lindseth IA. The Western Diet-Microbiome-Host Interaction and Its Role in Metabolic Disease. Nutrients. 2018 Mar 17;10(3):365.  ) ” diet has an impact on our health. It tends to increase inflammation in the body and to disrupt the metabolism. It can thus lead to obesity, type 2 diabetes, and metabolic syndrome. Numerous studies have shown that the gut microbiota and its immune system play a major role in metabolic balance, with disturbances in the gut converting excess food into extra pounds and serious illnesses.

More fat and sugar means less gut immune cells to balance the metabolism 

To better understand these disturbances, researchers fed mice a diet rich in fat and sugar for four weeks. As expected, in addition to gaining more weight than mice fed normally, these overfed mice also developed a (sidenote: Metabolic syndrome Combination of several metabolic anomalies: high blood pressure, large waist circumference, increased blood triglyceride and glucose levels associated to a low blood level of “good” cholesterol. Alberti KG, Zimmet P, Shaw J. The metabolic syndrome--a new worldwide definition. Lancet. 2005 ; 366 (9491) : 1059-62. ) . An analysis of the mice’s gut flora via their droppings showed that this diet caused a rapid loss of (sidenote: Segmented filamentous bacteria Segmented filamentous bacteria (SFB) are bacteria of the Clostridiaceae family that colonize the gut of many vertebrate and invertebrate animals without causing an inflammatory response. On the contrary, their presence is thought to stimulate the immune response. They help in the differentiation and maturation of certain defense cells and promote the elimination of pathogenic microbes.  Hedblom GA, Reiland HA, Sylte MJ, et al. Segmented filamentous bacteria–metabolism meets immunity. Frontiers in microbiology. 2018 Aug 24;9:1991.  https://www.frontiersin.org/articles/10.3389/fmicb.2018.01991/full   ) . This in turn reduced the production of (sidenote: T helper 17 (Th17) cells Th17 cells are immune system cells that play a role in host defense against pathogens, particularly at epithelial barriers, such as the gut barrier. Awasthi A, Kuchroo VK (2009) Th17 cells: From precursors to players in inflammation and infection. Int Immunol 21:489–498. ) , subsequent to which the metabolic syndrome appeared. 

The researchers found that Th17 cells regulate the absorption of lipids in the gut and are necessary for protection against metabolic syndrome. The loss of Th17 cells is thus to blame for the adverse health effects of a diet high in fat and sugar. By administering segmented filamentous bacteria to the overfed mice, Th17 production was restored. As a result, the mice lost weight and their metabolism improved.

Sugar, the metabolism’s worst enemy 

But which is most to blame, too much fat or too much sugar? The effects of a diet rich in fat and sugar (including sucrose and maltodextrin, common in candy and soda) were compared with those of a diet rich in fat but low in sugar. The researchers found that sugar on its own modifies the composition of the gut microbiota to the detriment of the segmented filamentous bacteria that stimulate Th17 cells. So would it be enough to eliminate sugar from the diet to ensure protection against metabolic disease? Not entirely, according to the researchers, since protection also requires the presence of the Th17 cells produced by the gut microbiota.

In short, metabolic syndrome, obesity, and type 2 diabetes are the result of complex interactions between diet, the gut microbiota, and immunity. According to the researchers, there is no “universal” diet that would produce the desired effect in everyone. Instead, a personalized approach to metabolic disorders is required. In the future, such approaches could take into account inter-individual differences in the gut microbiota’s immune system.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Off