Does the gut microbiota influence vaccine efficacy?

Some children treated with vaccines fail to develop protective immunity, especially in low- and middle-income countries. The gut microbiota is intimately linked to immune function and may be one of the factors responsible for this variability in vaccine response.

Vaccines are one of the greatest successes of public health, saving millions of lives worldwide, especially among young children (0-5 years), who are more vulnerable to infectious diseases. However, their efficacy varies from one population to another, with higher rates of protective immunity in European countries than in low- and middle-income countries (LMIC). Since the development of the gut microbiota in early life is intimately linked to the maturation of the immune system, and the microbiota of children in LMIC differ significantly from those of European children, researchers reviewed the evidence pointing to the gut microbiota’s role in disparities in vaccine response.

Immunomodulatory properties

A study on vaccines against tuberculosis, tetanus, hepatitis B, and poliomyelitis in Bangladeshi infants found that the presence of certain taxa is correlated with the rate of vaccine response, positively in the case of Actinobacteria, but negatively for Enterobacteriaceae. In addition, interventions to modify the microbiota (prebiotics, probiotics, antibiotics) provide further evidence of its involvement in vaccine response. A 2018 systematic review summarized the results of 26 studies in humans that used probiotics to enhance the efficacy of various vaccines. The review found positive outcomes in half the studies. Conversely, studies investigating the effects of antibiotics found either no improvement or a reduced immune response, which was attributed to disruption of the microbiota.

Two bacterial genera especially involved 

Two bacterial genera seem particularly capable of modulating responses to vaccines. Bifidobacterium and Bacteroides are essential for the development of a healthy microbiota in young children. However, young children can face significant microbiota disruptions (cesarean section, etc.). The effects of the microbiota on vaccine responses appear to be mediated by certain metabolites and/or cellular components, such as short-chain fatty acids, exopolysaccharides, or extracellular vesicles.

Towards a new generation of vaccine strategies

Although the relevant strains and products need to be better characterized, the intricate relationship between the microbiota and vaccine efficacy opens up rich clinical perspectives. This includes new vaccine stimulation therapies able to improve protection for children from LMIC without the use of adjuvants, which are often thought to have adverse side effects.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Pediatrics

Microplastics in takeaway food put gut and oral flora at risk

However well balanced, takeaway food has consequences for our health. The packaging in which takeaway food is served contains microplastics that impact our microbiota.

Plastic takeaway packaging releases microplastics and nanoplastics that may have a significant impact on the gut and oral microbiota.

Harmful effects on humans remain under-investigated

A study carried out in 2020 showed that plastic food containers made from polypropylene (PP), polystyrene (PS), polyethylene (PE), and polyethylene terephthalate (PET) all contain micro- and nanoplastics. Although the harmful effects of these particles on the microbiota have been demonstrated in animals (fish, shrimp, and mice), until now they have been under-investigated in humans.

Researchers analyzed and compared the gut and oral microbiota of 390 Chinese students aged between 18 and 30 who consumed takeaway food served in plastic packaging either frequently (at least three times a week), occasionally (once a week or less), or never. 

The scientists also created three groups of mice which, for five weeks, were given either a solution of microplastics at 5 mg/ml (20 mice), a solution of nanoplastics at 5 mg/ml (20 mice), or a solution of the same nanoplastics but at 2 mg/ml (20 mice). A control group of 15 mice was also established.

Disruption of microbial balance

The results show that consumers of takeaway food in plastic containers more frequently suffer from gut disorders and coughs than those who never consume such food. They also presented a dysbiosis of the gut and oral microbiota with specific bacterial signatures. The gut microbiota of occasional consumers was strongly associated with the presence of Faecalibacterium, while that of heavy consumers was associated with Collinsella. For the oral microbiota, the bacteria most strongly associated with heavy consumers was Thiobacillus.

Significant impact even with smaller particles and at low doses

The study on mice showed that all the animals fed with plastic particles presented a gut dysbiosis when compared to the control group. Changes in the size (i.e. micro- vs. nanoplastics) or quantity (5 mg/ml vs. 2 mg/ml) of the particles ingested had no effect on their impact.

Moreover, the researchers believe that the recurrent cough in takeaway lovers may mean that micro- and nanoplastics are able to migrate from the gut to the lungs, where they accumulate in the airway microbiota, causing a dysbiosis that leads to the cough. Although yet to be confirmed, these results are one more reason to switch to a glass lunch-box.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Gastroenterology

Can the gut microbiota help improve vaccine efficacy?

The gut microbiota differs from one person to another. These differences may explain variations in vaccine efficacy, with children from low- and middle-income countries showing poorer responses. Researchers are looking for ways to modify gut microbiota composition in the hope of addressing this “immune inequality”.

The gut microbiota

In theory, vaccines work on a simple (or fairly simple) principle: they (sidenote: To do this, a harmless fragment of the invader is inoculated into the host so that it develops targeted defenses. When the real pathogen subsequently appears, our defenses are ready to neutralize it.  https://www.who.int/news-room/feature-stories/detail/how-do-vaccines-work ) However, in practice, vaccines do not always work. They save millions of lives each year, especially among young children who are more vulnerable to infectious disease, but they are more effective in European children than in children from low- and middle-income countries (LMIC). Although treated with vaccines, (sidenote: While nearly 100% of Finnish children develop protective immunity in response to rotavirus vaccines, this is the case for only 58% of children in Nicaragua and 46% of children in Bangladesh. Similarly, protection rates for the BCG vaccine range from 0%-51% in African children versus 88%-100% in European children. ) In other words, the army of antibodies that makes up their (sidenote: Innate and adaptive immunity  The human body protects itself using two kinds of defense mechanisms: innate immunity and adaptive immunity. Innate immunity is the first line of defense against disease agents and is an immediate response, while adaptive immunity is delayed but provides lasting protection Janeway CA Jr, Travers P, Walport M, et al. Immunobiology: The Immune System in Health and Disease. 5th edition. New York: Garland Science; 2001. Principles of innate and adaptive immunity. ) fails to respond. Untrained to recognize and eradicate the enemy, they are unlikely to be able to defend the host in a real battle. But what causes this “immune inequality”?

Gut microbiota, an ally of immune response

The answer may involve a special third force allied with the immune army, the gut microbiota. The development and functioning of the gut microbiota and immune system are intimately linked; but the gut microbiota of European children differs significantly from that of children from LMIC. The researchers thus believe that differences in microbiota composition may explain variations in vaccine response. Accordingly, certain studies have sought to modify the gut microbiota in order to improve immune response. Trials in humans that used probiotics (live bacteria that strengthen the microbiota) to increase the proportion of patients who develop protective immunity have shown positive outcomes in half of cases. Two sentries of the gut microbiota, the bacterial genera (sidenote: Bifidobacterium A genus of Y-shaped bacteria, most species of which are beneficial to humans. They are found in the gut of humans, and in some yogurts.

They:
- Protect the gut barrier 
- Participate in the development of the immune system and help fight inflammation 
- Promote digestion and improve symptoms of gastrointestinal disorders Sung V, D'Amico F, Cabana MD, et al. Lactobacillus reuteri to Treat Infant Colic: A Meta-analysis. Pediatrics. 2018 Jan;141(1):e20171811.  O'Callaghan A, van Sinderen D. Bifidobacteria and Their Role as Members of the Human Gut Microbiota. Front Microbiol. 2016 Jun 15;7:925. Ruiz L, Delgado S, Ruas-Madiedo P, et al. Bifidobacteria and Their Molecular Communication with the Immune System. Front Microbiol. 2017 Dec 4;8:2345.
)
and Bacteroides, seem particularly capable of rallying the immune system’s troops.

Improving vaccine response

Although further research is required, the researchers are already considering new vaccine strategies that involve the modulation of gut flora composition in the hope of stimulating responses to vaccines. This new approach may increase access to effective vaccines in low- and middle-income countries (LMIC). It may also make it possible to do without certain adjuvants that are added to boost immune responses, but which are thought to have adverse side effects that fuel vaccine hesitancy.

Sources

Jordan A, Carding SR, Hall LJ. The early-life gut microbiome and vaccine efficacy. Lancet Microbe. 2022 Oct;3(10):e787-e794. doi: 10.1016/S2666-5247(22)00185-9.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News

Microplastics: beware of takeaway food packaging and their impact on the microbiota!

A study by Chinese researchers suggests that plastic particles from takeaway food packaging may alter the gut and oral microbiota.

The gut microbiota

Only half an hour to eat? Think twice before grabbing fried noodles at your local snack bar... especially if they come in plastic packaging. According to a recent study, the microplastics and nanoplastics in these disposable containers may disrupt your gut and oral microbiota.1

Microplastics and nanoplastics are everywhere!

Resistant, light, cheap... plastic has many advantages. However, plastic can degrade, generating tiny particles that disperse through the air and water, into animals’ bodies, and ultimately into our own bodies via our plates. Microplastics measure less than 5 mm and can be found throughout the body, including in the lungs, placenta, and blood. On the other hand, nanoplastics are not well studied, since they measure less than 100 nm (500 times less than the thickness of a human hair) and are more difficult to detect. Although little is known about their effects on humans, they are still a cause for concern. Not only can they cross the body’s biological barriers, but the additives they contain, considered chemical pollutants, may promote illnesses such as cancer and some forms of inflammatory bowel disease (IBD).2,3

Microbiota imbalance: plastic in the dock

We know that takeaway food packaging releases significant amounts of small plastic particles. Tests on animals fed with these micro- and nanoplastics show an adverse impact on the animals’ gut microbiota. But how do they affect human health?

To answer this question, researchers enrolled 390 Chinese students aged between 18 and 30 and put them into three groups: heavy consumers of takeaway food in plastic packaging (at least three times per week), occasional consumers (maximum once per week), and non-consumers. They collected stool and saliva samples in order to analyze and compare their oral and gut microbiota.

Significant impact on balance of gut and oral flora

The results show that consumers of takeaway food in plastic containers suffer more gut disorders and cough than those who never consume such food. More worryingly, they show significant alterations ( (sidenote: Dysbiosis Generally defined as an alteration in the composition and function of the microbiota caused by a combination of environmental and individual-specific factors. Levy M, Kolodziejczyk AA, Thaiss CA, et al. Dysbiosis and the immune system. Nat Rev Immunol. 2017;17(4):219-232.   ) ) in their gut and oral microbiota. These have specific bacterial signatures, such as higher quantities of Collinsella in their stools and higher quantities of Thiobacillus (previously found in rice fields polluted by plastic) in their mouths.

Opening simple plastic package is far from harmless

A study by Australian researchers4 has shown that cutting, tearing, twisting, or simply handling a piece of adhesive tape, a chocolate wrapper, or a shopping bag may release potentially toxic microplastics. The study has shown that, depending on the type of the packaging and the opening technique, between 0.46 and 250 microplastic particles are released for every centimeter cut, torn, or twisted.

Particles able to pass between body compartments?

The authors suggest that coughing, which was more frequent in the takeaway food eaters, may result from micro- and nanoplastics that migrate from the gut to the lungs, where they accumulate in the airway microbiota, leading to dysbiosis. 

These results have yet to be confirmed, but in the meantime, consider preparing your own snacks and, above all, carry them in a (more stable) glass container.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Off

Can gut bacteria and metabolites help the earlier prediction of necrotizing enterocolitis in newborns?

Could certain gut bacteria and three short-chain fatty acids provide a simple, reliable, and early prediction method for neonatal necrotizing enterocolitis? So suggests a study involving 34 premature babies.

NEC

Identify early and intervene as soon as possible. This is the key to managing neonatal necrotizing enterocolitis (NEC), which affects between 5% and 12% of premature babies. However, due to a lack of sufficiently sensitive biomarkers in newborns, this remains wishful thinking. Nonetheless, previous studies have shown the appearance of a gut dysbiosis in the 7 days to 72 hours preceding NEC. Can the microbiota and its metabolites – particularly short-chain fatty acids (SCFAs) involved in maintaining the integrity of the intestinal epithelium – predict NEC?

34 preterm infants with digestive disorders

To explore the predictive value of the gut microbiota and SCFAs, a prospective study was conducted in 34 preterm infants (gestational age less than 34 weeks) suffering from gut disorders (bloating, vomiting, or bloody stools). 17 of the infants were suspected of having NEC and 17 were matched controls without NEC whose stools were collected on the enrollment day. Of the 17 infants suspected of having NEC, (sidenote: Gut perforation The remaining 5 children showed gut perforation on the day of enrollment in the study. ) (a subgroup of the original matched sample), whose stool was collected seven days later on average.

5% and 12% of premature babies Between 5% and 12% of premature babies develop necrotizing enterocolitis (NEC)

20%-30% of infants In 20%-30% of infants this results in death.

Gut dysbiosis precedes NEC

Contrary to the results of previous studies, the researchers did not systematically observe a loss of gut diversity prior to the disease: some indices of bacterial richness (Ace and Chao1) showed a significant difference, while others (Simpson and Shannon) did not. According to the authors, the digestive disorders present in all children in the study (including the controls) may explain this discrepancy with the data from the literature.

Conversely, seven days before the onset of NEC, a change in the composition of the flora was noted: the bacterial species Streptococcus salivarius and Rothia mucilaginosa increased, while Bifidobacterium subsp. lactis decreased. Variations at phylum level (increase in Proteobacteria, decrease in Firmicutes, Actinobacteriota, and Bacteroidota) were also explored, but the differences were not deemed significant.

Three SCFAs as metabolic markers

The researchers also looked at bacterial metabolites, specifically acetate, propionate, and butyrate, which represent 90%-95% of total SCFAs in the human gut. The study showed that these three SCFAs decreased significantly seven days before the onset of NEC, probably due to the decrease in Firmicutes and Bacteroidota. These metabolites proved to be much better predictive biomarkers for NEC than the bacterial biomarkers. More specific and sensitive (AUC of 68%-73%, depending on the SCFA), in the future they may have a clinical application.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Pediatrics Gastroenterology

Exposure to air pollution disturbs the microbiota of babies

Would going green protect our children from lung and cardiovascular diseases?
According to a study published in Gut Microbes, air pollution significantly alters the microbiota of babies, potentially impacting their future health.

The gut microbiota The pulmonary microbiota
Exposure to air pollution disturbs the microbiota of babies

Road transport, factories, wood heating... It has long been known that air pollution adversely affects lung and cardiovascular health. Indeed, recent studies have shown that it alters the microbiota of adults. But what impact do air pollutants have on the microbiota of babies?

To answer this question, scientists from the University of Colorado Boulder (USA) measured air pollutant exposure levels in 103 Californian children aged six months. They also collected stool samples to analyze the composition of their microbiota.

9 out of 10 people According to the WHO, 9 out of 10 people breathe polluted air.

7 million This pollution is responsible for 7 million deaths each year.

Serious microbiota disturbances

The scientists found that, after adjusting for potential confounders such as birthweight, socioeconomic status, mode of delivery, and breast or formula feeding, the more newborns are exposed to air pollution, the greater the changes to the composition of their microbiota.

Air pollution: a major public health issue

Residential heating, road transport, construction sites, industry, and quarries are the main sources of air pollution. They are responsible for emissions of toxic particulate matter (PM) and nitrogen dioxide (NO2). Fine particles can pass through the body’s protective membranes and affect the heart, lungs, and brain. 

Children are particularly sensitive to air pollution. Among children, air pollution can lead to respiratory diseases, cancer, and cognitive disorders.

The microbiota of the most exposed babies contained more Dialister and Dorea, two bacterial genera associated, in adults, with systemic inflammation and a higher risk of cancer, multiple sclerosis, and mental health disorders.

Their microbiota also contained fewer bacteria that produce short-chain fatty acids ( (sidenote: AGCC Acides gras à chaîne courte ) ), which are known to have beneficial effects on gut barrier integrity, cardiovascular health, gut-brain communication, and the (sidenote: Blood-brain barrier The blood-brain barrier is a “physical” barrier that separates the central nervous system (CNS) from the bloodstream. It tightly controls exchanges between the blood and the brain compartment. 
Engelhard HH, Arnone GD, Mehta AI, Nicholas MK. Biology of the blood-brain and blood-brain tumor barriers. InHandbook of Brain Tumor Chemotherapy, Molecular Therapeutics, and Immunotherapy 2018 Jan 1 (pp. 113-125). Academic Press. https://www.sciencedirect.com/science/article/pii/B9780128121009000085
)
. 

Understanding the effects of pollution on microbial communities

This study highlights for the first time an association between exposure to ambient air pollution and the gut flora composition of young children. Although concerning, these results still need to be confirmed and completed by further studies. As a next step, researchers should follow changes in the children’s microbiota over time, try to identify the mechanisms by which pollution exerts its effects on microbial communities, and find out whether the changes are really associated with health problems.

Gut microbiota: why is it that important for your health?

Learn more
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Off

Your IBS Diagnosis Check List

How many patients suffering from gut disorders do you see per week? How many are diagnosed with irritable bowel syndrome (IBS)? Do you know that some patients struggled more than 4 years before receiving a formal medical diagnosis of IBS?

Up to 75% of individuals with Irritable Bowel Syndrome (IBS) may be undiagnosed.  As a complex disorder driven by multiple factors with symptoms that can overlap with those of other gastrointestinal diseases and disorders, diagnosing IBS can be challenging.

To help, Prof. Jean-Marc Sabaté, Prof. Jan Tack, Dr. Pedro Costa Moreira, in collaboration with the Biocodex Microbiota Institute, have developed an IBS Diagnosis Checklist, providing a tool to diagnose IBS more accurately and enhance a clearer communication with your patient, improving management and care. This tool has received the endorsement of the World Gastroenterology Organisation.

IBS
Actu GP : La dysbiose vaginale à l’origine de certains cas d’infertilité ?

Download your tool here:

Image
IBS Diagnostic Tool Pr. J Tack EN

52% Just 1 in 2 people having suffered from a digestive condition involving the microbiota had made the connection

68% More than 2 in3 people know that IBS could be related to microbiome

What you will find in the IBS diagnosis tool?

Dear healthcare professionnal, for the first time you will find all the information you need in one usefull IBS diagnosis tool:

  • Simple figures to explain the disease, the symptoms and the pathophysiology
  • The diagnosis criteria and the IBS subtypes according to Rome V
  • A checklist of warning signs to be investigated to help you confirm your diagnosis
  • The list of investigations that are needed, the one recommended in specific case and finally those not useful as routine test
  • The four general management concepts
  • A frequency proposal to conduct the follow up care

How to define Irritable Bowel Syndrome (IBS)?

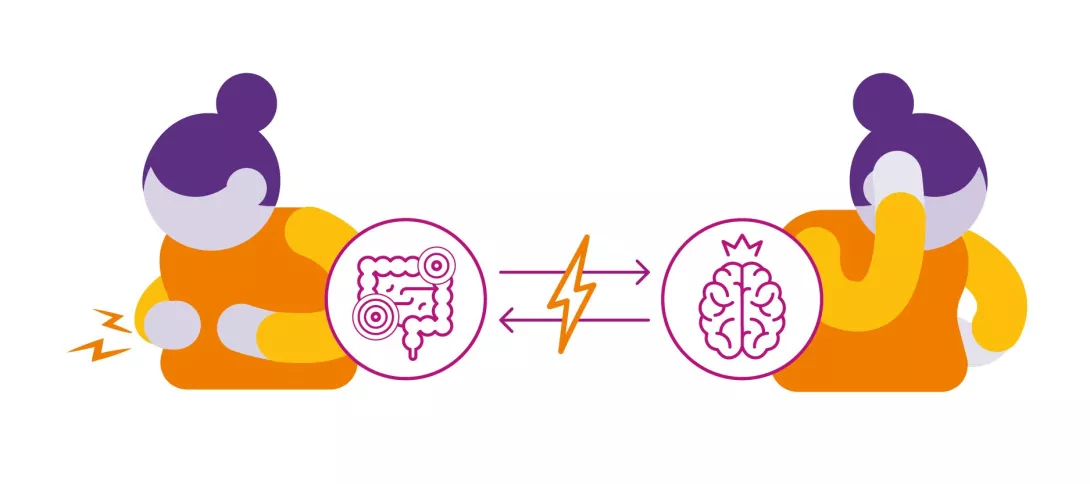
Irritable bowel syndrome is a disorder of the gut-brain axis (DGBI) and is a symptom-based disorder with no tissue damage.

Image
Illustration of bidirectional communication between the gut and the brain in irritable bowel syndrome (IBS).

It is characterized by:


  1. Bloating and/or abdominal distension
  2. Recurrent (but not continuous) abdominal pain or discomfort
  3. Altered bowel habits (in terms of frequency and/or shape of stools).


In addition, patients often experience higher anxiety and/or depression levels, and IBS occurrence could be related to an imbalance of the gut microbiota – or dysbiosis.
4 to 10% of population suffer from IBS, depending on the geographical region and the criteria used for assessment. For example, Western Europe tends to have higher rates than Asia.

List of synonymous disorder names:

  • Irritable bowel syndrome
  • Spastic colon
  • Mucous colitis
  • Functional colopathy
What to say about IBS?
  • Bloating, recurrent abdominal pain/discomfort and altered bowel habit characterize this symptom-base disorder named irritable bowel syndrome (IBS). 
  • IBS is a disorder of gut–brain interaction, the two organs don’t understand and communicate with each other properly.
  • IBS is a symptom-based disorder with no tissue damage>.
  • Gastrointestinal symptoms do not come alone, IBS is often accompanied by higher levels of psychological upset such as anxiety, stress and depression.
  • The brain receives signals from the bowel that are over-interpreted as signals of harm.
     

What do we know about the pathophysiology?

Image
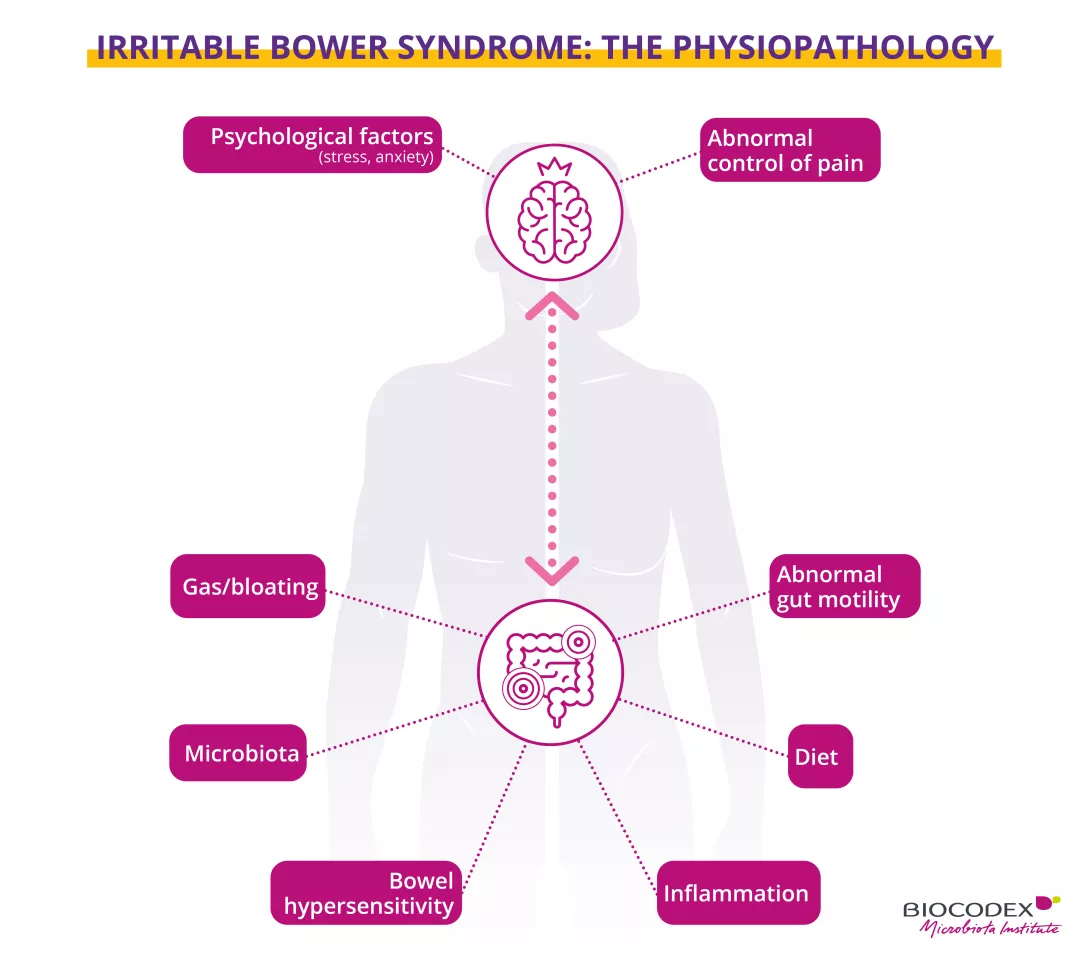
IBS pathophysiology: Diagram of factors involved in IBS: stress, anxiety, pain perception, gut motility, microbiota, diet, visceral hypersensitivity, inflammation and bloating.

Although the precise biological mechanisms underlying IBS are not fully understood yet and the precise etiology of the disorder remains elusive, recent evidence identified the following pathophysiological mechanisms:


  • Psychological factors including stress, anxiety, depression can influence gut function and exacerbate symptoms
  • Gas/bloating
  • Microbiota: changes in the gut microbiota may contribute to immune activation, visceral hypersensitivity, and altered motility
  • Bowel hypersensitivity: increased sensitivity of bowel sensory neurons leads to exaggerated pain and discomfort in response to normal stimuli
  • Inflammation: low-grade inflammation contributes to symptoms
  • Diet
  • Abnormal gut motility
  • Abnormal control of pain in the central nervous system
     

How to make a confident diagnosis?

IBS is diagnosed according to Rome V criteria.


  • Presence of chronic/recurrent and not continuous abdominal pain or discomfort at least 3 days per month in the last three months, with criteria onset at least six months before diagnosis.
  • Associated with two or more of the following criteria: related to defecation, associated with a change in frequency of stool, associated with a change in form (appearance, consistency) of stool.


To be noted: abdominal pain and discomfort should not be only related to menses.
 

IBS is subdivided into different subtypes

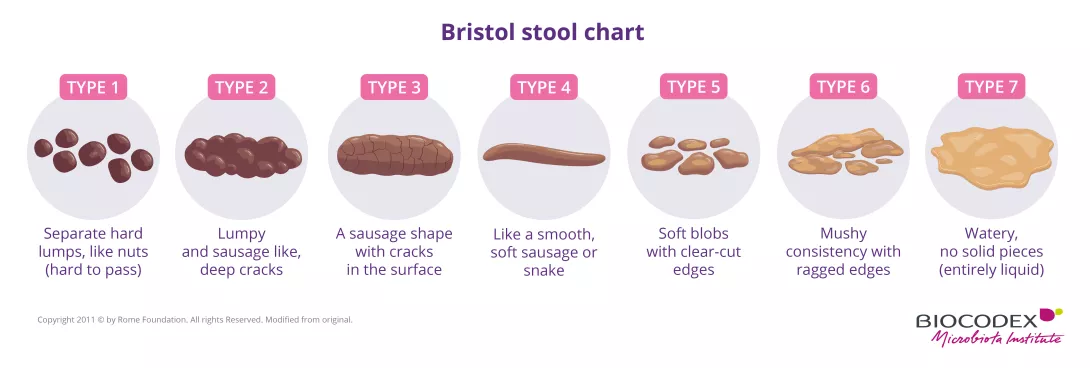
They are characterized by the consistency of stools according to the Bristol stool chart:

  • IBS-C: predominance of constipation, with more stool types 1-2 than stool types 6-7.
  • IBS-D: predominance of diarrhea, with more stool types 6-7 than stool types 1-2.
  • IBS-M: mixed symptoms with alternating constipation (Bristol 1-2) and diarrhea (Bristol 6-7)
  • IBS-U: unspecified bowel habits, stools are rarely abnormal.
Image
Bristol Stool Chart: Bristol Stool Chart illustrating the 7 stool types, from separate hard lumps (type 1) to entirely liquid stools (type 7).
What to say about IBS?
  • The bowel is processing signals over-sensitively and this affects function.
  • The function of the bowel is affected by the nervous system.
  • The bowel sends signals in such a way that they are over-interpreted by the brain.
  • The brain is receiving or processing signals too sensitively.
  • The brain is misinterpreting normal signals from the body as signs of disease.
  • IBS could be related to an unbalanced gut microbiota.

Everything you need to know about the microbiota gut-brain axis

Go deeper

What are the warning signs requiring further evaluation?

Checklist of features requiring additional investigations of referral

If one or more of the following symptoms are present, consider further evaluation and/or referral:
  • Family history (inflammatory bowel disease, celiac disease or colorectal cancer)
  • Weight loss
  • Fever
  • New symptoms (less than 6 months)
  • Nocturnal symptoms
  • Extra-intestinal symptoms (arthritis, rash, eye inflammation)
  • Recent use of antibiotics
  • Abnormalities in physical examination
Refer to a gastroenterologist for review in presence of one or more of the following symptoms:
  • Anemia or blood loss
  • Increase in inflammatory markers
  • Fecal incontinence
  • Abdominal mass

Which investigations are needed?

Don’t over investigate!

Recommended as routine tests:

  • Full blood count
  • C-reactive protein (CRP) (exclusion of IBD or other inflammatory condition)
  • Stool pattern evaluation: frequency and consistency (Bristol)
     

Consider in specific case:

  • Fecal calprotectin in case of diarrhea as a symptom and if reimbursed in your country.
  • Serology for celiac disease if the pathology is prevalent in your country.
  • Thyroid test only in case of majorly altered bowel habit, with other clinical signs, to be reassured.
  • Colonoscopy only in selected cases, based on stool pattern sub-type (diarrhea) and result of calprotectin test, age threshold for colorectal cancer screening (usually >50 years), personal and/or familial history.
  • Rectal Exam recommended in anyone with blood in the stools; Males & Females > 40 years with lower GI symptoms.
     

Not useful as routine tests

  • Iron studies
  • Albumin
  • Parasitology (parasite if overseas travels stool MC&S, C. difficile toxin)
  • Bowel cancer screening outside the recommended national guidelines
  • CT scan / Ultrasound / MRI
  • Gynecological evaluation
     

What are the general management concepts?

IBS symptoms are managed with a multi-faceted approach including:

1.    Diet intervention
  • Healthy diet, limiting the intakes of potential dietary triggers such as FODMAPs, lactose, gluten, etc.
  • Prebiotics, probiotics and/or fibers intake
2.    Lifestyle adjustment
  • Regular physical activity
  • Regular sleep habits
3.    Gut-brain signal management
  • Psychotherapeutic interventions such as Cognitive Behavior Therapy (CBT), hypnosis, psychodynamic, relaxation, etc., for long-term psychological support could help reduce the symptoms by acting on the gut-brain interaction.
4.    Symptomatic medical treatment
  • Specific drug targeting bowel function, pain or bloating could help reduce symptoms: antispasmodics, antidiarrheals, laxatives, etc.
What to say about IBS?
  • The microbial communities that live in a specific environment of the body is called microbiota.
  • An unbalanced gut microbiota, or dysbiosis, is a change in the composition and functions of the microorganisms that live in the gut.
  • Food, bacteria, or substances found in the gut can sometimes cause the gut to malfunction and trigger symptoms.
  • IBS is a chronic disorder where symptoms can be managed through lifestyle changes, dietary therapy and psychological therapies.
  • We will meet every 6 to 8 weeks in order to follow up the effectiveness of the treatment/strategy.
     

When to schedule a follow-up care?

Reevaluate treatment in 6 to 8 weeks.

Endorsed by

The World Gastroenterology Organisation

The World Gastroenterology Organisation (WGO) is a federation of 119 Member Societies and four Regional Associations of gastroenterology representing over 60,000 individual members worldwide. The WGO focuses on the improvement of standards in training, education, and the practice of Gastroenterology, Hepatology and other related disciplines worldwide. https://www.worldgastroenterology.org/

The APSSII

The APSSII is an association of patients suffering from irritable bowel syndrome (IBS, also called functional colopathy). Its purpose is to inform about the disease, to promote research, and to allow patients to come out of isolation.

https://www.apssii.org/accueil/index.php

secretariat@apssii.org 

https://youtu.be/xveUZuPcjak

Get the official printed tool! 

Ask your local representative to get your fan deck brochure of the IBS diagnosis tool. 

To know more

Everything you need to know about Irritable Bowel Syndrome (IBS)

Exclusive materials dedicated to Irritable Bowel Syndrome (IBS)

Recommended by our community

"As a gastroenterologist I’ve never found difficult to diagnose IBS, which is by far the most common intestinal disorder at any age.
But any tool which can help physicians( especially GPs) to reach a correct diagnosis is obviously very welcome."
 -  Mario Guslandi (From Biocodex Microbiota Institute on LinkedIn)

"Excellent, thanks!" - Carlos Mora (From Biocodex Microbiota Institute on LinkedIn)

Sources

Barbara G, Grover M, Bercik P, et al. Rome Foundation Working Team Report on Post-Infection Irritable Bowel Syndrome. Gastroenterology. 2019;156(1):46-58.e7.

Black CJ, Ford AC. Global burden of irritable bowel syndrome: trends, predictions and risk factors. Nat Rev Gastroenterol Hepatol 2020; 17: 473-86.

Blake MR, Raker JM, Whelan K. Validity and reliability of the Bristol Stool Form Scale in healthy adults and patients with diarrhoea-predominant irritable bowel syndrome. Aliment Pharmacol Ther. 2016;44(7):693-703.

Carbone F, Van den Houte K, Besard L, et al. Diet or medication in primary care patients with IBS: the DOMINO study - a randomised trial supported by the Belgian Health Care Knowledge Centre (KCE Trials Programme) and the Rome Foundation Research Institute [published online ahead of print, 2022 Apr 28]. Gut. 2022;gutjnl-2021-325821.

Collins, S. A role for the gut microbiota in IBS. Nat Rev Gastroenterol Hepatol 11, 497–505 (2014).

Corsetti M, Shin A, Lacy BE, et al. Bowel Disorders. Gastroenterology. 2026;170(6):1261-1282

Drossman DA, Tack J. Rome Foundation Clinical Diagnostic Criteria for Disorders of Gut-Brain Interaction. Gastroenterology. 2022 Mar;162(3):675-679

Ford AC, Sperber AD, Corsetti M, et al. Irritable bowel syndrome. Lancet. 2020 Nov 21;396(10263):1675-1688.

Fukudo S, Okumura T, Inamori M, et al. Evidence-based clinical practice guidelines for irritable bowel syndrome 2020. J Gastroenterol. 2021;56(3):193-217.

Hillestad EMR, van der Meeren A, Nagaraja BH, et al. Gut bless you: The microbiota-gut-brain axis in irritable bowel syndrome. World J Gastroenterol. 2022 Jan 28;28(4):412-431.

https://www.snfge.org/content/constipation-chronique

Kindt S, Louis H, De Schepper H, et al. Belgian consensus on irritable bowel syndrome. Acta Gastroenterol Belg. 2022;85(2):360-382.

Lacy BE, Pimentel M, Brenner DM, et al. ACG Clinical Guideline: Management of Irritable Bowel Syndrome. Am J Gastroenterol. 2021;116(1):17-44.

Longstreth GF, Thompson WG, Chey WD, et al. Functional bowel disorders [published correction appears in Gastroenterology. 2006 Aug;131(2):688]. Gastroenterology. 2006;130(5):1480-1491.

Moayyedi P, Mearin F, Azpiroz F, et al. Irritable bowel syndrome diagnosis and management: A simplified algorithm for clinical practice. United European Gastroenterol J. 2017;5(6):773-788.

Savarino E, Zingone F, Barberio B, et al. Functional bowel disorders with diarrhoea: Clinical guidelines of the United European Gastroenterology and European Society for Neurogastroenterology and Motility. United European Gastroenterol J. 2022;10(6):556-584.

Simrén, M., Tack, J. New treatments and therapeutic targets for IBS and other functional bowel disorders. Nat Rev Gastroenterol Hepatol 15, 589–605 (2018).

Sperber AD, Bangdiwala SI, Drossman DA, et al. Worldwide Prevalence and Burden of Functional Gastrointestinal Disorders, Results of Rome Foundation Global Study. Gastroenterology. 2021;160(1):99-114.e3.

Sperber AD. Epidemiology and Burden of Irritable Bowel Syndrome: An International Perspective. Gastroenterol Clin North Am. 2021 Sep;50(3):489-503.

Vasant DH, Paine PA, Black CJ, et al. British Society of Gastroenterology guidelines on the management of irritable bowel syndrome. Gut. 2021;70(7):1214-1240.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Gastroenterology Off

Everything you need to know about Irritable Bowel Syndrome (IBS)

Accrediting training, infographics, expert’s video, thematic folder, news… Biocodex Microbiota Institute provides you exclusive materials dedicated to Irritable Bowel Syndrome (IBS). Tailor-made tools and contents to improve your daily practice and be(come) easily an IBS expert!

Follow the guide.

IBS

Get your IBS Diagnosis Check List

Your IBS Diagnosis Check List

Properly diagnosing IBS can be challenging and uncertain, it is a complex disea…

Infographic to share with your patients

What is the Irritable Bowel Syndrome (IBS)?

Useful documents

Irritable bowel syndrome in children & adolescents

Useful documents

An exhaustive thematic folder about Irritable Bowel Syndrome (IBS)

Functional gastrointestinal disorders from childhood to adulthood

Functional gastrointestinal disorders (FGIDs) have long remained underacknowled…

An accrediting training on IBS

Xpeer course: Gut microbiota in the management of gastrointestinal symptoms

A great opportunity for HCPs to be certified on IBS!

Exclusive Microbiota Magazine content

Plausibility of a pathophysiological role for altered gut microbiota in the irritable bowel syndrome

The most common functional bowel disorder, the irritable bowel syndrome (IBS), …

Microbiota gut-brain axis in Irritable Bowel Syndrome

Irritable bowel syndrome (IBS) is a functional gastrointestinal disorder charac…


Latest news about IBS

Patients stories

Living with irritable bowel syndrome (IBS)

Go on the lay public section to discover them
Summary
On
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Gastroenterology Off

Are gut imbalances a risk factor for HIV infection?

Numerous studies have shown that HIV infection is associated with an imbalance of the gut microbiota (dysbiosis). Now US researchers1 have made the surprising discovery that this dysbiosis precedes HIV infection and may even be a risk factor for the disease.

The gut microbiota
HIV

For scientists, an “association” is where two phenomena occur at the same time, without necessarily having a cause-and-effect relationship. Is the gut dysbiosis (i.e. imbalance of the gut flora’s composition) observed in those infected with human immunodeficiency virus (HIV) a cause or a consequence of the disease? Or is it both? With only a few days to go before World AIDS Day on December 1st, the jury is still out, since the state of the gut microbiota prior to infection is not well known, and many other factors influence the appearance of dysbiosis, including age, diet, antibiotic use, and even sexual behavior, according to some recent data2,3.  

To get a clearer picture, US researchers brought together gut microbiota samples from about 50 men who have sex with men, collected during different studies. They selected individuals with similar profiles (age, ethnicity, sexual behavior, etc.), half of whom were infected with HIV during the course of the studies, with the other half remaining HIV free. They were thus able to compare the gut microbiota of the infected men before and immediately after infection, and to compare the infected men’s gut microbiota with that of the healthy uninfected pairs.

38 million At the end of 2021, approximately 38 million people were living with HIV worldwide, more than two-thirds of them in Africa.

Minimal changes in microbiota before/after HIV infection... 

The authors first found that the composition of the infected men’s gut microbiota changed very little during the acute phase of HIV. Only increased Fusobacterium mortiferum was observed. Not normally resident in the gut flora, this bacterial species had already been associated with HIV in other studies.

... but significant pre-infection differences vs. controls

In contrast, the gut microbiota of the men who would go on to be infected with HIV (i.e., their “pre-infection” gut microbiota) differed from that of the controls (who remained HIV free). In particular, they had fewer bacteria from the Bacteroides group, and increased levels of Megasphaera elsdenii, Acidaminococcus fermentans, and Helicobacter cinaedi. This type of dysbiosis has frequently been observed in HIV-infected individuals. However, in this new study, the gut imbalance appears to have been present before infection, potentially influencing susceptibility to HIV, according to the authors.

Transmission of HIV

HIV is a virus transmitted through sexual contact, through the blood, and from mother to child (during pregnancy, childbirth, or breastfeeding). It attacks cells that carry a CD4 receptor, particularly T cells, a type of white blood cell that performs a major immune function in the body’s defense against attack by external microbial agents (bacteria, viruses, or fungi) or other foreign invaders.

HIV infection occurs in three successive phases over 10 years on average (with significant differences between individuals): 

  • The acute or primary infection phase begins 10 to 15 days after infection and lasts about two weeks. The virus invades the body, penetrates the CD4 cells, and is fought by the immune system. This stage may be asymptomatic or appear as a flu-like illness.

  • The chronic phase results in the exhaustion of the immune system, mainly through the progressive loss of CD4 T cells. It can last several years and may be accompanied by minor skin and gastrointestinal disorders, mild fever, night sweats, etc.

  • The AIDS (acquired immunodeficiency syndrome) phase corresponds to a very low level of CD4 T cells and the onset of opportunistic diseases (which “take advantage” of the weakness of the immune system to develop) such as serious infections or certain types of cancer.4

Gut microbiota, a new tool for preventing HIV?

So, does gut microbiota composition play a role in susceptibility to HIV infection? Encouraged by similar conclusions from another US team5, the researchers propose that this avenue be followed up by studies on larger samples. They hope that this will identify a “gut microbiota signature” associated with greater susceptibility to HIV infection, thus allowing more targeted prevention via treatment of the gut microbiota of people at risk.6  

The researchers make it clear that this finding does not contradict the idea that HIV can itself cause dysbiosis. The short duration of the study meant it was not possible to observe the changes in gut microbiota composition that occur during chronic HIV. In addition, these results were obtained in a small group with a specific profile and thus generalizability beyond this population is limited.

The gut microbiota

Find out more
Sources
  1. Fulcher JA, Li F, Tobin NH, et al. Gut dysbiosis and inflammatory blood markers precede HIV with limited changes after early seroconversion. EBioMedicine. 2022;84:104286
  2. Noguera-Julian M, Rocafort M, Guillen Y, et al. Gut microbiota linked to sexual preference and HIV infection. EBioMedicine. 2016;5:135–146.
  3. Armstrong AJS, Shaffer M, Nusbacher NM, et al. An exploration of Prevotella-rich microbiomes in HIV and men who have sex with men. Microbiome. 2018;6(1):198.
  4. Collège des Universitaires de Maladies Infectieuses et Tropicales. Infection à VIH, UE6 n° 165. ECN Pilly 6ème édition 2020. Alinéa Plus, Paris ; p 195-210
  5. Chen Y, Lin H, Cole M, et al. Signature changes in gut microbiome are associated with increased susceptibility to HIV-1 infection in MSM. Microbiome. 2021;9(1):237
  6. UCLA Health Newsroom : Gut bacteria may contribute to susceptibility to HIV infection, UCLA-led research suggests (29/09/22) https://www.uclahealth.org/news/gut-bacteria-may-contribute-susceptibility-hiv-infection
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News

Is gut dysbiosis a risk factor for HIV infection?

A recent US study has revealed that the gut dysbiosis and systemic inflammation observed in HIV patients appear to be present prior to seroconversion, increasing vulnerability to infection.1 This unexpected insight into the links between HIV and the gut microbiota may help guide targeted prevention efforts.

HIV

With only a few days to go before World AIDS Day on December 1st, let’s take a look at the links between HIV and the microbiota. Numerous studies have associated changes in the gut microbiome with HIV infection. However, many of these studies have been cross-sectional and methodologically heterogeneous, and therefore subject to various confounding factors. HIV infection is known to be accompanied by gut dysbiosis and bacterial translocation linked to systemic inflammation, but the time course involved is not fully understood. Furthermore, recent studies have shown that, in addition to age, diet, and antibiotic use, sexual behavior also influences the gut microbiota, regardless of HIV status2,3, further confounding the evidence.

Longitudinal study with bias controlled

 To measure changes in the gut microbiota and markers of inflammation during HIV infection, the researchers selected fecal and blood samples from four different longitudinal studies (USA, Peru) conducted over periods of 4 months to 2 years among men who have sex with men. Of these men, 27 were infected with HIV. The samples from the infected men were paired with those of 28 controls with similar demographic and behavioral characteristics.

Changes in the gut microbiota and inflammatory markers precede seroconversion 

The researchers noted few changes in the gut microbiota of subjects during the acute phase of HIV. In a subgroup from a US study, only an increase in Fusobacterium mortiferum was observed shortly after seroconversion, together with a decrease in Prevotella intermedia. The most significant differences were between pre-HIV infection subjects and controls. The gut microbiota of pre-HIV infection subjects showed reduced levels of several Bacteroides species and a higher level of Megasphaera elsdenii. They also had higher plasma levels of inflammatory cytokines (B cell activating factor, IL-8, TNF-α).

Gut microbiota, a targeted prevention option?

According to the authors, the study suggests that the changes to the gut microbiota existed before HIV infection. Together with similar results from another US team4, this shows that gut dysbiosis is a contributing factor to HIV rather than a consequence of it, even if dysbiosis is subsequently observed in chronic HIV. The observation period of the study was too short for the researchers to identify subsequent changes. In addition, the small sample size and the specific characteristics of the participants (sex, age, drug use, sexual behavior, etc.) may also limit generalizability. However, the researchers believe that the discovery of a gut signature for HIV susceptibility and/or inflammatory markers may provide a new tool for targeted prevention.

Recommended by our community

"Good" -@khubaibchandia (From Biocodex Microbiota Institute on X)

Sources
  1. Fulcher JA, Li F, Tobin NH, et al. Gut dysbiosis and inflammatory blood markers precede HIV with limited changes after early seroconversion. EBioMedicine. 2022;84:104286
  2. Noguera-Julian M, Rocafort M, Guillen Y, et al. Gut microbiota linked to sexual preference and HIV infection. EBioMedicine. 2016;5:135–146.
  3. Armstrong AJS, Shaffer M, Nusbacher NM, et al. An exploration of Prevotella-rich microbiomes in HIV and men who have sex with men. Microbiome. 2018;6(1):198
  4. Chen Y, Lin H, Cole M, et al. Signature changes in gut microbiome are associated with increased susceptibility to HIV-1 infection in MSM. Microbiome. 2021;9(1):237
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Gastroenterology