Targeting the gut microbiota to combat allergies

Overview

By Pr. Roberto Berni Canani, MD, PhD
Department of Translational Medical Science; European Laboratory for the Investigation of Food Induced Diseases, and CEINGE Advanced Biotechnologies; Task Force on Investigation on Microbiome, University of Naples “Federico II”, Naples, Italy
Photo : Targeting the gut microbiota to combat allergies

Dysbiotic gut microbiota plays an important role in the development of allergic diseases, in particular food allergies. The gut microbiota drives the maturation and function of the immune system, and genetic, environmental, and dietary factors may alter the commensal microbiota, leading to a dysregulation of immune function. Several factors responsible for dysbiosis have been associated with the occurrence of allergies, such as Caesarean delivery, the lack of breast milk, the use of drugs (mainly antibiotics and gastric acidity inhibitors), the use of antiseptic agents, and low-fibre/high-fat diets. No specific bacterial taxa have been consistently associated with allergies, but evidence suggests that gut dysbiosis occurs even before allergies present. Shortchain fatty acids (SCFAs) are crucial gut microbiota-derived metabolites involved in cross-talk with the immune system. Targeting the composition and function of the gut microbiota represents a promising strategy against allergic diseases, in particular, against childhood food allergies.

The prevalence, persistence, and severity of allergic diseases and, in particular, food allergies (FA), has increased substantially in recent decades in the industrialised world under the pressure of gene-environment interactions leading to immune system dysfunction, mediated, at least in part, by epigenetic mechanisms [1, 2]. This changing scenario has led to an increase in hospital admissions, medical visits, treatments, and a greater burden of care on families. All these factors have a significant impact on social costs and quality of life, and place a great psychological burden on patients and families.

Food allergies are characterised by an abnormal immune response towards dietary antigenic peptides that are normally tolerated. The cause of FAs is still largely undefined. Based on current knowledge, genetic susceptibility alone cannot account for the changing pattern of FAs and there has been a renewed interest in the role of the environment in the sensitisation to food. Evidence suggests a key pathogenetic role of gut microbiota (GM) alterations (dysbiosis) in allergy development. A healthy GM has a crucial impact on the development of the gastro-intestinal tract and immune system. A dysbiotic GM is associated with various diseases, including allergies [3].

The importance of microbial exposure for immune tolerance

The way in which dietary antigens are normally rendered non-immunogenic through immune tolerance has not yet been fully defined. Evidence suggests a pivotal role for regulatory T cells (Tregs) expressing the transcription factor Foxp3 (Foxp3+Tregs) and the complex interaction between the GM and immune and non-immune cells. The presence of both diet-and microbe-induced populations of Treg cells is required for full tolerance to food antigens [4].

During vaginal delivery, infants receive their first bacterial inoculum from the maternal vaginal tract, skin tissue, and often from faecal matter, exposing the immature immune system to a significant bacterial load [3]. The maturation of a healthy GM in early life allows for a change in the Th1/Th2 balance, favouring a Th1 cell response, while dysbiosis alters host-microbiota homeostasis, producing a shift in the Th1/Th2 cytokine balance towards a Th2 response [5].

Tregs are depleted in germ-free mice and in mice receiving an amino acid-based diet [4, 6]. Secretory IgA (sIgA) and innate immunity peptides exert a pivotal role in regulating GM composition. Deficiency in both innate and adaptive immunity (especially low levels of IgA) has been observed in children with multiple FAs [7]. A healthy GM promoting sIgA production facilitates the survival of protective bacterial strains within the gut lumen [8].

The gut microbiota and allergies

The expression of an allergic phenotype is dependent on the interaction between two major factors: genetic predisposition and gene-environment interactions. An increasing number of studies suggests a correlation between factors that alter the GM in the first years of life and the development of allergies later in life. There is increasing evidence that early-life GM dysbiosis represents a critical factor underlying the development of allergies.

The main factors responsible for dysbiosis are: birth by Caesarean section, lack of breast milk, drug use (mainly antibiotics and gastric acidity inhibitors), antiseptic agent use, timing of the introduction of solid foods, and junk food-based and/or low-fibre/high-fat diets [3, 9]. The maternal use of antibiotics before and during pregnancy, as well as antibiotic treatments during the first months of life, are also reported to be associated with an increased risk of cow’s milk allergies (CMA) in children [10]. Data that may be used to characterise the microbiota of patients with FAs are still preliminary. We recently described GM dysbiosis in children affected by IgE-mediated CMA; CMA infants had significantly reduced levels of Bifidobacteriaceae, Streptococcaceae, Enterobacteriaceae, and Enterococcaceae, and presented significantly higher levels of selected strains from Ruminococcaceae and Lachnospiraceae families. The GM of subjects with CMA comprised 73% Bacteroidetes and Firmicutes taxa, which are also known to dominate the adult gut [11].

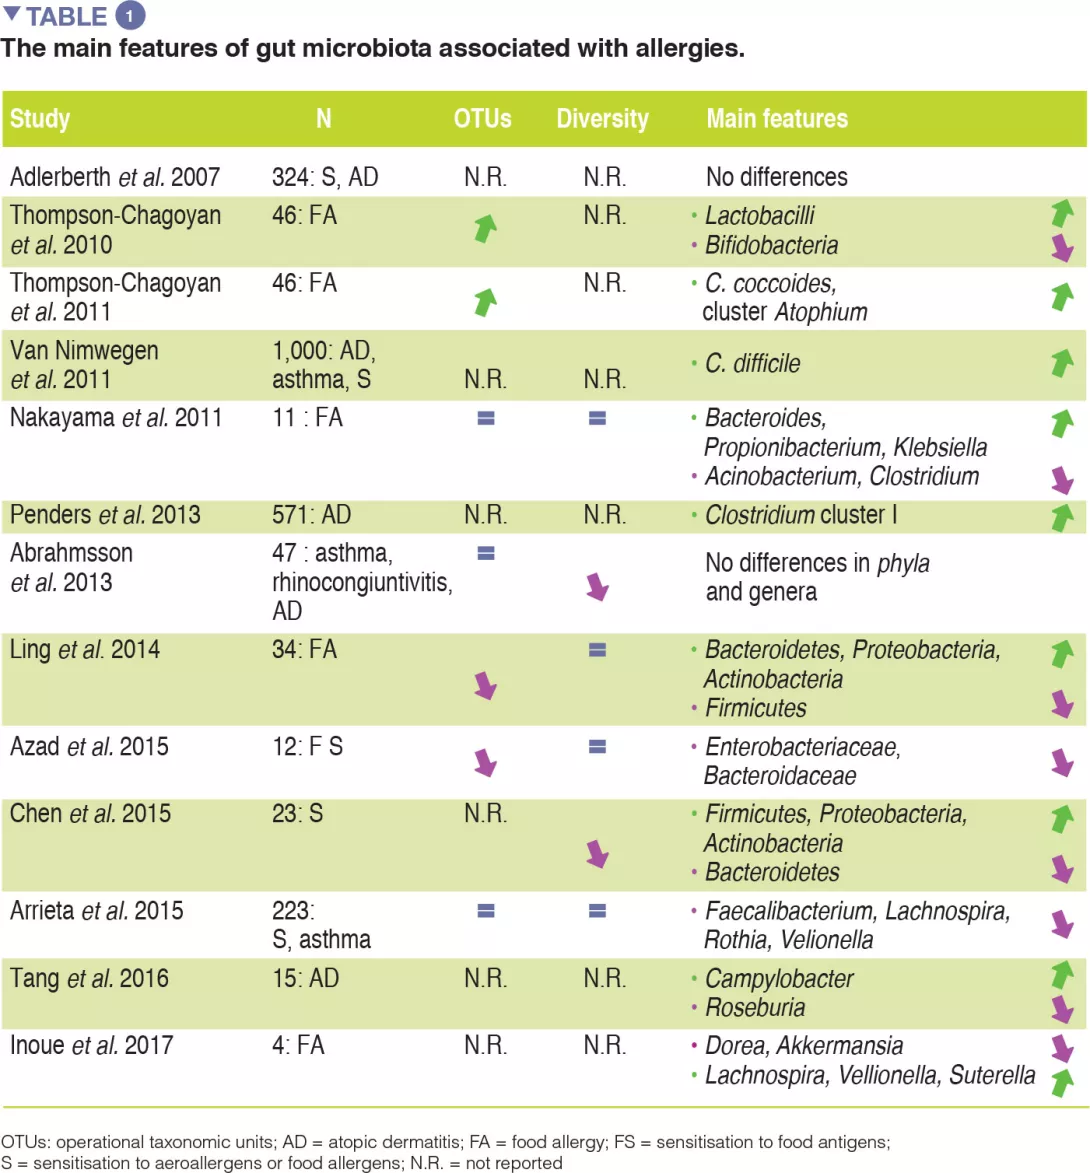
Although compelling evidence for an association between GM dysbiosis and FAs is emerging, heterogeneity in study design (involving sampling time points, the methods used to characterise microbiota, and allergic phenotypes studied) has made it difficult to establish a causal relationship between specific bacterial taxa and the development of allergies. No specific bacterial taxa have been consistently associated with FA and a broad range of microbes isolated from the human gut may be involved in tolerogenic mechanisms. The main evidence for allergy-associated GM is summarised in Table 1.
Image

The gut microbiota plays a central role in the pathogenesis of allergies

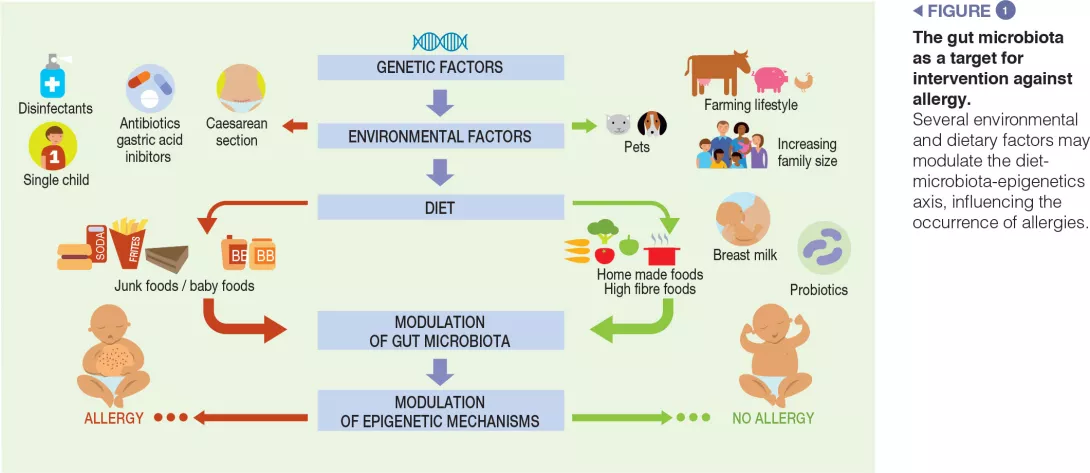
Evidence suggests that the gut microbiota-epigenetics axis, modulated by a number of environmental and dietary factors, plays an important role in the occurrence of allergies. This axis regulates a number of non-immune and immune tolerogenic mechanisms, and could be the ideal target for innovative, preventive, and therapeutic strategies against allergies.

SCFAs are major GM metabolites involved in cross-talk with human cells. Among the SCFAs, butyrate exerts a pivotal role in the induction of immune tolerance, and butyrate deficiency has been observed in allergic patients [4]. The different types of dysbiosis may be hypothesised to lead to similar effects in terms of SCFAs, and/ or the production of other microbiota-derived metabolites may facilitate the occurrence of allergies. Clostridia species, belonging to Cluster IV and XIVa, are the prominent source of SCFAs in the colon. Bacteria-produced SCFAs have been implicated in the regulation of both the proportion and functional capability of Tregs, which, in some studies, have been specifically attributed to butyrate production by spore-forming Clostridiales. An enrichment of taxa from the Clostridia class and Firmicutes phylum has been observed in human subjects with resolution of CMA [9]. Data from our laboratory showed that oral butyrate treatment leads to a dramatic inhibition of acute allergic skin response, anaphylactic symptom scores, reduced body temperature, increased intestinal permeability, and anti-βLG lactoglobulin (BLG) IgE, IL-4, and IL-10 production in a murine model of CMA, suggesting a protective role of butyrate against FAs [9]. Butyrate exhibits multiple mechanisms of action, however, many of these involve epigenetic regulation of gene expression through the inhibition of histone deacetylase (HDAC). The inhibition of HDAC9 and 6 increases FoxP3 gene expression, as well as the production and suppressive function of Tregs [12]. We evaluated the direct effects of butyrate on peripheral blood mononuclear cells (PBMCs) from children affected by challenge-proven IgE-mediated CMA. PBMCs were stimulated with BLG in the presence or absence of butyrate. Preliminary results show that butyrate stimulates IL-10 and IFN-γ production and decreases the rate of DNA methylation of these two cytokines. The same effective butyrate dose induces demethylation of the FoxP3 promoter region and down-regulation of HDAC6/HDAC9 expression [2].

Modulation of the gut microbiota associated with allergies

Children exposed to farm environments have a lower risk of allergy development. Although it has not been conclusively proven, one of the plausible explanations for the protective effect associated with early- life farm exposure is the role of the GM, because individuals exposed to a farm environment possess a different microbial composition relative to those with other lifestyles [3]. Other epidemiological factors which protect against FAs include older siblings and exposure to pets in early life. Pet ownership is associated with high microbial diversity in the home environment. A recent study examining the influence of dietary patterns on the development of FAs at the age of two suggests that dietary habits may influence the development of FAs by changing the composition of the gut microbiota. In particular, an infant diet consisting of high levels of fruits, vegetables, and home-prepared foods was associated with less FAs [9] (Figure 1).

Probiotics, defined as ingested microbes that provide health benefits to the host, may be beneficial by modulating the GM [13]. Evidence of probiotic use against respiratory allergies remains preliminary (Table 2). However, meta-analyses have revealed that the use of selected probiotics, from gestation through to the first six months of life, could reduce the incidence of atopic eczema in children with a family history of allergic disease [14].
How to modulate the gut microbiota?

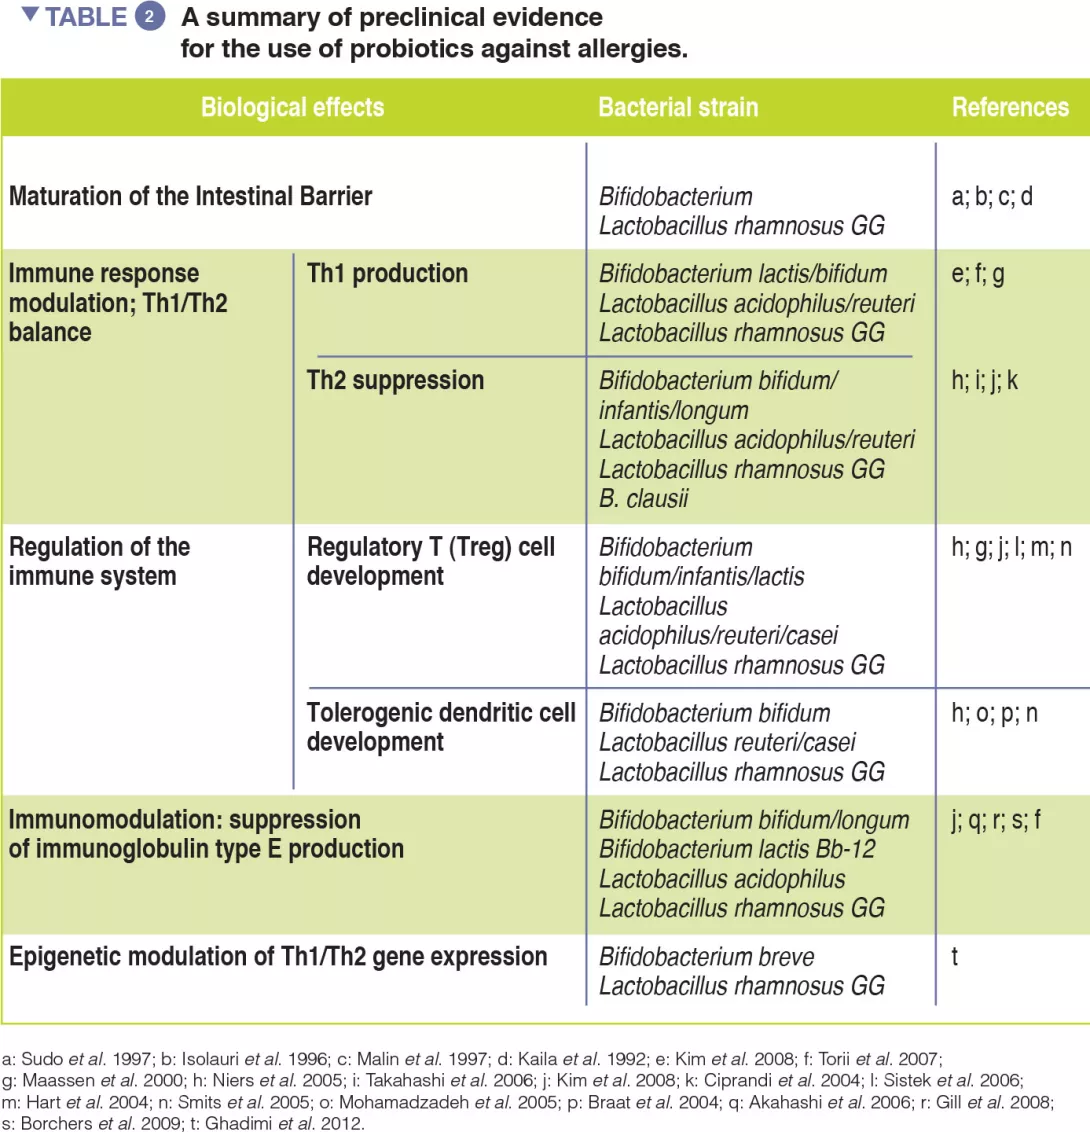
Emerging evidence supports the use of selected dietary strategies and probiotic strains for the prevention and treatment of allergies (Table 2).

Image

We have previously demonstrated that addition of the probiotic, L. rhamnosus, to a hypoallergenic formula accelerates the acquisition of immune tolerance and protects against the occurrence of other atopic manifestations in children with CMA [15-17]. When we compared the faecal microbiota among infants receiving this tolerance-inducing probiotic therapy, we found significant positive correlations between the abundance of genera with a potential to produce butyrate and the concentration of faecal butyrate [11]. Strain-level demarcations for butyrate-producing genera (including Roseburia, Coprococcus, and Blautia), identified in infants who acquired tolerance to cows’ milk, suggest that L. rhamnosus treatment contributes to the acquisition of tolerance by altering the strain-level community structure of taxa with a potential to produce butyrate [11]. Accordingly, oral immunotherapy supplemented with another L. rhamnosus strain has been shown to be effective in inducing peanut non-responsiveness in 82% of allergic children [18].
Image

Conclusion

The trillions of bacteria that populate our gut critically regulate key physiological functions against allergies. Environmentally induced changes in GM composition and function (decreased butyrate production, for example) create dysbiosis that is linked to an increased risk of allergy. Understanding how gut bacterial communities interact with the immune system is opening the way to novel preventive treatment strategies for allergies.

Sources

1 Tanaka M, Nakayama J. Development of the gut microbiota in infancy and its impact on health in later life. Aller Internat 2017; 66: 515e522.

2 Paparo L, Di Costanzo M, Di Scala C, et al. The influence of early life nutrition on epigenetic regulatory mechanism of the immune system. Nutrients 2014; 6: 4706-19.

3 Berni Canani R, Gilbert JA, Nagler CR. The role of the commensal microbiota in the regulation of tolerance to dietary antigens. Curr Opin Allergy Clin Immunol 2015; 15: 243-9.

4 Smith PM, Howitt MR, Panikov N, et al. The microbial metabolites, short-chain fatty acids, regulate colonic Treg cell homeostasis. Science 2013; 341: 569-73.

5 Inoue Y, Shimojo N. Microbiome/microbiota and allergies. Semin Immunopathol 2015; 37: 57e64.

6 Kim KS, Hong SW, Han D, et al. Dietary antigens limit mucosal immunity by inducing regulatory T cells in the small intestine. Science 2016; 351: 858-63.

7 Sampath V, Sindher SB, Zhang W, et al. New treatment directions in food allergy. Ann Allergy Asthma Immunol 2018; 120: 254-62.

8 Bieber T, Cork M, Reitamo S. Atopic dermatitis: a candidate for disease-modifying strategy. Allergy 2012; 67: 969-75.

9 Aitoro R, Paparo L, Amoroso A, et al. Gut microbiota as a target for preventive and therapeutic intervention against food allergy. Nutrients 2017; 9: E672.

10 Metsälä J, Lundqvist A, Virta LJ, et al. Mother’s and offspring’s use of antibiotics and infant allergy to cow’s milk. Epidemiology 2013; 24: 303-9.

11 Berni Canani R, Sangwan N, Stefka AT, et al. Lactobacillus rhamnosus GG supplemented formula expands butyrate producing bacterial strains in food allergic infants. ISME J 2016; 10: 742-50.

12  Berni Canani R, Paparo L, et al. Differences in DNA methylation profile of Th1 and Th2 cytokine genes are associated with tolerance acquisition in children with IgE-mediated cow’s milk allergy. Clin Epigenetics 2015; 31: 7-38.

13 Hill C, Guarner F, Reid G, et al. The International Scientific Association for Probiotics and Prebiotics consensus statement on the scope and appropriate use of the term probiotics. Nat Rev Gastro Hepat 2014; 11: 506-14.

14 Cuello-Garcia CA, Brożek JL, Fiocchi A, et al. Probiotics for the prevention of allergy: A systematic review and meta-analysis of randomized controlled trials. J Allergy Clin Immunol 2015; 136: 952-61.

15 Berni Canani R, Nocerino R, Terrin G, et al. Effect of Lactobacillus GG on tolerance acquisition in infants with cow’s milk allergy a randomized trial. J Allergy Clin Immunol 2012; 129: 580-2; 582.e 1-5.

16 Berni Canani R, Nocerino R, Terrin G, et al. Formula selection for management of children with cow’s milk allergy influences the rate of acquisition of tolerance: a prospective multicenter study. J Pediatr 2013; 163:771-7.e1.

17 Berni Canani R, Di Costanzo M, Bedogni G, et al. Extensively hydrolyzed casein formula containing Lactobacillus rhamnosus GG reduces the occurrence of other allergic manifestations in children with cow’s milk allergy: 3-year randomized controlled trial. J Allergy Clin Immunol 2017; 139: 1906-1913.e4.

18 Tang ML, Ponsonby AL, Orsini F, et al. Administration of a probiotic with peanut oral immunotherapy: A randomized trial. J Allergy Clin Immunol 2015; 135: 737-44.e8.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article

Microbiota and cystic fibrosis

Press review

By Pr. Ener Cagri Dinleyici
Professor in Pediatrics, Eskisehir Osmangazi University Faculty of Medicine; Department of Pediatrics, Eskisehir, Turkey

Cystic fibrosis (CF) is a progressive, genetic disease that causes persistent lower respiratory infections and is related to different systemic symptoms and signs. More than 70,000 people live with CF worldwide [1].

The types and severity of symptoms can differ widely from person to person and are mainly related to the age of the patient as well as age at diagnosis. Children and adolescents with CF have a wide range of symptoms and signs including gastrointestinal manifestations. Recent studies have shown that dysbiosis is a feature of CF, leading to reports focusing on the relationship between the composition of the airway microbiota and clinical features and pulmonary function in patients with CF [2].

Dysbiosis-associated CF may be related to the natural course of the disease (including gastrointestinal involvement or respiratory microbiota alterations). However, patients require multiple courses of antibiotic treatment and these antibiotics may change the composition of the microbiota.

Studies have shown that patients with CF typically have decreased amounts of Bifidobacterium spp., Bacteroides-Prevotella group, Clostridium cluster XIVa, Faecalibacterium prausnitzii and Eubacterium rectale, whereas Enterobacteriaceae and Clostridia are increased. De Freitas and colleagues published a recent study in PLOS One, aimed at evaluating the effect of CF and antibiotic therapy on the intestinal microbiota composition in 19 children and adolescents with CF relative to 17 age and sex-matched controls [3]. The level of fecal calprotectin (an intestinal inflammation marker) was higher in the CF group (irrespective of antibiotic treatment) compared to the healthy controls. The authors showed that Bacteroides, Firmicutes, Eubacterium rectale and Faecalibacterium prausnitzii were significantly decreased, whereas Clostridium difficile, Escherichia coli and Pseudomonas aeruginosa were significantly increased in the CF group, relative to the healthy controls. The main differences in microbiota composition between patients with CF and controls, irrespective of antibiotic treatment, were noted for Eubacterium rectale, Bifidobacterium, Escherichia coli, Firmicutes, Pseudomonas aeruginosa and Clostridium difficile. The results of this study therefore demonstrate that the intestinal microbiota composition in CF patients is different from that of healthy controls and that the frequent use of antibiotics has no additional effects on these alterations.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Press review

Microbiota and non-antibiotic drugs interactions: friends or foes?

Press review

By Pr. Ener Cagri Dinleyici
Professor in Pediatrics, Eskisehir Osmangazi University Faculty of Medicine; Department of Pediatrics, Eskisehir, Turkey

Photo : Microbiota and non-antibiotic drugs interactions: friends or foes?

Most of the recent studies about the effects of drugs on the intestinal microbiota composition have focused on antibiotic use in different age groups.

Previous studies showed that metformin, proton pump inhibitors, NSAIDs, and atypical antipsychotics have an effect on the intestinal microbiota composition. However, these studies presented general results for drug classes instead of specific drugs. Lisa Maier and colleagues published their new study results in Nature in 2018, and they aimed to generate a comprehensive resource of more than 1,000 drugs actions on the microbiome (against 40 representative gut bacterial strains), which could facilitate more in-depth clinical and mechanistic studies, ultimately improving therapy and drug design. Maier et al. [1] showed that 24% out of these 1,000 drugs inhibited the growth of at least one strain in vitro. The effects of human-targeted drugs on gut bacteria are reflected on their antibiotic-like side effects in humans, like previously published human studies. This study showed that susceptibility to antibiotics and human- targeted drugs correlates across bacterial species, suggesting common resistance mechanisms, and highlighted the potential risk of non-antibiotics promoting antibiotic resistance. Widespread worldwide use of pharmaceutical drugs might be related with the dysbiosis, especially in modern Western societies.

This recent trial also showed that the intestinal microbiota composition can also modulate drug efficacy and toxicity and might be a new platform for further drug development; however, further in vivo clinical trials are necessary to better understand the mechanism of action. A comprehensive understanding of how therapeutics interact with gut microbes will open up the path for further mechanistic dissection of such interactions, and ultimately improve not only our understanding of the gut microbiome, but also drug safety and efficacy [2].

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Press review

3rd meeting of the federation of neurogastroenterology

Congress review

By Dr. Jari Punkkinen
Head of Endoscopy Unit, Porvoo Hospital, Department of Medicine, Finland

IBD
Image1_Article5_Microbiota_NL-5_FR

Selected experts about Irritable Bowel Syndrome and Gut Microbiota.

Gut microbiota dysbiosis in IBS

Microbiota dysbiosis and its relation to irritable bowel syndrome (IBS) was discussed during various sessions of the conference. In particular, Pr. Magnus Simrén and Pr. Uday Ghoshal highlighted some features related to microbiota composition of IBS patients. Based on several studies, IBS patients have been shown to have a low microbial richness compared to healthy individuals, and Methanobacteriales may be undetected and methane production low in such patients [1].

Furthermore, a subset of IBS patients present dysbiosis with increased Firmicutes and Bacteroides enterotypes compared to healthy individuals with enriched Clostridiales and Prevotella enterotypes. However, an important question is not only which bacteria are associated with IBS but what they do in the gut and how they are involved in mechanisms of visceral hypersensitivity, neuro-motor dysfunction, increased permeability, and low-grade inflammation. Small intestine bacterial overgrowth (SIBO) may be the cause of IBS in some patients and a current challenge is to improve screening for these patients as upper gut aspirate culture is difficult to perform and not always available. The glucose hydrogen breath test may be used to identify such patients, and this would appear to be more accurate than the lactulose hydrogen breath test [2].

Gut microbiota modulation in IBS

Can the gut microbiome be changed for therapeutic purposes and could it relieve IBS symptoms? Options to modulate gut microbiota include antibiotics, probiotics, synbiotics, altering gut motility, dietary manipulation, fecal transplantation, and use of bacteriophages. These therapies were discussed in the presentations of Pr. Uday Ghoshal and Pr. Giovanni Barbara. A role for antibiotics is most apparent in IBS-patients with SIBO. Both norfloxacin and rifaximin are significantly more effective in reducing IBS symptoms in SIBO- positive than SIBO-negative patients.

In IBS patients without constipation, according to Target 1 and 2 studies, rifaximin relieves global IBS-symptoms, and bloating. Target 3 and further studies have shown that rifaximin can be used repeatedly in relapsing IBS-D without loss of effect or appearance of bacterial resistance [3, 4]. Moreover, rifaximin transiently reduces bacterial counts in the feces but it also seems to have an eubiotic effect increasing Lactobacillaceae abundance.

The low FODMAP diet seems to reduce symptoms in some IBS patients but it also results in lower Bifidobacterium counts in the feces. In IBS patients responding to a low FODMAP diet the dysbiosis index increases, thus responsiveness to the diet may be predicted by faecal bacterial profiles. The efficacy of fecal microbial transplantation in IBS remains controversial as this was demonstrated in only one of the two large randomized controlled studies [5, 6]. As stated by Pr. Giovanni Barbara, the American College of Gastroenterology, based on a meta-analysis of 53 randomized controlled trials, concluded that probiotics reduce global IBS symptoms as well as bloating and flatulence [7]. To be consolidated, this recommendation should be founded on new, high-quality data.

However, not all probiotics are similar. Bifidobacterium infantis was shown by prof. Eamonn Quigley to relieve abdominal pain, bloating, and bowel function and improve quality of life in patients with all IBS-subtypes, and this appears to have anti-inflammatory and immunomodulating properties reducing CRP and TNFα in conditions like psoriasis, chronic fatigue syndrome, and ulcerative colitis. Furthermore, preliminary results suggest that in combination with Bifidobacterium longum it might also relieve depression in patients with IBS.

The microbiome and gut-brain axis

Based on preclinical studies, products of gut bacteria have been shown to change brain responses to stimuli, however the challenge is to translate these studies to clinical relevance. Huiying Wang showed in her recent study that Bifidobacterium longum strain modulates brain activity during social stress (associated with a cyberball game) in healthy volunteers based on evaluation using magnetoencephalography and QOL questionnaires. Besides an effect on neural oscillations, the strain also enhances a feeling of vitality and reduces mental fatigue compared to placebo over a four-week follow-up period. Pr. Paul Enck described the relationship between stress or anxiety and IBS as two-way as the symptoms can be both the cause and result of IBS. Based on a study of patients with IBS, Bifidobacterium longum was shown to correlate with a decrease in depression and anxiety scores, but at onset, these scores were insufficiently high to establish a diagnosis of depression or anxiety [8]. Thus, it is more appropriate to state that this probiotic affects mood rather than depression or anxiety. Similar to Bifidobacterium longum, rifaximin has also been shown to modulate brain activity and increase relaxation and reduce anxiety during social stress based on a double blindedrandomized trial of healthy volunteers evaluated by magnetoencephalography [9].

Sources

1 Tap J, Derrien M, Törnblom H et al. Identification of an intestinal microbiota signature associated with severity of irritable bowel syndrome. Gastroenterology 2017; 152: 111-23.

2 Ghoshal UC, Sukla R, Ghoshal U. Small intestinal bacterial overgrowth and irritable bowel syndrome: a bridge between functional organic dichotomy. Gut Liver 2017; 11: 196-208.

3 Lembo A, Pimentel M, Rao SS et al. Repeat treatment with rifaximin is safe and effective in patients with diarrhea-predominant irritable bowel. Gastroenterology 2016;151;1113-21

4 Pimentel M, Cash BD, Lembo A et al. Repeat rifaximin for irritable bowel syndrome: no clinically significant changes in stool microbial antibiotic sensitivity. Dig Dis Sci 2017;62:2455-2463

5 Johnsen PH, Hilpüsch F, Cavanagh JP, et al. Faecal microbiota transplantation versus placebo for moderate-to-severe irritable bowel syndrome: a double-blind, randomised, placebo-controlled, parallel-group, single-centre trial. Lancet Gastroenterol Hepatol 2018; 3: 17-24.

6 Halkjær SI, Christensen AH, Lo BZS, et al. Faecal microbiota transplantation alters gut microbiota in patients with irritable bowel syndrome: results from a randomised, double-blind placebo-controlled study. Gut. 2018;67(12):2107-2115.

7 Ford AC, Moayyedi P, Chey WD, et al. American College of Gastroenterology Monograph on management of irritable bowel syndrome. Am J Gastroenterol 2018; 113: 1-18.

8 Pinto-Sanchez MI, Hall GB, Ghajar K, et al. Probiotic Bifidobacterium longum NCC3001 reduces depression scores and alters brain activity: a pilot study in patients with irritable bowel syndrome. Gastroenterology 2017; 153: 448-59.

9 Wang H, Braun C, Enck P. Effects of rifaximin on central responses to social stress – a pilot experiment. Neurotherapeutics 2018; 15; 807-8.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Congress review

51st annual Meeting ESPGHAN

Congress review

By Dr. Solange Heller Rouassant
Pediatrician with specialty in Pediatric Gastroenterology and Nutrition México City, México Mexican Councilor of NASPGHAN

Gastric microbiota and Helicobacter pylori

Proteobacteria, Firmicutes, Actinobacteria, Bacteroidetes, and Fusobacteria are the most abundant phyla in H. pylori positive and H.pylori-negative patients and this gastric microbiota may play a role in the H. pylori-associated carcinogenicity [1]. Alarcón [2] characterized gastric microbiota in children with and without H. pylori; when detected, H. pylori dominated the microbial community, but when absent, there was a higher bacterial richness and diversity.

Gut microbiota in early life

Development of gut microbiota in early life is influenced by delivery mode, breast milk or formula feeding, antibiotic use, timing of introduction of solid foods and cessation of milk feeding. The gut microbiota of a newborn is transiently dominated by Enterobacteriaceae and Staphylococcus and very soon by Bifidobacterium and lactic acid bacteria. Bifidobacterium-dominated microbiota continues until complementary feeding starts [3].

  • Dukanovic [4] showed that C-section delivery and exclusive breast-feed infants have a relatively low abundance of Bacteroides in the infant stool; Bacteroides species were detected in 73% vaginal and 16% C-section samples.

  • Collado [4] demonstrated shared features between microbiota in maternal-infant pair and breast milk, suggesting a microbial transfer during lactation. Specific strains of Bacteroides, Bifidobacterium, Staphylococcus and Enterococcus genera were isolated from maternal infant gut and specific strains of Staphylococcus, Lactobacillus, Enterobacter and Acinetobacter from paired breast milk at 2 months of age.

Probiotics and synbiotics supplementation in early life

  • It has been reported that association between gut microbiota composition in early life and development of diseases exists [5]. Studies on early infant gut microbiome have shown that antibiotic resistant gene carriage is acquired early and may have long term sequelae.

  • Exclusively breastfed infants were supplemented with Bifidobacterium longum subsp. infantis (Casaburi [4]) as a targeted probiotic capable of remodeling gut microbiome with potential reduction of antibiotic gene reservoirs. It was concluded that colonization of high levels of this strain is a safe and non-invasive method to decrease a reservoir of genes that confer antibiotic resistance.

  • High levels of Bifidobacterium longum subsp. infantis in breast-fed infants, regardless of delivery mode, remained stable through the first year of life if breastfeeding was continued [4].

Infant formula supplementation with prebiotics and probiotics

Human milk oligosaccharides (HMOs) are unconjugated, solid and abundant compounds breast milk. The spectrum of HMOs in mother’s milk especially related to the mother’s secretor status modulates the bifidobacterial composition of the infant’s gut.

Gut of formula-fed infants has a lower relative abundance of Bifidobacteria and a higher microbial diversity. The use of prebiotics in infant formula increases the bifidobacterial fraction in the infant’s gut. Currently, available prebiotics (galacto- (GOS) and fructooligosaccharides (FOS)) are metabolized by Bifidobacteria, but not by the human host [5].

  • Puccio [6] supplemented an infant formula with 2 “fucosyllactose and lacto-N-neotetraose”, commonly found in human milk, with good results. An infant formula with GOS, FOS and Bifidobacterium breve compensates the delayed Bifidobacterium colonization in C-section-delivered infants, modulates gut microbiota and emulates conditions observed in vaginally born infants [6].

  • Comparison of two different infant formula supplemented with prebiotics only or prebiotics and probiotics showed similar gut microbiota profiles than breast-fed infants (Tims & Phavichir [4]).

Cow's milk allergy (CMA) prevention and management

  • Probiotics have been recommended for prevention of CMA even though more evidences are needed. Lactobacillus rhamnosus or Bifidobacterium lactis were administered daily from 35 weeks gestation to 6 months postpartum in mothers, and from birth until the age of two in children. Children that ingested Lactobacillus rhamnosus had a significant reduction of prevalence of eczema in childhood (Wickens [4]).

  • Extensive hydrolyzed infant formulas have been supplemented with L. rhamnosus for the management of IgE mediated CMA and development of immune tolerance. Clinical studies in healthy infants and infants suffering CMA showed that synbiotic-supplemented aminoacid-formulas (AAF) are hypoallergenic, well tolerated, and warranty normal growth.

  • Results of a multicenter, double blind, randomized controlled trial in infants with non IgE mediated CMA was presented (Candy [7]). Infants received a hypoallergenic, AAF formula containing a prebiotic blend of chicory-derived neutral oligofructose and long-chain Bifidobacterium breve . At week 8, significant differences on gut microbiota composition were present between groups, with higher percentages of Bifidobacteria in the symbiotic-AAF supplemented group. Modulation of gut microbiota using specific synbiotics may improve symptoms in infants with CMA.

Infantile colic

Evidence suggests that altered gut microbiota affects gut motor function and induce gas production in infants, resulting in abdominal pain/colic. Manipulation of gut microbiota may play a role in the management and prevention of infantile colic.

  • A Cochrane systematic review [4] of prophylactic probiotics in infantile colic included studies of Lactobacillus reuteri, multi-strain probiotics, Lactobacillus rhamnosus, Lactobacillus paracasei and Bifidobacterium animalis. This meta-analysis showed no differences in the use of several probiotics on primary outcome. However, a wider analysis suggested efficacy of probiotics for infantile colic (Ong [4]).
Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Congress review

Gut microbiota profiles in untreated children with attention deficit hyperactivity disorder

Commented article - Children's section

By Pr. Emmanuel Mas
Gastroenterology and Nutrition Department, Children’s Hospital, Toulouse, France

Photo : Gut microbiota profiles in untreated children with attention deficit hyperactivity disorder

Comments of the original article by Jiang et al. (Behavoural Brain Research 2018)

Although increasing evidence suggests a role for the gut microbiota in neurodevelopment, the actual structure and composition of microbiota in children with attention-deficit/hyperactivity disorder (ADHD) remain unclear.

Thus, the present study aimed to define the characteristics of gut microbiota in treatment-naive children with ADHD and to assess their relationship with the severity of ADHD symptoms. High-throughput pyrosequencing was used to investigate the microbiota composition in fecal matter from 51 children with ADHD and 32 healthy controls (HC).

An operational taxonomical unit (OTU)-level analysis revealed a significant decrease in the fractional representation of Faecalibacterium in children with ADHD compared to HC. In individuals with ADHD, the abundance of Faecalibacterium was negatively associated with parental reports of ADHD symptoms. However, there was no significant difference in alpha diversity between the ADHD and control groups.

This present findings support the involvement of microbiota alteration in psychiatric diseases and Faecalibacterium may represent a potential novel marker of gut microbiota in ADHD. Future studies are needed to validate these findings and to elucidate the temporal and causal relationships between these variables [1].

What is already known about this topic?

In recent years, the gut and gut microbiota have gained important status in human biology, perceived by some authors as a “second or third brain”. The gut-brain axis is being studied more precisely, and impairments in its function are being investigated with regards to various neurological and psychiatric disorders. Gut microbiota impairment has been highlighted in autism as well as in other psychiatric disorders. Regarding ADHD, no study has precisely analyzed the gut microbiota, but some authors suggest that a dysbiotic gut microbiota may play a role (symptoms improve under probiotics and worsen under antibiotics, and delivery by Caesarean section is a risk factor for the disease).

Image

Key points

  • The gut-brain axis plays an important role in various neurological and psychiatric disorders.

  • For ADHD, a disturbance of the gut microbiota (including a decrease in Faecalibacterium) may play a role, as suggested by this pilot study.

  • Further studies are needed to confirm this result and to assess whether correcting this dysbiosis will improve ADHD symptoms.

What are the main results of this study?

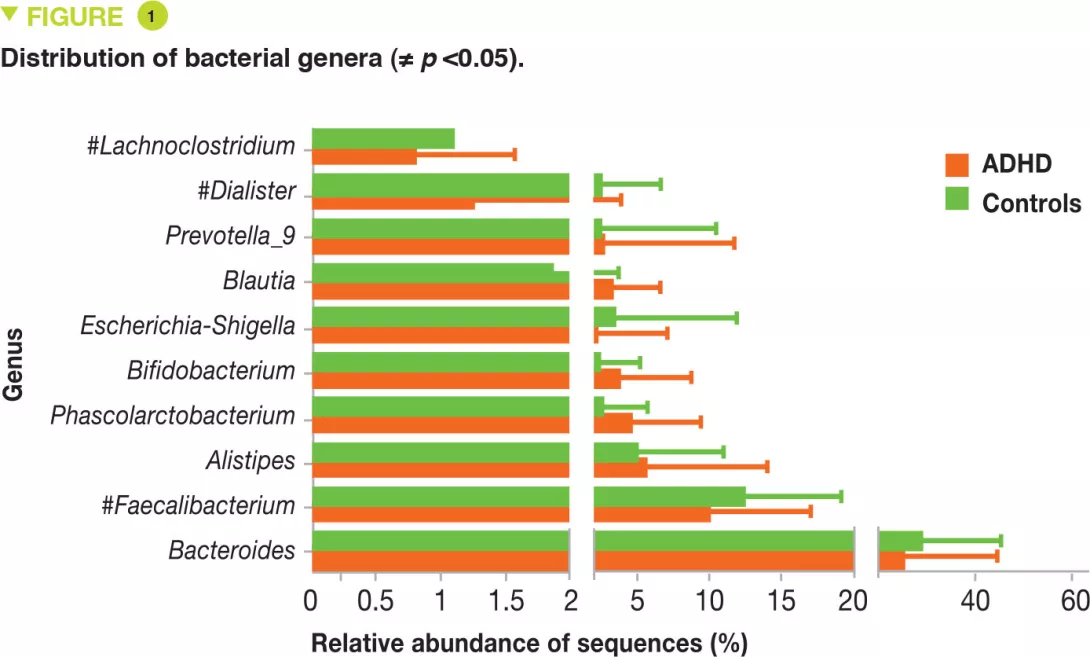
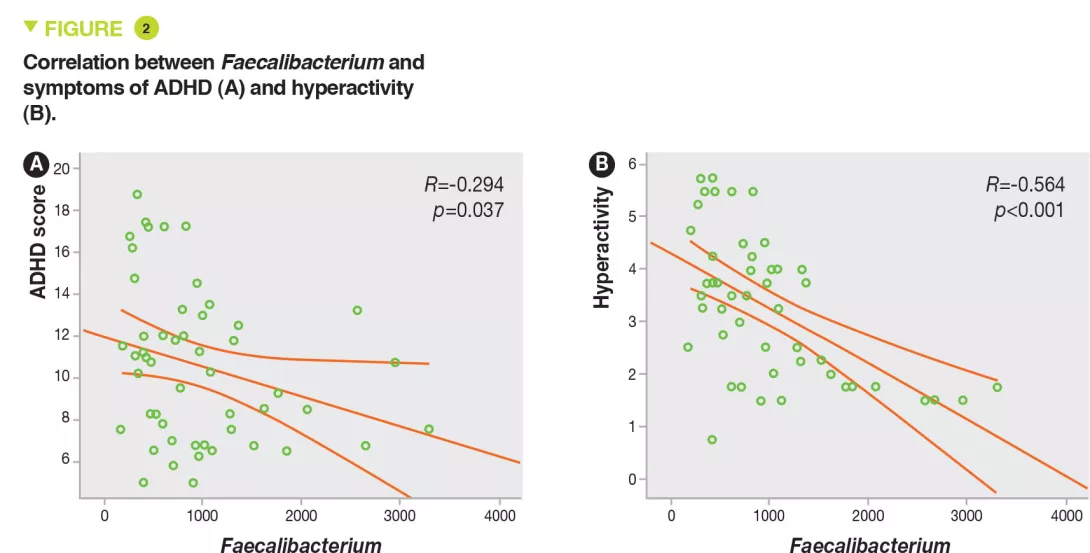
The authors included 51 children with ADHD, aged 6-10 years, and 32 matched controls from a Chinese hospital, from May 2015 to December 2016. The diagnosis of ADHD was based on the Kiddie- SADS-PL questionnaire that is included in the diagnostic manual of mental disorders: Diagnostic and Statistical Manual of Mental Steenvoorde-IV classification system (DSM-IV). Parents completed a questionnaire to assess the severity of ADHD symptoms (Conners Parent Rating Scales). Children with specific diets, probiotic or antibiotic treatment within the previous 2 months, digestive disorders, depressive or anxious symptoms, obesity, an atopic background, and/or medically treated for their ADHD were excluded. No difference was identified between the two groups for age, sex, BMI, delivery, or feeding formula (breast-feeding). The analysis of the gut microbiota, carried out through pyrosequencing of 16S RNA and OTU analysis, showed no difference in bacterial diversity (alpha and beta). The four major phyla in all samples were Firmicutes, Bacteroidetes, Proteobacteria and Actinetobacteria, with no difference between ADHD children and controls. However regarding genera, the levels of Faecalibacterium, Lachnoclostridium and Dialister were reduced in ADHD children (Figure 1). The abundance of Faecalibacterium negatively correlated with the severity of ADHD and the hyperactivity index (Figure 2).

Image

What are the  practical consequences?

If disturbance of the gut microbiota is involved in ADHD (as in other disorders), care should be taken to provide appropriate prescription of antibiotics in children, a fortiori in infants, to prevent further development of these disorders.

In ADHD, it might be useful to target Faecalibacterium by increasing its level in the gut. Dietetically, this is promoted by a Mediterranean diet and probably reduced by a Western diet. In addition to this dietary approach targeted on Faecalibacterium, it is also necessary to reduce gut inflammation, which is supported by a decrease in Faecalibacterium.

Conclusion

This pilot study has shown that the gut microbiota is disturbed in ADHD. This dysbiosis was more specifically related to Faecalibacterium, a genus that negatively correlated with the severity of ADHD symptoms.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Commented article

Gut microbiota involved in the pathogenesis of non-alcoholic fatty liver disease

Press review

By Pr. Markku Voutilainen
Turku University Faculty of Medicine; Turku University Hospital, Department of Gastroenterology, Turku, Finland

Non-alcoholic fatty liver disease (NAFLD) is the most common liver disease in western countries and affects 25-30% of the general population. NAFLD is classified into simple fatty liver disease with no or minimal inflammation, and steatohepatitis (NASH), which is characterized by steatosis, inflammation and fibrosis. NASH may lead to cirrhosis, which is a risk factor for hepatocellular carcinoma (HCC). NAFLD is the hepatic manifestation of metabolic syndrome.

Puri and Sanyal reviewed the role of the intestinal microbiome in NAFLD.[5] Increased adipose tissue mass with activation of the innate immune system leads to insulin resistance. Altered gut microbiota and increased intestinal permeability cause immune activation. Microbiome may also affect extra-intestinal organs by translocation, gut-derived neurohumoral signalling, and altering the nutritional substances absorbed from the intestine.

Chen and co-workers examined gut microbiota in the bile acid metabolism.[6] Microbiota produces enzymes that in the intestines convert primary bile acids (synthesised and conjugated in the liver) into secondary bile acids. Dysbiosis may lead to decreased synthesis of secondary bile acids, which in turn diminishes the activation of nuclear receptors such as farnesoid X receptor (FXR), pregnane X receptor, Takeda G-protein-coupled bile acid protein 5 (TGR5) and vitamin D receptor. These receptors play important roles in energy regulation and their dysfunction may play a role in the pathogenesis of NAFLD. Dysbiosis leads to increased bile acid deconjugation and is associated with disturbed lipid and cholesterol metabolism, weight increase and disturbed signalling.[6] Gut microbiota metabolises bile acids, conversely, bile acids are needed to maintain normal gut microbiota.

The gut microbiota is changed in NAFLD, but there is no uniform pattern.[6] Bacteria converting primary bile acids (C. leptum for example) are decreased in the faeces of NAFLD patients. Decreased FXR increases the synthesis of primary bile acids, gluconeogenesis, triglycerides and very-low-density lipoprotein synthesis. Thus decreased FXR as well as TGR5 may be involved in NAFLD pathogenesis. Modulation of gut microbiota could be an option for the treatment of NAFLD. Probiotics could adjust the whole bile acid pool instead of individual nuclear receptors.[6]

Variable definitions, histologic assessments and methods, as well as different bioinformatics approaches have been used. Thus it is difficult to draw generalisable conclusions of the microbiota changes in the pathogenesis of NAFLD.[5] The mechanisms that link microbiota changes to NAFLD pathogenesis are increased energy extraction in the gut and increased free fatty acid hepatic uptake, altered gut barrier function and endotoxemia with inflammation, altered bile acid and choline metabolism.

Loman and co-authors analysed the impact of pre- and probiotic treatment on NAFLD.[7] They identified 25 studies that fulfilled the PICOS* criteria: 9 assessed prebiotic, 11 probiotic and 7 symbiotic treatments. These therapies significantly reduced body mass index (BMI), hepatic transaminases and ν-glutamyltransferase, cholesterol and triglycerides levels. The effect of pro- and prebiotics were similar on BMI, liver enzymes and high-density cholesterol. The major weaknesses of the stu- dies were the lack of intestinal microbiota analysis, the heterogeneity of treatments, and their short duration. The present meta-analysis was, however, the first one to report simultaneous changes induced by microbiota treatment on weight, lipid metabolism and inflammation in NAFLD.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Press review

Proton pump inhibitors modify gut microbiome

Press review

By Pr. Markku Voutilainen
Turku University Faculty of Medicine; Turku University Hospital, Department of Gastroenterology, Turku, Finland

Proton pump inhibitors (PPIs), which are nowadays ones of the most widely used medicines even if about half of the prescriptions lack an evidence-based indication, have a central role in the treatment of peptic ulcer and gastro-oesophageal reflux disease. PPIs inhibit acid secretion from gastric parietal cells. PPI-induced hypochlorhydria may increase the risk of infections.

Mishiro et al. investigated the impact of 20 mg daily esomeprazole for 1 month on saliva, periodontal pocket fluid and fecal microbiota in 10 healthy volunteers.[1] Colonic microbiota contained the greatest number of species. Firmicutes, Bacteroidetes, Actinobacteria and Proteobacteria were the most abundant species in faeces, whereas Firmicutes, Proteobacteria, Bacteroidetes and Fusobacteria were the most common in saliva and periodontal pocket fluid. PPI caused a significant reduction in the diversity of salivary microbiota. Streptococci, which are predominantly found in the upper gastrointestinal tract, were increased in faeces and also in saliva and periodontal pocket after PPI treatment.[1]

Antibiotics and acid-suppressive medications cause dysbiosis. Stark et al. performed a retrospective study with 333,353 US children.[2] PPI prescriptions were associated with obesity, each additional antibiotic class increased the risk of obesity, and each additional 30-day prescription of acid-suppressive medication strengthened the association with obesity.

Mailhe et al. examined the gastrointestinal microbiota composition of 6 patients who underwent gastroscopy and colonoscopy.[3] Samples were obtained from stomach, duodenum, ileum, and colon. Culturomics was performed with mass spectometry MALDI-TOF and metagenomics targeting the V3-V4 region in the 16S rRNA. In all, 368 bacterial species were observed (37 new species): 110 from the stomach, 106 from the duodenum and 235 from the left colon. The upper gut contained less aero-intolerant species and less rich microbiota compared with the lower gut. Three patients used long-term PPI treatment; their gastric pH and bacterial diversity were higher compared with those not using PPI.

Investigators from Cleveland, have reviewed the impact of PPIs on gut microbiome [4]. The main consequence of PPI treatment is the increase in gastric pH. PPI treatment may lead to excess Streptococcus gastric colonisation, which may cause dyspeptic symptoms. Small bowel bacterial overgrowth risk is moderately increased during PPI treatment.[4] PPI and antibiotics increase Clostridium difficile infection (CDI) risk. PPI treatment may also increase spontaneous bacterial peritonitis risk in hepatic cirrhosis. A statistical association between PPI use and the incidence of Salmonella and Campylobacter infections has been reported.

Observational studies reporting associations between PPI use and side effects do not necessarily prove causal relationship. PPI users are often sicker than non-users, which could partially explain the increase of side effects. Anyhow, PPIs should be used only on evidence-based indications with lowest effective doses and should be stopped when the treatment response has been achieved.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Press review

The food additive trehalose increases the virulence of epidemic clostridium difficile

Commented articles - Adults' section

By Pr. Harry Sokol
Gastroenterology and Nutrition Department, Saint-Antoine Hospital, Paris, France

Photo : The food additive trehalose increases the virulence of epidemic clostridium difficile

Comments of the original article by Collins de Collins et al. (Nature 2018)

Clostridium difficile has recently increased to become a dominant nosocomial pathogen in North America and Europe, although little is known about what has driven this emergence. Here the authors show that two epidemic ribotypes (RT027 and RT078) have acquired unique mechanisms to metabolize low concentrations of the disaccharide trehalose. RT027 strains contain a single point mutation in the trehalose repressor* that increases the sensitivity of this ribotype to trehalose by more than 500-fold.

Furthermore, dietary trehalose increases the virulence of a RT027 strain in a mouse model of infection. RT078 strains acquired a cluster of four genes involved in trehalose metabolism, including a PTS permease that is both necessary and sufficient for growth on low concentrations of trehalose. The authors propose that the implementation of trehalose as a food additive into the human diet, shortly before the emergence of these two epidemic lineages, helped select for their emergence and contributed to hypervirulence [1].

What is already known about this topic?

Whole-genome sequencing analysis of C. difficile RT027 strains has shown that two independent lines have emerged in North America between 2000 and 2003 [2]. A comparison with pre-epidemic RT027 strains has shown that the epidemic strains have acquired a mutation in the gyrA gene, that has led to an increased resistance to fluoroquinolone antibiotics. While the development of this resistance has certainly played a role in the spread of RT027 strains, it has also been observed in non-epidemic C. difficile ribotypes and identified in strains from the middle of the 1980s. Thus, other factors have probably contributed to the emergence of epidemic RT027 strains. The prevalence of a second C. difficile ribotype, RT078, has increased tenfold in hospitals and clinics between 1995 and 2007, and has been associated with increased severity [3]. However, the mechanisms involved in the increased virulence remain unknown. Since RT027 and RT078 lines are phylogenetically distant from each other, the changes that have simultaneously led to an increase in prevalence and severity of infection might be due to independent mechanisms.

What are the main results of this study?

RT027 strains have been shown to have a competitive advantage over other strains both in vitro and in mouse models of C. difficile infection. To investigate the mechanisms involved, the authors examined the use of different carbon sources by the various strains and highlighted an increased capacity of RT027 strains to metabolise the disaccharide, trehalose. By comparing the genomes of many C. difficile strains, the authors identified a putative responsible enzyme, phosphotrehalase enzyme (TreA), which metabolises trehalose-6-phosphate into glucose and glucose-6-phosphate. The authors then observed that this gene was activated in RT027 strains at a concentration of trehalose 500-fold lower than that for the other C. difficile strains. More detailed analyses have identified a polymorphism in the TreA transcriptional repressor (TreR) in all RT027 strains and in other closely related strains responsible for epidemics in Europe and Australia. To determine whether the capacity to metabolise trehalose has an impact on virulence, the authors administered it orally to mice transplanted with human microbiota and infected with either a RT027 strain (R20291) or the same strain deleted for the TreA gene (R20291Δ TreA), and therefore unable to metabolise trehalose. Mortality was much lower with the R20291Δ TreA strain (Figure 1).

Image

Key points

  • C. difficile infection outbreaks with hypervirulent epidemic strains (RT027 and RT078) emerged in the early 2000s.

  • Trehalose is a highly resistant disaccharide that has been used in the food industry since 2000.

  • RT027 and RT078 strains have acquired a competitive advantage that allows them to metabolise trehalose, even at low concentrations, which increases their virulence.

In a second experiment, the authors infected mice transplanted with human microbiota with the RT027 strain (R20291) in the presence or absence of trehalose in the drinking water (given at a dose equivalent to that received during a standard human meal). Mortality was much higher in the presence of trehalose. The two combined experiments confirm the assumption that trehalose in food contributes to the severity of RT027 strains. The genetic analysis of RT078 strains demonstrated an insertion of 4 genes, encoding a second copy of phosphotrehalase (TreA2) and its repressor (TreR2), as well as 2 other related genes. A mutation- and overexpression-based approach confirmed that this insertion was responsible for the capacity of RT078 strains to grow in the presence of trehalose.

What are the practical consequences?

Trehalose is an extremely stable sugar that is resistant to both high temperatures and hydrolysis. Considered ideal for use in the food industry, it has been mainly used since 2000, when a new low-cost production process was discovered [3]. Its use has been authorized in food by the Food and Drug Administration (FDA) in 2000 and by European institutions in 2001. The wide adoption of trehalose coincides with the emergence of infection outbreaks with RT027 and RT078 strains. Overall, the results suggest a causal role for trehalose in food in the emergence of these hypervirulent epidemic strains of C. difficile.

Conclusion

The wide adoption of trehalose in the food industry coincides with the emergence of infection outbreaks with C. difficile RT027 and RT078 strains. These strains have acquired the capacity to metabolise trehalose at low concentrations, conferring them a selective advantage over other strains in an ecosystem in which trehalose has been introduced. This capacity to metabolise trehalose increases their virulence. Overall, the results suggest a causal role for trehalose in food in the emergence of these hypervirulent epidemic strains of C. difficile.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Commented article

The gut microbiota: issues and challenges in the management of metabolic disorders

Congress review 

By Pr. Jaafar Heikel
African Centre for Health Research and Studies, Mohammed-VI University Polytechnique, Morocco

The 5th International Congress on Nutrition, organized by the Tunisian Association of Nutrition Sciences, was held on November 9-11, 2018 in Hammamet, Tunisia. This edition sheds light on the link between the gut microbiota and metabolic disorders such as diabetes and obesity.

The microbiota: a new player in our understanding of metabolic disorders

Like most African countries, Maghreb countries are experiencing a demographic, epidemiological, and nutritional transition. In 2018, as in developed countries, there were more deaths from non-communicable diseases (75%) than from infectious diseases. Excess weight, obesity, diabetes, and hypertension have become a public health concern, with prevalence exceeding 50, 20, 10 and 30%, respectively. Classic approaches to management have proved to be inadequate due to a number of determinant factors.

Although the first published studies on gut microbiota date back to the 1960s, it has only been in the last fifteen years or so that new work has highlighted the role of the microbiota in the maintenance of chronic inflammatory states, insulin resistance, or obesity, by acting through different mechanisms.[1] Phenomena such as metabolic endotoxemia and bacterial translocation, resulting from the passage of lipopolysaccharides (LPS) into the systemic circulation, appear to be implicated.

Whether the disorder is diabetes, obesity, or metabolic syndrome, the quantity, quality, and diversity of microbiota (especially the phyla Firmicutes, Bacteroidetes, and Actinobacteria) underlie the cascade of responses leading to increased intestinal permeability (“leaky gut”), mobilization of pro-inflammatory cells, and induction of specific cell transport proteins. Gut micro-organisms are even thought to play a positive role in the immune system through exposure to bacterial LPS, which may be tolerated in some cases. Metabolic disorders, such as those caused by a high-fat diet, for example, could be avoidable by inhibiting LPS receptors (CD14/Toll-like receptor 4; TLR-4).

Bacteria-host cell communication: impact on metabolism

When subjected to a high-fat, low-fibre diet, the bacteria that compose the gut microbiota undergo changes on their surface (LPS) that trigger immune responses and local inflammatory reactions. These events increase intestinal permeability, allowing inflammatory components to enter the bloodstream.[2] Recent work has highlighted this role of dietary fat in dysbiosis and endotoxemia, initially in the oral microbiota. The process is thought to be triggered first by glycoprotein CD36 (increased sensitivity to the taste of fat), and then augmented at the level of the microbiota of the gustatory papillae (rich in Streptococci), thus creating a local inflammatory process identical to that seen in the intestinal wall. In addition, the texture and type of fat – saturated or polyunsaturated – and the involvement of bile salts have also been suggested as factors that could help account for metabolic disorders and the risk of obesity.

The role of certain bacterial phyla such as Firmicutes, Bacteroidetes, and Actinobacteria in metabolic endotoxemia, based on studies in both axenic mice and humans, is well established. For instance, in the mouse, a high-fat diet increases the concentration of circulating LPS, leading to metabolic changes linked to obesity, and analysis of gut microbiota reveals a significant decrease in Bifidobacterium spp. and Bacteroides-associated gut bacteria. In addition, a negative association has been observed between endotoxemia and the number of Bifidobacteria; the latter can reduce the level of LPS and improve intestinal barrier function,[3-5] as well as intestinal barrier integrity, which is crucial to prevent passage of bacterial components from the intestinal lumen into the bloodstream and host tissues.

What is the impact on management of metabolic disorders?

The major focus is currently the identification of specific bacteria, with a view to offering clinicians the tools to prevent or manage patients at risk of, or already suffering from, a metabolic disorder.[6- 7] Restoring equilibrium to the intestinal ecosystem or re-balancing the microbiota is a challenge in patients with intestinal dysbiosis, which is determined by epigenetics, the environment, diet, lifestyle, history of antibiotic treatments, and state of health.

Thus, Firmicutes and Bacteroidetes, which account for the majority of our gut microbiome, affect the risk of metabolic diseases, relative to their abundance. Moreover, recent studies on specific bacteria associated with energy and carbohydrate metabolism have been carried out in the laboratory. These studies seem to show, for example, that Akkermansia muciniphila, even pasteurized, improves intestinal barrier function and the thickness of the mucus layer, and may thus influence insulin resistance and obesity. The oxygen sensitivity of this species has so far limited its ability to be cultured and restricted its study in humans.

Other gut bacteria, such as Faecalibacterium prausnitzii, play a beneficial role and may offer therapeutic strategies based on the use of specific probiotics. In addition, other elements should be considered, such as the interactions between the host, microbiota, and brain, leading to the concepts of the taste cortex, pleasure circuit, and microbial agents that mediate obesity, which are of particular importance. The significant failure to manage obesity may be explained by approaches that lack optimal management of the dynamic states of the gut microbiota over time.

Consequently, today’s challenge is to better understand “obesogenic and diabetogenic microbiotic factors” in order to shape the way low-fat and low-carbohydrate nutritional diets, appropriate physical activity, probiotic and prebiotic supplementation, as well as faecal transplantation may be used in the future.

The role of these factors needs to be clarified with regards to their complementarity and based on an integrated preventative, but also therapeutic, approach.[8] Sufficiently large cohort studies should help confirm the role of the oral and gut microbiota in the development of transient and chronic inflammatory states underlying metabolic disorders – and probably other pathological states, such as cancers or some psychiatric conditions.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Congress review