Can we target microbiota in the management of children with functional abdominal pain disorders?

By Iulia Florentina Tincu, Roxana Elena Matran, Cristina Adriana Becheanu
Carol Davila University of Medecine and Pharmacy, Romania
TFI-Chez-enfant-image1

The dysbiotic gut in functional abdominal pain disorders in children

Functional abdominal pain disorders (FAPDs), also referred to as functional gastrointestinal disorders (FGIDs), represent the one of the main etiologies of chronic abdominal pain in the pediatric population that involve interplay among regulatory factors in the enteric and central nervous systems 1. The ongoing classification system, ROME IV, distinguishes several pain-predominant FGIDs based on their recognizable patterns of symptoms, such as functional dyspepsia (FD), irritable bowel syndrome (IBS), abdominal migraine, and FAP-not otherwise specified (FAP-NOS) 2. During the past two decades numerous studies researched possible causes and underlying mechanisms of appearance, but the clear pathophysiology is yet to be revealed, despite pediatric neurogastroenterology findings in terms of intestinal motility, signaling molecules, changes in microbiota or epigenetic mechanisms 3. Gut microbiota modifications, known as a dysbiotic gut, may play a role in functional abdominal pain disorders through gut immunity and integrity alteration 4, 5. Several studies have reported a lower level of microbial diversity in patients with functional abdominal pain disorders 6, 7 and species such as Lactobacilli and Bifidobacteria are heavily altered 8. Thus, a growing body of clinical data have been gathered around using probiotics in functional disorders’ management, although study data are lacking on children 9.

Research insights

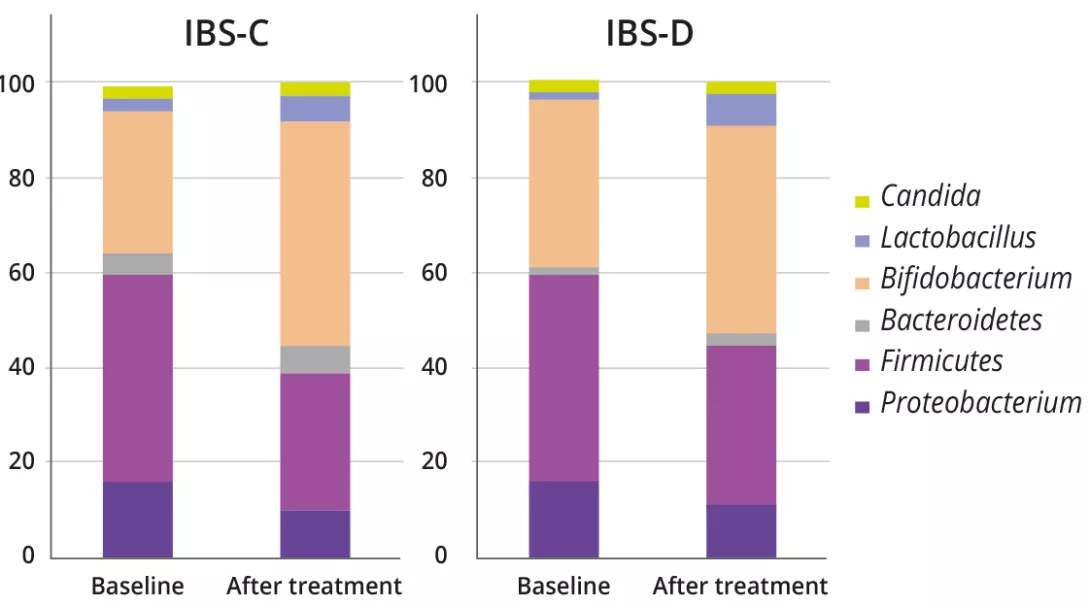
The analysis of microbiota in 18 patients with FGIDs provided data about intestinal dysbiosis at the moment of the diagnosis and its changes over a period of three months of treatment with specific strains of probiotics and prebiotics (figure 1).

Individuals. Age 4-14 years and diagnosed with functional abdominal pain disorders (functional dyspepsia and irritable bowel syndrome) according to ROME IV criteria.

Intervention. Six bacterial strains (Lactobacillus rhamnosus R0011, Lactobacillus casei R0215, Bifidobacterium lactis BI-04, Lactobacillus acidophilus La-14, Bifidobacterium longum BB536, Lactobacillus plantarum R1012) and 210 mg of fructo-oligosaccharides-inulin. One capsule was administered orally, daily, for 12 weeks, and the medication was provided by the healthcare practitioners.

Clinical outcome. The patients were scored for severity of abdominal discomfort, dyspepsia, flatulence, and epigastric pain on a ten-point ordinate (numerical rating) scale.
Image

Fecal samples were collected from participants before and after treatment using a special laboratory kit with two sterile containers, which were then brought to the laboratory in conditions depending on the time spent from collection to laboratory delivery: if the interval was less than 24 hours, both containers were stored and transported in cooled conditions at 4 °C; if the period between stool elimination and laboratory delivery was more than 24 hours, one container was stored in a frozen condition at – 80 °C until analysis, and the other one was cooled at 4 °C. Stool samples were analyzed using the test Colonic dysbiosis-basic profile (SBY 1) performed by Synlab-Germany. Microbiota composition was expressed as number of colony forming units (CFU) for various aerobic/anaerobic bacterial and fungal species. The analysis provided data on fecal pH, IgA in μg/mL (normal ranges 510–2,040 μg/mL), lactoferine μg/ mL (normal ranges < 7.2), calprotectin in mg/kg (normal ranges < 50.0 negative, 50–99 intermediary, > 100 positive).

In the fecal microbial analysis, there was an increasing proportion of bacterial genera associated with health benefits (e.g., Bifidobacterium and Lactobacillus), for both IBS-C and IBS-D (IBS-C: 31.1 ± 16.7% vs. 47.7 ± 13.5%, p = 0.01; IBS-D: 35.8 ± 16.2% vs. 44.1 ± 15.1%, p = 0.01). On the other hand, genera of harmful bacteria, including Escherichia, Clostridium, and Klebsiella were proven to decrease after treatment (21.3 ± 16.9% vs. 16.3 ± 9.6%, p = 0.02).

No particularities were found in children with FD. At baseline, before any symbiotic intervention, Bifidobacterium profiles were significantly different between IBS-C and IBS-D (87.14 ± 23.19 vs. 71.37 ± 12.24; p = 0.02), with lower counts in IBS-D. The symbiotic administration had a significant effect on bacterial profiles from baseline to the end of treatment in both IBS-C and IBS-D groups (Table 1).

Image

Practical consequences

The clinical symptoms in study population were more diminished after treatment, with statistical significance, suggesting that influencing gut dysbiosis might also reduce patients’ burden and improve clinical scores.

Overall, 14 (78%) patients reported treatment success (defined as no pain). The proportion of patients with adequate symptom relief was higher in the IBS-D than in the IBS-C group; however, the difference was not statistically significant (74.4% vs. 61.9%, p = 0.230). In both IBS-C and IBS-D groups, scores on the Bristol scale improved significantly after intervention (baseline vs. after treatment; 2.8 ± 0.6 vs. 3.9 ± 0.9, p = 0.03, 6.1 ± 0.9 vs. 4.1 ± 1.0, P = 0.01, respectively). Abdominal distension and flatulence were significantly improved in both IBS-C and IBS-D groups (IBS-C: 6.5 ± 2.8 vs. 3.7 ± 1.8, p = 0.01; IBS-D: 5.9 ± 2.2 vs. 2.9 ± 1.8, p = 0.01).

Key points
  • The exploration of human microbiome revealed over time that dysbiosis has a substantial role in pathogenesis of functional abdominal pain disorders, although specific profiles as early biomarkers are still far from current practical use.
  • There is a real need for future unitary studies in terms of microbiota-modifying interventions for a broader landscape of pediatric disorders.
  • We can conclude that a novel perspective in the growing field of microbiota modifying therapies in children with FGIDs may offer valuable insights of disease mechanisms so personalized therapeutic strategies might improve patients’ symptoms.

Conclusion

Microbiota targeted intervention might result in significant changes in the gastrointestinal dysbiosis and this finding is related to gastrointestinal symptoms relief in patients with functional abdominal pain disorders.

Sources:
  1. Royle JT, Hamel-Lambert J. Biopsychosocial issues in functional abdominal pain. Pediatr Ann 2001; 30: 32-40. 
  2. Hyams JS, Di Lorenzo C, Saps M, Shulman RJ, Staiano A, van Tilburg M. Functional Disorders: Children and Adolescents. Gastroenterology 2016: S0016-5085. 
  3. Oświęcimska J, Szymlak A, Roczniak W, Girczys-Połedniok K, Kwiecień J. New insights into the pathogenesis and treatment of irritable bowel syndrome. Adv Med Sci 2017; 62: 17-30. 
  4. Chong PP, Chin VK, Looi CY, Wong WF, Madhavan P, Yong VC. The Microbiome and Irritable Bowel Syndrome - A Review on the Pathophysiology, Current Research and Future Therapy. Front Microbiol 2019; 10: 1136. Erratum in: Front Microbiol 2019; 10: 1870. 
  5. Pantazi AC, Mihai CM, Lupu A, et al. Gut Microbiota Profile and Functional Gastrointestinal Disorders in Infants: A Longitudinal Study. Nutrients 2025; 17: 701. 
  6. Carroll IM, Ringel-Kulka T, Keku TO, et al. Molecular analysis of the luminal- and mucosal-associated intestinal microbiota in diarrhea-predominant irritable bowel syndrome. Am J Physiol Gastrointest Liver Physiol 2011; 301: G799-807. 
  7. Rosa D, Zablah RA, Vazquez-Frias R. Unraveling the complexity of Disorders of the Gut-Brain Interaction: the gut microbiota connection in children. Front Pediatr 2024; 11: 1283389. 
  8. Bellini M, Gambaccini D, Stasi C, Urbano MT, Marchi S, Usai-Satta P. Irritable bowel syndrome: a disease still searching for pathogenesis, diagnosis and therapy. World J Gastroenterol 2014; 20: 8807-20. 
  9. Klem F, Wadhwa A, Prokop LJ, et al. Prevalence, Risk Factors, and Outcomes of Irritable Bowel Syndrome After Infectious Enteritis: A Systematic Review and Meta-analysis. Gastroenterology 2017; 152: 1042-54.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Off

Interconnected pathways link plasma lipids, fecal microbiota and brain activity to cognition related to childhood malnutrition

COMMENTED ARTICLE - Children's section

By Prof. Emmanuel Mas
Gastroenterology and Nutrition Department, Children's Hospital, Toulouse, France

Comments on the original article by Portlock et al., Nat Commun 1

Malnutrition affects more than 30 million children every year and has profound immediate and long-lasting repercussions. Children who survive often suffer long-lasting neurocognitive sequelae that impact on their school performance and socio-economic status. The mechanisms behind these consequences are poorly understood. Using SHAP models interpreted by multisystem random forest and network analysis, the authors show that moderate acute malnutrition (MAM) is associated with increased stool Rothia mucilaginosa and Streptococcus salivarius and decreased Bacteroides fragilis in a group of one-year-old children in Dhaka, Bangladesh. These changes in the microbiome form interconnected pathways involving reduced plasma levels of oddchain fatty acids, decreased electroencephalogram gamma and beta power in temporal and frontal brain regions, and reduced vocalization. These results support the hypothesis that prolonged colonization with oral commensal species delays the development of the gut and brain microbiome. Although causal links need to be validated by empirical data, this study provides useful information to improve interventions targeting neurodevelopmental deficits associated with MAM.

What do we already know about this subject

Childhood malnutrition is a major public health problem and one of the leading causes of death before the age of five. Moderate acute malnutrition (MAM) is associated with delayed neurocognitive development, but the link remains poorly understood. It is also associated with dysbiosis of the gut microbiota (GM), whose establishment is slowed and marked by enrichment in Bifidobacterium and Escherichia species. These disturbances in the gut microbiota could have an impact on cerebral development via the gut-brain axis, due to defective nutrient absorption or accumulation of toxic metabolites. This inter-organ communication could be mediated indirectly by plasma lipids, as lipids are the essential constituent of the brain and are modulated by MI metabolites  such as bile acids.

What are the main insights from this study?

The study was carried out in the Mirpur region of Bangladesh, and compared 159 children with MAM with 75 well-nourished controls at 12 months of age. MAM was defined by a weight/height ratio between -2 and -3 z-scores. The MAM group was significantly associated with social-demographic factors (toilet, mode of delivery and water treatment - kettle).

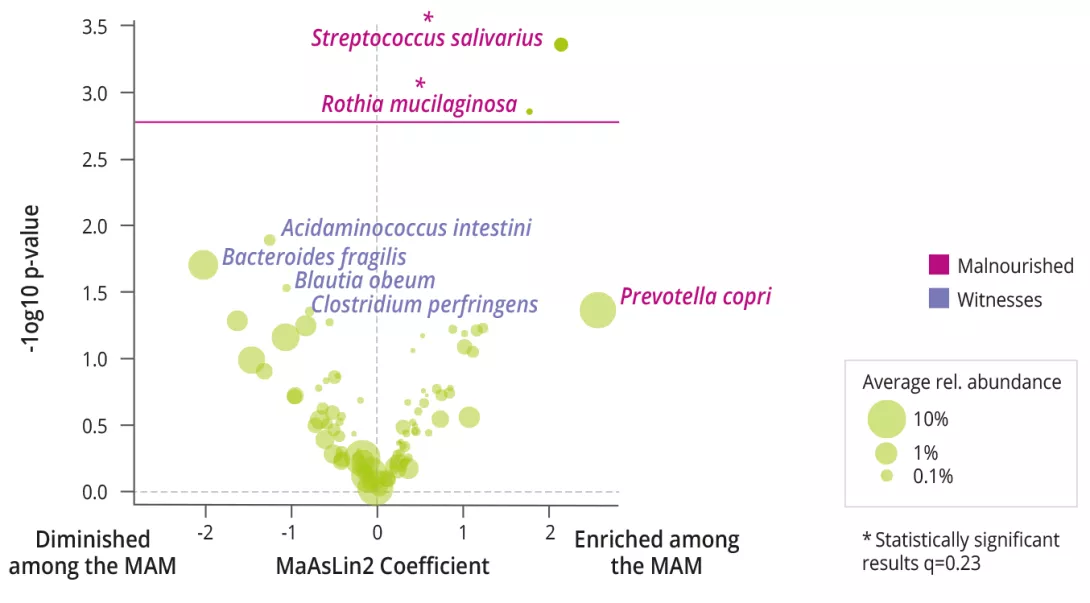
MAM was associated with decreased bacterial alpha diversity (Shannon), increased prevalence and abundance of Rothia mucilaginosa and Streptococcus salivarius (figure 1), and an increased Bacteroidetes/Firmicutes ratio. Functional analyses of the MI showed no differences.

Image

The electroencephalogram (EEG) showed a significant decrease in beta (12-30 Hz) and gamma (30-45 Hz) frequencies in the temporal and frontal regions of children with MAM. Significant decreases in expressive communication, fine and gross motor scores, and vocalization were also observed.

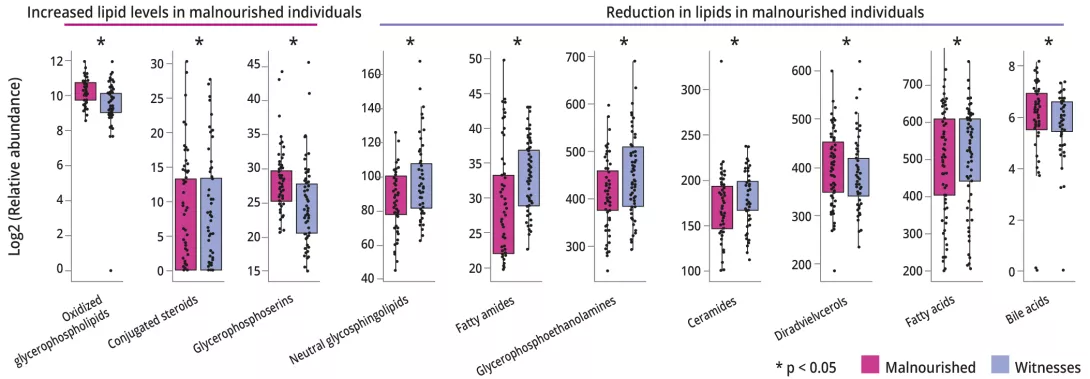
After adjusting for mode of delivery, gender and duration of exclusive breastfeeding, MAM was associated with changes in plasma lipidome, with relative abundance increased by 128 (16%) compounds and decreased by 189 (24%) (figure 2).

Image

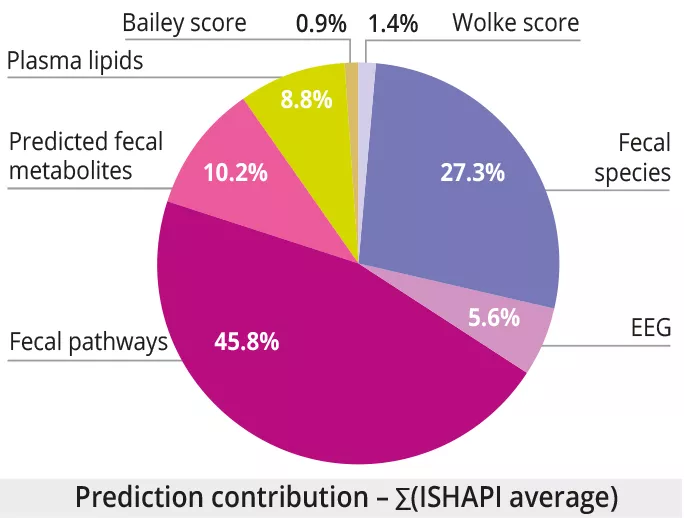
Integration of multimodal data showed that the best predictors of MAM at 12 months were: 1) plasma lipids (AUROC = 0.95 0.05); 2) brain and behavioral measures (Wolke score, EEG, Bayley score) (AUROC = 0.73±0.05, 0.71±0.10, 0.68±0.07 respectively) ; 3) the taxonomic, functional and predicted metabolite profile of the fecal microbiome (AUROC = 0.56±0.07, 0.53±0.07, 0.52±0.06). Note the high proportion of data related to the fecal microbiome for predicting MAM in multimodal analysis, despite the poor performance of the fecal microbiome (figure 3).

Multimodal network analysis predicted that a cluster of B. fragilis, pyruvate fermentation pathways, plasma ceramides, EEG and expressive communication was strongly correlated with good nutritional status at 12 months. Finally, the strongest effect as an interspecies interaction was observed between R. mucilaginosa and S.salivarius, whose combined presence amplified the prediction of MAM at 12 months.

Image

What are the consequences in practice?

This study shows the importance of GM in the nutritional status of infants. The presence of commensal gram-positive and facultative anaerobic oral bacteria such as R. mucilaginosa and S. salivarius may be responsible for deregulation of bile acids. This could lead to lipid changes that are important for brain development.

In addition, it is important to highlight the benefit of B. fragilis in relation to fermentation pathways on nutritional status at 12 months.

Key point
  • Intestinal persistence of commensal bacteria Rothia mucilaginosa and Streptococcus salivarius in MAM children overrides colonization by Bacteroides fragilis. This interferes with the synthesis of
    fatty acids essential for brain development

Conclusion

This study highlights that dysbiosis of the gut microbiota is associated with abnormalities in brain development present in children with MAM, via changes in plasma lipids.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Commented article Off

Towards a health-associated core keystone (key species) index for the human gut microbiota

COMMENTED ARTICLE - Adults’ section

By Pr. Harry Sokol
Gastroenterology and Nutrition Department, Saint-Antoine Hospital, Paris, France

Comments on the original article by Goel et al., Cell Reports 2025 1

Foundation HUB page

A robust index of gut microbiome taxa, encompassing their association with host health and microbiome resilience, would be valuable for the development and optimisation of microbiomebased therapeutics. In this article the authors present a single ranked order for 201 taxa, the Health-Associated Core Keystone (HACK) index, derived using their prevalence/community association in non-diseased subjects, their temporal stability and their association with host health. This index was constructed using 127 discovery cohorts and 14 validation datasets (a cumulative total of 45,424 gut microbiomes from subjects aged over 18 years, representing 42 countries, 28 disease categories and 10,021 longitudinal samples). The authors show that this index is reproducible regardless of microbiome profiling strategies and cohort lifestyle. Specific consortia of high HACK index taxa respond positively to Mediterranean diet-based interventions, are associated with better immune checkpoint inhibitor responsiveness and display specific functional profiles at the genome-level. The availability of HACK indices thus provides a rational basis for comparing microbiomes and facilitating the selection and design of microbiome-based therapies.

What do we already know about this subject?

Gut microbiome-based therapeutics (including probiotics, live biotherapeutic products, prebiotics/synbiotics and faecal transplantation) aim to restore a healthy microbiota, but with varying degrees of success depending on the population. To optimise these approaches, a consensual definition of a “healthy” microbiome would be needed - a challenging task due to the high degree of interindividual variability.
However, meta-analyses reveal taxa that are consistently depleted or enriched across multiple diseases, suggesting that microbes can be positioned along a spectrum of association with host health 2, 3. High-ranking species on this scale would have the greatest potential: i) as direct therapeutic agents or targets for enrichment;ii) as markers of clinical efficacy. The authors therefore propose creating a priority index integrating three criteria: positive association with health, contribution to microbiota stability and strong community “interaction”. This index, which can be applied to large public datasets, would serve as a rational tool for selecting and evaluating future microbial therapeutic strategies.

What are the main insights from this study?

Using a discovery cohort comprising 39,926 gut microbiomes from 127 cohorts (including cross-sectional and longitudinal data, spanning 42 countries and 28 different diseases), the authors generated a ranking of 201 prevalent (core) gut microbiota taxa (those detected in ≥ 5% of samples in ≥ 50% of the studied cohorts), the HACK index (Health-Associated Core Keystone Index), each being assigned a score based on three quantifiable properties: i) prevalence/community association in non-diseased subjects; ii) temporal stability; and iii) negative association with disease.

The HACK index was calculated as the product of two scores: i) the mean of the association scores of a taxon for all the three properties; and ii) a reward score assessing the similarity (or how evenly distributed) these three scores were with respect to each other. Analysis of the highest- ranked taxa based on this order revealed 17 taxa having a HACK index of ≥ 75% (figure 1). These taxa all had individual scores of ≥ 70% for the three properties. These included Faecalibacterium prausnitzii, a well-recognised marker of microbiome health [4], followed by Bacteroides uniformis. The list also features several species from the genera Roseburia, Alistipes, and Eubacterium, as well as Coprococcus catus.

The authors then demonstrated the reproducibility of both the individual scores and the overall HACK index by recalculating the association scores within each cohort separately, using different sequencing methods (Shotgun or 16S) and across different type of populations (industrialised urban versus other), followed by an additional validation dataset composed of 14 additional cohorts totalling 5,498 microbiomes.

Beyond their stronger association with health and microbiota stability, some taxa with a high HACK index were also associated with favourable responses to various microbiota-related interventions, such as the Mediterranean diet or anti- cancer immunotherapy.

By analysing genome-level functional annotations from 32,005 genomes representing 122 of the 201 taxa, the authors identified 150 functional features (tags or fragments) specifically enriched and conserved in the genomes of taxa having high HACK indices. These represent a wide range of functions: production of butyrate/propionate with anti-inflammatory properties, synthesis of numerous vitamins, biosynthesis of neuroactive amino acids like tryptophan, and their beneficial anti-inflammatory derivatives such as indoles, or chondroitin sulphates. These are functionalities which warrant exploration to understand underlying mechanisms.

Image

What are the consequences in practice?

The HACK indices were calculated from a global cohort of 45,000 gut microbiomes spanning the six major continents, making this one of the most comprehensive studies to date. These indices represent a step forward in the rational prioritisation of gut microbial species as potential candidates for microbiome based therapeutics. In addition, functionalities associated with high HACK indices may help identify pathways and metabolic capabilities linked to the general health and stability of the microbiome.

Key points
  • Based on 45,454 microbiomes from 141 cohorts (42 countries and 28 disease groups), this study ranked 201 taxa according to their association with three key traits of host and microbiome health: i) prevalence in non-diseased subjects;ii) temporal stability; and iii) negative association with disease
  • Among the 17 bacteria with the highest scores, Faecalibacterium prausnitzii and Bacteroides uniformis ranked first and second, respectively
  • The ranking was reproducible regardless of sequencing method or lifestyle of the cohorts
  • The highest-ranked taxa are associated with positive responses to various microbiota- related therapeutic interventions

Conclusion

Drawing on a very large database, this study identifies a group of 17 taxa that are particularly prevalent (core taxa), stable over time and associated with health. In addition to progressing towards the definition of key components of the human microbiota in terms of both taxonomy and function, this work provides a rational basis for the development of novel therapies based on the gut microbiota or targeting it.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Commented article Off

Microbiotalks: where science meets conversation about microbiota

The Microbiotalks series brings together global experts, researchers, and lay public around one mission: understanding how the microbiota shape health and well-being.
Through inspiring discussions and evidence-based insights, each session opens new perspectives on today’s most pressing health challenges.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Off

Good eating habits to take care of your vaginal flora

We cannot stress it enough: our diet is our first line of defense. This also applies to vaginal microbiota, which is strongly influenced by diet and alcohol consumption. 

The vaginal microbiota

The vaginal microbiota (or vaginal flora) is in some ways the exception that proves the rule: it thrives when not diverse and is largely dominated by lactobacilli. When these bacteria predominate, they repel pathogenic microbes and with them the risk of vaginal infections such as bacterial vaginosis and vulvovaginal candidiasis.

But how can we make sure these beneficial vaginal lactobacilli predominate? Does our diet play a role? A study 1 on 113 Italian students appears to confirm the impact of good and bad eating habits.

Bad habits to avoid

An increase in animal protein intake (mainly from (sidenote: Red meat All mammalian muscle meat such as beef, veal, pork, lamb, mutton, horse, and goat, including that contained in processed foods and in most beefburgers. It does not include poultry or wild game, or offal. However, the definition may vary from country to country: in France, for example, “red meat” refers to beef, lamb, and horse meat, but not to pork or veal, which are considered white meats.

Sources: WHO WHO/IARC CIV (French meat information center)
)
and (sidenote: Processed meat Meat that has been transformed through salting, curing, fermentation, smoking, or other processes to enhance flavor or improve preservation.
Most processed meats contain pork or beef, but processed meats may also contain other red meats, poultry, offal, or meat by-products such as blood.
Examples of processed meat include hot dogs (frankfurters), ham, sausages, corned beef, and biltong or beef jerky as well as canned meat and meat-based preparations and sauces.

Source: WHO
 
)
) goes hand in hand with a vaginal flora imbalance. According to the authors, this kind of diet could increase inflammatory markers or produce toxic compounds that raise vaginal pH, thereby promoting the growth of pathogenic bacteria. 

Meat consumption

  • If you eat red meat, limit consumption to no more than about 3 portions per week. This is equivalent to about 350–500 g (about 12–18oz) cooked weight. 2
  • 500 g of cooked red meat is equivalent to 700–750 g of raw meat. 2
  • Consume very little, if any, processed meat. 2

Alcohol consumption also appears to promote vaginal dysbiosis and boost pathogens such as Gardnerella and Atopobium, confirming the results of a French study which found that heavy drinking adversely affects the intimate flora of young women.

What explains this? Does alcohol have a direct effect on our bacteria, “intoxicating” our beneficial lactobacilli? Or does it alter our immune system, opening the door to the proliferation of unwanted bacteria? 

Binge drinking leaves gut microbiota of young people with a hangover

Learn more

A few good habits to cultivate

The good news is that some dietary habits are beneficial to the vaginal flora.

  • For example, an increased intake of alpha-linolenic acid, an anti-inflammatory (sidenote: Omega-3 A family of essential fatty acids that includes alpha-linolenic acid (ALA), which is both essential in itself (our body cannot produce it, so it must be obtained from food) and a precursor to other omega-3s.
    From ALA, our body can synthesize other omega-3 fatty acids, such as the well-known EPA and DHA.
    However, the body’s rate of conversion of ALA to DHA is too low to meet our DHA requirements. Since DHA is also considered essential, it must also be obtained from food.

    Source: ANSES
     
    )
    found in certain plant-based foods (nuts, rapeseed oil, walnut oil, linseed oil, etc.), appears to reduce the risk of vaginal flora dominated by L. iners (a lactobacillus less protective than others) and promote the beneficial L. crispatus. 
  • Plant proteins (from legumes such as lentils, beans, etc.), fiber, and starch appear to keep the pathogen Gardnerella at bay. The authors believe that these nutrients boost the production of vaginal glycogen, the favorite food of lactobacilli, thus promoting their development. 

Surprisingly, the Mediterranean diet, rich in vegetables, fruit, legumes, and whole grains, does not seem to change vaginal flora composition.
However, there may simply have been too few true followers of this diet among the students to observe any effect.

Even though the Mediterranean diet does not preserve vaginal balance, it is still very good for our cardiovascular health, for warding off certain diseases (ulcerative colitis, endometriosis, etc.) and for helping us to age well (combating frailty in the elderly, slowing Alzheimer’s disease, reducing mortality, etc.)

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Off

When drugs meet microbes: a bidirectional dialogue with therapeutic implications

By Prof. Emmanuel Montassier
Emergency Department, CHU Nantes; Inserm, Center for Research in Transplantation and Translational Immunology, UMR 1064, Nantes Université, Nantes, France

Photo : Microbiota and non-antibiotic drugs interactions: friends or foes?

Bidirectional interactions between oral drugs and the gut microbiome are increasingly seen as crucial to drug efficacy, safety, and tolerability. While antibiotics are known to disrupt microbial communities, about 24% of non-antibiotic drugs also inhibit at least one commensal species. Additionally, 10–15% of oral drugs are transformed by gut microbes in vivo, affecting their effectiveness or toxicity. Common medications such as proton pump inhibitors (PPI), nonsteroidal anti-inflammatory drugs (NSAIDs), metformin, and statins can alter microbiota composition and function, influencing host metabolism and immunity. Despite these findings, the microbiome is often overlooked in prescribing and in drug development. This review summarizes key clinical and mechanistic insights, highlights notable drug–microbiota interaction, and explores emerging strategies to enhance outcomes. Integrating pharmacomicrobiomics into clinical care may reduce adverse effects and support precision medicine.

The gut microbiota acts as a metabolic organ, supporting digestion, immunity, and homeostasis 1. Its interaction with drugs, however, is bidirectional: medications can disrupt microbial balance, while microbes can alter drug activity. This makes the microbiome a significant yet often overlooked factor in adverse drug reaction (ADR) risk 2, 3. Gut microbial enzymes can transform drugs into more toxic forms, increasing tissue exposure and harmful effects. Growing evidence highlights microbial variability as a key driver of individual differences in drug response and ADRs 2, 4. Integrating pharmacomicrobiomics into risk assessment alongside genetics and clinical data could help predict susceptibility to drug-related harm and guide personalized prevention strategies.

Drug-induced microbiota disruption: antibiotics and beyond

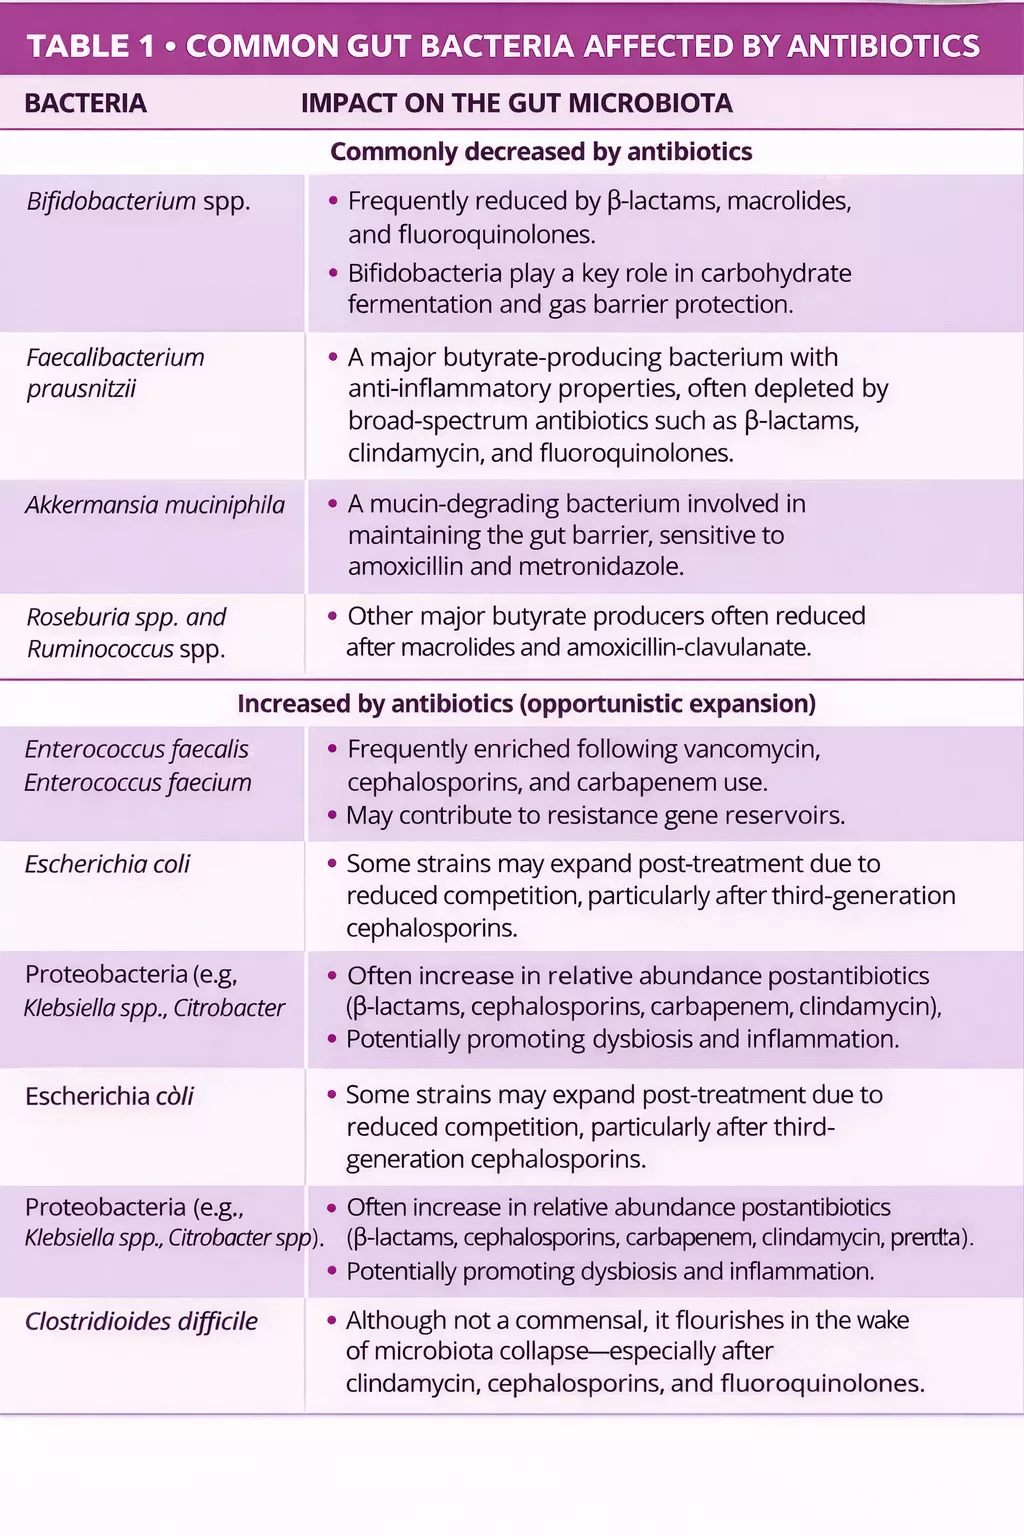
Antibiotics are well known to disrupt the gut microbiota by reducing diversity, altering composition, and promoting resistant strains (table 1) 5, 6. Van Zyl et al. found that antibiotics especially quinolones and β-lactams consistently disrupt microbial communities across body sites, with combination regimens causing prolonged dysbiosis and increased pathogenic burden 5. Similarly, Maier et al. showed that different antibiotic classes have distinct effects on gut bacteria, with macrolides and tetracyclines causing sustained losses in anaerobes, and drugs like amoxicillin and ceftriaxone shifting populations toward Proteobacteria. Despite individual variability, a common trend emerged: depletion of obligate anaerobes (e.g., Firmicutes) and enrichment of facultative and potentially pathogenic microorganisms 6.

Image
Image

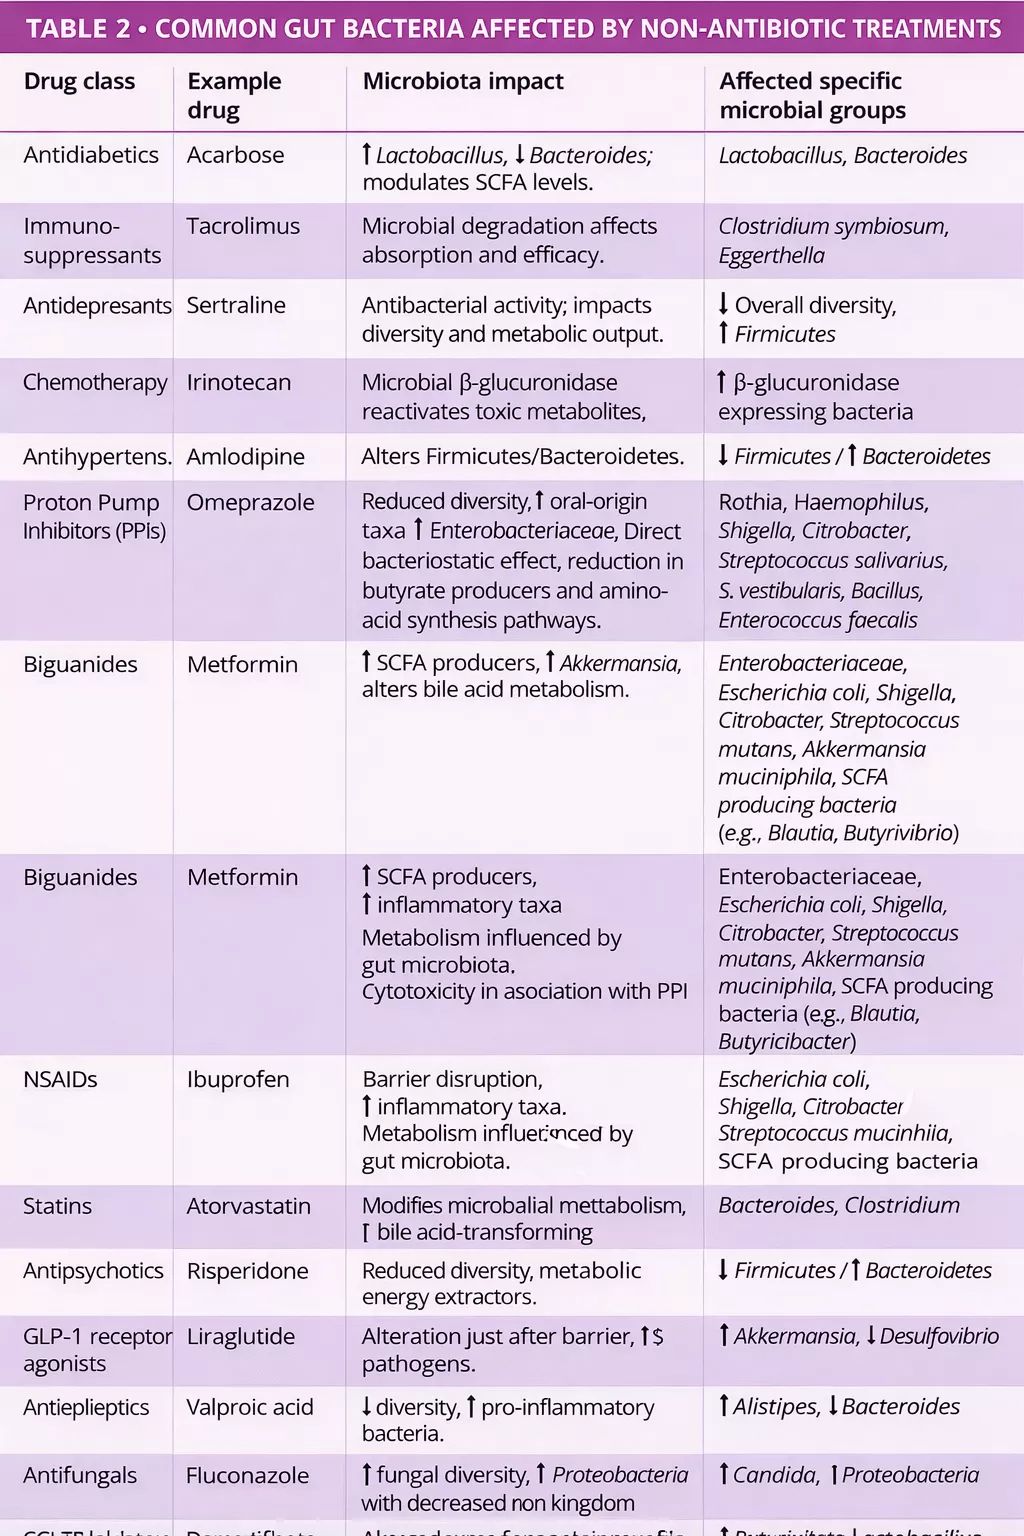
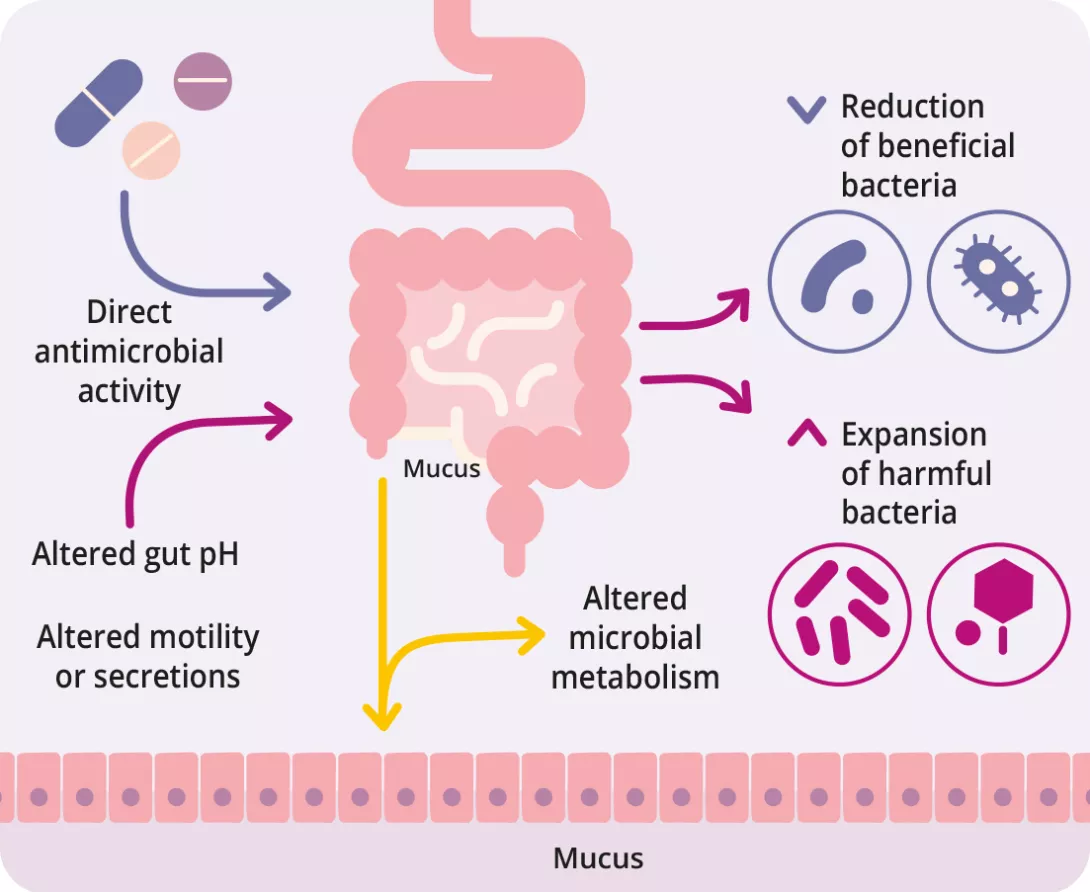
Beyond antibiotics, many non-antibiotic drugs including PPIs, metformin, NSAIDs, antipsychotics, and statins also alter the gut microbiota (figure 1, table 2) 7, 8. Drugs influence the gut microbiota through various mechanisms direct antimicrobial action, altered pH, bile acid modulation, intestinal motility changes, and mucus secretion 9.

Image

Gut microbiota modifies drugs metabolism

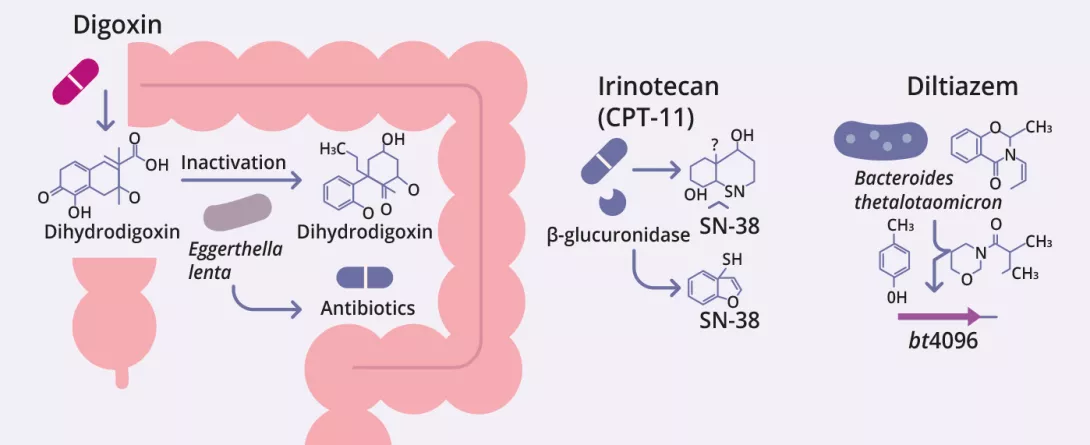
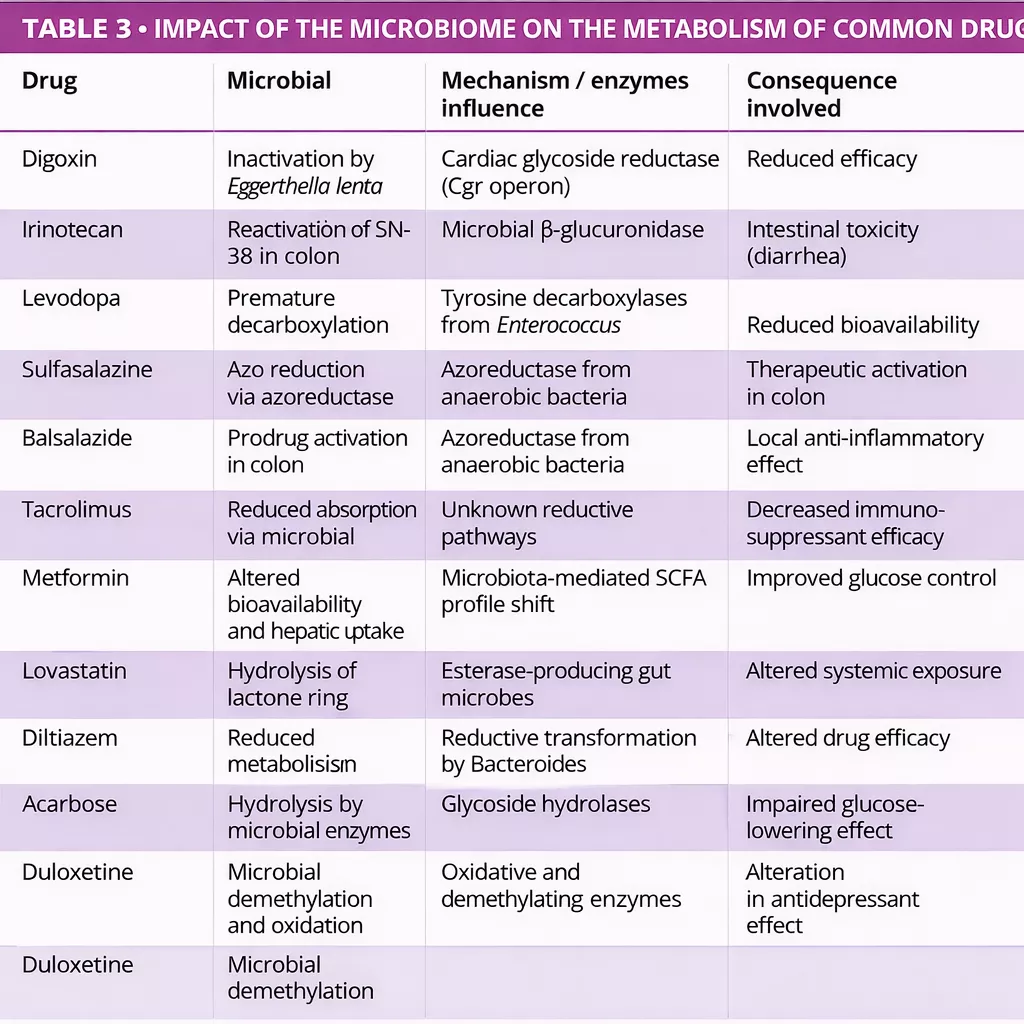
The gut microbiota can biotransform therapeutic drugs, altering their activity, efficacy, and toxicity (figure 2, table 3) 12-14. Zimmermann et al. mapped microbial metabolism by screening 271 oral drugs against 76 gut bacterial strains, finding that 176 were metabolized by at least one strain. Notably, Bacteroides dorei and B. uniformis metabolized nearly 100 drugs. Over 40 microbial enzymes were identified,
mediating a wide range of reactions including reduction, hydrolysis, decarboxylation, dealkylation, and demethylation 12.

Javdan et al. developed a personalized platform (MDM-Screen) to assess microbial drug metabolism using ex vivo microbiota from individual donors. Screening 575 drugs, they found that 13% were metabolized by gut microbes, including many previously unrecognized interactions. These transformations such as hydrolysis, reduction, and deacetylation can activate, inactivate, or increase drug toxicity. The study also revealed significant inter-individual variability and identified key microbial genes (e.g., uridine phosphorylase, β-glucuronidase) linked to specific metabolic pathways 15.

The efficacy of some drugs may depend more on the microbiota composition than on the host genetics.

Image
Image

Clinical consequences: toward personalized medicine

Microbiota-drug interactions have major clinical implications, as individual differences in gut microbiota may explain variability in drug response and side effects. Importantly, it is not just microbiota composition but also its functional stability that influences treatment outcomes.

In advanced melanoma, patients responding well to anti-PD-1 therapy showed stable microbial functions and CD8+ T cells reactive to bacterial peptides from Lachnospiraceae, which mimic tumor antigens highlighting microbial functionality as a potential prognostic marker and therapeutic adjunct in cancer immunotherapy 16.

These insights underscore the need to integrate both human and microbial genomics into pharmacological assessments. In drug development, simulating microbiota–drug interactions in silico has become key. Dodd and Cane proposed a detailed framework combining in vitro systems (e.g., strain libraries, stool-derived communities), genetic tools (gain/loss-offunction assays), and metagenomics to identify microbial genes involved in drug metabolism. Gnotobiotic mouse models further help disentangle microbial from host effects on pharmacokinetics.

As this field advances, microbiota-informed prescribing is emerging as a way to tailor treatments and reduce adverse effects. In the future, pharmacomicrobiomics could guide drug choices and dosages based on microbial biomarkers, enabling truly personalized medicine 17.

Personalizing treatment could one day require a microbiota fingerprint.

Preserving and restoring the microbiota: a therapeutic frontier

Protecting the gut microbiota during drug therapy is a promising strategy to reduce ADRs and preserve efficacy. While probiotics and prebiotics show some benefit against drug-induced dysbiosis, their effectiveness varies. Targeted probiotics tailored to specific drug effects, and fecal microbiota transplantation (FMT), particularly for recurrent C. difficile infection, offer more reliable options.

Precision tools such as microbial enzyme inhibitors (e.g., β-glucuronidase blockers for irinotecan toxicity), bioengineered probiotics,
microbiota-sparing drug designs, and diet-based interventions are under investigation. Clinical trials are exploring synbiotics customized to drug regimens to improve outcomes with minimal microbiota disruption. Postbiotics like butyrate are also being evaluated for anti-inflammatory and gut barrier-supporting effects.

Integrating microbiota-targeted strategies into pharmacology will require advanced tools multi-omics, machine learning, and systems microbiome modeling to predict and manage microbiota–drug interactions effectively.

Manipulating the gut microbiota may enhance treatment success and reduce complications.

Conclusion

Microbiota–drug interactions are an emerging and often overlooked aspect of medicine with major implications for treatment outcomes. Integrating these insights into clinical practice is key to developing safer, more precise, and microbiota-aware therapies. As evidence grows, new opportunities arise to modulate the microbiome to boost efficacy, reduce toxicity, and rescue drug responses.

Innovative approaches such as live biotherapeutics, engineered microbes, and microbiota-derived metabolites (“pharmabiotics”) are reshaping pharmacotherapy. Although regulatory interest is increasing, standardized clinical protocols are still developing. In the near future, microbiome engineering could become a routine component of personalized, systems-based medical care.

Sources:
  1. Valdes AM, Walter J, Segal E, Spector TD. Role of the gut microbiota in nutrition and health. BMJ 2018; 361: k2179.
  2. Zhao Q, Chen Y, Huang W, Zhou H, Zhang W. Drug-microbiota interactions: an emerging priority for precision medicine. Signal Transduct Target Ther 2023; 8: 386.
  3. Wallace BD, Wang H, Lane KT, et al. Alleviating cancer drug toxicity by inhibiting a bacterial enzyme. Science 2010; 330: 831-5.
  4. Bolte LA, Björk JR, Gacesa R, Weersma RK. Pharmacomicrobiomics: The Role of the Gut Microbiome in Immunomodulation and Cancer Therapy. Gastroenterology 2025 Online publication ahead of print.
  5. Nel Van Zyl K, Matukane SR, Hamman BL, Whitelaw AC, Newton-Foot M. Effect of antibiotics on the human microbiome: a systematic review. Int J Antimicrob Agents 2022; 59: 106502. 
  6. Maier L, Goemans CV, Wirbel J, et al. Unravelling the collateral damage of antibiotics on gut bacteria. Nature 2021; 599: 120-4. 
  7. Vich Vila A, Collij V, Sanna S, et al. Impact of commonly used drugs on the composition and metabolic function of the gut microbiota. Nat Commun 2020; 11: 362. 
  8. Macke L, Schulz C, Koletzko L, Malfertheiner P. Systematic review: the effects of proton pump inhibitors on the microbiome of the digestive tract-evidence from next-generation sequencing studies. Aliment Pharmacol Ther 2020; 51: 505-26. 
  9. Le Bastard Q, Berthelot L, Soulillou JP, Montassier E. Impact of non-antibiotic drugs on the human intestinal microbiome. Expert Rev Mol Diagn 2021; 21: 911-24. 
  10. Maier L, Pruteanu M, Kuhn M, et al. Extensive impact of non-antibiotic drugs on human gut bacteria. Nature 2018; 555: 623-8. 
  11. Weersma RK, Zhernakova A, Fu J. Interaction between drugs and the gut microbiome. Gut 2020; 69: 1510-9. 
  12. Zimmermann M, Zimmermann-Kogadeeva M, Wegmann R, Goodman AL. Mapping human microbiome drug metabolism by gut bacteria and their genes. Nature 2019; 570: 462-7. •
  13. Haiser HJ, Gootenberg DB, Chatman K, Sirasani G, Balskus EP, Turnbaugh PJ. Predicting and manipulating cardiac drug inactivation by the human gut bacterium Eggerthella lenta. Science 2013; 341: 295-8. 
  14. Takasuna K, Hagiwara T, Hirohashi M, et al. Involvement of beta-glucuronidase in intestinal microflora in the intestinal toxicity of the antitumor camptothecin derivative irinotecan hydrochloride (CPT-11) in rats. Cancer Res 1996; 56: 3752-7.
  15. Javdan B, Lopez JG, Chankhamjon P, et al. Personalized mapping of drug metabolism by the human gut microbiome. Cell 2020; 181: 1661-79.e22. 
  16. Macandog ADG, Catozzi C, Capone M, et al. Longitudinal analysis of the gut microbiota during anti-PD-1 therapy reveals stable microbial features of response in melanoma patients. Cell Host Microbe 2024; 32: 2004-18.e9. 
  17. Dodd D, Cann I. Tutorial: Microbiome studies in drug metabolism. Clin Transl Sci 2022; 15: 2812-37.
Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Off

Gut microbiota: PFAS purifier?

PFAS, better known as “forever chemicals,” have contaminated our environment and our food. Our gut bacteria may help limit the absorption of these substances by our bodies: they sequester them before escorting them out with our stool and into the toilet. Good riddance!

The gut microbiota

(sidenote: PFAS (per- and polyfluoroalkyl substances) Large group of chemicals, also referred to as ‘forever chemicals’, consisting of a more or less long or branched carbon chain and containing at least one fluorinated group. Their extreme persistence in the environment has been understood for a long time. However, other properties of these compounds that are displayed by certain subgroups of PFAS, are concerning: 

- potential for bioaccumulation in living organisms; 
- high mobility in water, soil and air;
- long-range transport potential; and
- (eco)toxicological effects that impact humans and the environment.


Sources: 
European Environment Agency: PFAS Pollution in European Waters
Gaillard L, Bernal K, Coumoul X et al. Forever pollutants and human contamination: State of art and challenges around per- and polyfluoroalkyl substances (PFASs).Cah Nut & Diet. 2024. Dec (59);6:349-361.
)
, or “forever chemicals,” are widely found in everyday objects (fire-resistant materials in our furniture, non-stick pans, etc.), and today they’re turning up in the environment, in our food... and apparently in the bacteria of our gut microbiota. At least, that’s what a study 1 has demonstrated for the first time in mice that were fed 42 PFAS commonly found in our diet. 

4,700 Per- and polyfluoroalkyl substances (PFAS) include over 4,700 compounds. ¹

€50–80 billion The annual health-related cost of PFAS exposure is estimated to be 50–80 billion Euros across Europe. ¹

More or less bioaccumulating bacteria

Result: several of their gut bacteria massively bioaccumulate certain PFAS. Their surprising favorites: large-sized PFAS.

Among the 89 bacterial strains studied, 38 turned out to be formidable PFAS “vacuum cleaners,” particularly those belonging to the Bacteroidota family. Even at very low doses, PFAS are absorbed in just 3 minutes and accumulate within the bacteria at concentrations up to 50 times higher than in the bacteria’s surrounding environment.

100

The half-life of very long-chain PFAS — the time it takes for half of a substance to degrade or be eliminated — could range from 10 to 100 years, highlighting their extreme persistence in the environment. In a living organism, the half-life varies from a few hours to several years depending on the molecule. 2

No harm done!

As surprising as it may seem, despite their toxicity and their “soapy” effect (PFAS are known and used for their surfactant properties), PFAS appear to have little impact on the functioning of gut bacteria.

They accumulate inside these microorganisms in the form of compact clusters, which, according to the authors, may limit their toxicity. 
Even better, the bacteria seem to adapt: after about a hundred generations, the descendants of Bacteroides uniformis or E. coli grow faster than their predecessors, despite the continued presence of PFAS which they continue to trap efficiently.
Even though the bacteria survive well, some changes are nevertheless observed in their functioning in response to this stress, although, at this stage, it is not yet possible to assess the consequences for the microbiota or the host. 

Microbiota and exposome: a dialog at the core of our health

Learn more

PFAS eliminated through stool

But above all – and this is the study’s major discovery – the bacteria that trap PFAS facilitate their natural elimination. In mice transplanted with human gut microbiota, PFAS were found in greater amounts in their droppings than in mice without microbiota. And the greater the bioaccumulation potential of the bacteria in the digestive system, the more significant this elimination becomes.

Therefore, gut microbiota, especially when rich in bioaccumulating bacteria, may act as a kind of natural extractor of PFAS, trapping these pollutants inside their cytoplasm before carrying them out with the stool. Destination: the sewers!
These results provide new insight into the impact of PFAS on the microbiota, although further studies are needed to better understand the role of these bioaccumulating bacteria in our health.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Off

Let’s not sugarcoat it: sweeteners decrease the effectiveness of immunotherapy

Sucralose is a widely consumed sweetener that alters gut microbiota, indirectly impacting the immune system via T cell metabolism, and with it, responses to immunotherapy.

The gut microbiota is a major regulator of responses to (sidenote: Immune checkpoint inhibitors (ICIs) Therapies that seek to remove the mechanisms that inhibit the immune system’s response to cancer cells. Targeted checkpoints include Programmed Death-1 (PD-1), Programmed Death-Ligand 1 (PDL-1), and cytotoxic T-lymphocyte associated protein 4 (CTLA-4). Lifting these brakes allows the immune system to recognize and attack cancer cells.
 
)
in several cancers, including melanoma and non-small-cell lung cancer (NSCLC). However, the impact of dietary factors such as sweeteners remains poorly understood. For example, sucralose is a widely consumed sweetener known to alter the microbiota. Does it play a role? To answer this question, researchers studied the link between consumption of this sweetener and the effectiveness of anti-PD-1 treatments.

Diminished outlook among sweetener users

The analysis involved three patient cohorts: 91 patients with advanced melanoma, 41 with advanced NSCLC, and 25 with high-risk resectable melanoma, all treated with anti-PD-1 immunotherapy.

High sucralose consumption (> 0.16 mg/kg/day) is associated with poorer clinical outcomes:

  • in advanced melanoma, median progression-free survival (PFS) decreases from 13 to 8 months
  • in NSCLC, it falls from 18 to 7 months, with a lower treatment response rate (12% vs. 49%)
  • in resectable melanoma, treatment response is lower, as is relapse-free survival (19 vs. 25 months).

Similar trends were observed with another sweetener, acesulfame, but not with aspartame or saccharin.

Underlying mechanisms involving T cells

Murine models have confirmed these findings and made it possible to explore the underlying mechanisms. Sucralose consumption leads to resistance to anti-PD-1 immunotherapy and significantly increased tumor growth, whereas sucrose (table sugar) consumption has no effect. The mechanisms appear to involve T cells: sucralose consumption has deleterious effects on several T cell processes (proliferation, cytotoxic function, metabolism). These effects do not appear to be limited to cancer alone, but instead may affect various diseases, from cancer to seasonal viral infections.
 

24-37% Nonnutritive sweeteners (NNS) intake is prevalent in the general population, both in lean and obese individuals alike, with 24% to 37% of US adults reporting some NNS intake in dietary recall surveys.

The gut microbiota, necessary and sufficient

The effect of sucralose depends entirely on the gut microbiota: fecal microbiota transplants (FMT) from mice that consume sucralose are sufficient to reduce the effectiveness of immunotherapy in naive mice. Conversely, an FMT from mice that respond to treatment restores the effectiveness of immunotherapy in mice that consume sucralose.

More specifically, sucralose alters microbiota composition, favoring bacteria that degrade arginine and thus reducing arginine levels in feces, serum, and tumors. Arginine is a key metabolite in T cell metabolism, which explains why T cells become depleted. Remarkably, supplementation with arginine or citrulline (a precursor of arginine) restores T-cell function and overcomes sucralose-induced resistance to immunotherapy in mice.

Thus, certain dietary factors, such as artificial sweeteners, appear to represent a mechanism of resistance to immune checkpoint inhibitors. Confirmation of any causal link will require prospective studies.

Everything you need to know about Microbiota & Immunity

Read the article
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Gastroenterology Immunotherapy Off

Gut bacteria: natural traps for PFAS

Certain bacteria in the gut microbiota bioaccumulate PFAS. They accumulate these pollutants inside their cells at concentrations up to 50 times higher than their environment. An unexpected mechanism that may support their elimination through stool.

PFAS1, also known as “forever chemicals,” have invaded our daily lives: fire-retardant foams in our sofas, waterproof clothing, non-stick pans, and more. Yet interactions between certain PFAS accumulating in the environment and bacteria have already been documented: some strains of Pseudomonas, isolated from sites contaminated with PFAS, bioaccumulate a sulfur-containing PFAS, while certain lactobacilli ‘bio-bind’ with another PFAS. How does the gut microbiota, the key interface between dietary exposure to these substances and our body, come into play? This question is explored in studies released in Nature Microbiology in 2025.
 

Strong and rapid bioaccumulation

By testing 89 microbial strains, researchers found that PFAS bioaccumulation capacity varies greatly from one bacterium to another: 38 strains, including bacteria belonging to the Bacteroidota phylum, showed particularly high bioaccumulation ability, even at low PFAS concentrations. The process proved to be very fast (just a few minutes), irreversible (no release) and highly efficient: the intracellular PFAS concentration in bacteria is about 50 times higher than that of the medium, reaching the millimolar range. The longer the PFAS molecule, the more strongly it is bioaccumulated by the bacterium.

4,700 Per- and polyfluoroalkyl substances (PFAS) include >4,700 compounds.

€50–80 billion The annual health-related cost of PFAS exposure is estimated to be 50–80 billion Euros across Europe.

Little impact on bacterial function

Surprisingly, bioaccumulated PFAS have little effect on bacterial life: their physicochemical properties cause them to aggregate into dense intracellular clusters, limiting their cellular toxicity and effects. Bacteria even appear to adapt over generations: the 100th generation of B. uniformis and E. coli ΔtolC grows faster than their ancestors in the presence of PFAS while maintaining their bioaccumulation capacities.

Although it does not compromise bacterial viability, bioaccumulation nonetheless induces certain changes, particularly in the most accumulative strains: alterations are observed in membrane proteins (particularly efflux pumps responsible for excreting toxins) and in the secretion of amino acids involved in the gut–brain axis or stress response.

Did you know?

The half-life of very long-chain PFAS — the time it takes for half of a substance to degrade or be eliminated — could range from 10 to 100 years, highlighting their extreme persistence in the environment. In a living organism, the half-life varies from a few hours to several years depending on the molecule.2

PFAS excreted in stool

Finally, the presence of bioaccumulating bacteria in the intestine increases the elimination of PFAS: the stool of mice carrying human microbiota is significantly richer in PFAS than that of mice without microbiota. And PFAS excretion is all the more effective when intestinal flora bacteria are strong bioaccumulators. For now, however, the authors are not drawing any conclusions about possible health benefits.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Gastroenterology Off

The nasal microbiota: your baby’s first line of defense

Why does one infant’s cold stay mild while another’s leads to bronchiolitis? A new study reveals the answer isn't just the virus, but the microbial ecosystem in the nose that acts as the immune system’s first line of defense.

The pulmonary microbiota

Every parent knows the cascade of events: a simple cough and runny nose can quickly progress into a full-blown ear infection, or worse, bronchiolitis. We’ve long blamed the virus, but a critical new study in Nature Communications 1 reveals that the virus is often just the opening act. The real drama unfolds within your baby’s (sidenote: ENT Microbiota This refers to the specific community of microorganisms (bacteria, fungi, viruses) that reside in the interconnected regions of the ear, nose, and throat. This ecosystem is distinct from the gut microbiota and plays a crucial, direct role in local immunity and respiratory health. ) , the complex community of bacteria in the nose and throat that serves as the frontline of the immune system. This research provides a new framework for understanding respiratory health during the crucial first year of life.

The viral trigger for bacterial colonization

Researchers followed 300 infants from birth, meticulously tracking their health and analyzing over 2,400 nasal samples. The data reveals a clear mechanism: a viral infection, whether from a common Rhinovirus or Respiratory Syncytial Virus (RSV), profoundly alters the landscape of the respiratory system.

Respiratory syncytial virus (RSV)

Causes 3.6 million hospitalizations each year and approximately 100,000 deaths among children under the age of 5. ²

The presence of a virus was shown to increase the odds of infant (sidenote: Bacterial Colonization This is the persistent presence and growth of bacteria on a host surface, such as the nasal passages, without causing clinical signs of disease. It is a necessary prerequisite for infection but is distinct from it, representing an asymptomatic carrier state. ) with Haemophilus influenzae by 44% and Streptococcus pneumoniae by a striking 83%.

For infants already carrying S. pneumoniae, a viral infection amplified its (sidenote: Colonization Density This is a quantitative measure of the bacterial load, or the number of a specific bacterium present in a sample, rather than a simple presence/absence result. High colonization density can increase the risk of a pathogen transitioning from a harmless colonizer to an active infection. ) nearly four-fold, creating a high-risk environment for invasive disease.

Here is the most significant insight from the study. The virus doesn’t just help harmful bacteria; it actively sabotages the beneficial microbes that keep them in check.

The analysis identified specific protective species, like Corynebacterium, that normally prevent pathogens from gaining a foothold. The data showed that a viral infection leads to a direct loss of these beneficial bacteria. It is this depletion that opens the door for pathogens to colonize.

In a counterintuitive twist, the same viral infections were associated with a 55% lower odds of acquiring Staphylococcus aureus, revealing just how specific and complex these microbial interactions are.

Shaping a resilient immune system for your child

This work emphasizes that a healthy ENT microbiota is not optional; it is a fundamental component of early life immunity.

In fact, the composition of an infant's nasal microbiota was a more accurate predictor of future bacterial acquisition than standard clinical risk factors. The development of this ecosystem is shaped by the (sidenote: Exposome It was in 2005, in an article published in the journal Cancer Epidemiology, Biomarkers & Prevention, that Dr. Christopher Wild first defined the exposome as "life-course environmental exposures (including lifestyle factors), from the prenatal period onwards. It is a complex and dynamic representation that integrates the chemical, microbiological, physical, recreational and medicinal environments, lifestyle, diet and infections."
Source
)
, with factors like breastfeeding playing a key role in seeding and nourishing beneficial species.

Understanding these early microbial dynamics is essential, as they lay the foundation for long-term respiratory health and may influence the future risk of conditions like recurrent infections and asthma.

Microbiota, asthma and antibiotics: it’s all in the nose!

Learn more
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Off