Associations between the gut microbiome and colorectal cancer (CRC) have been uncovered, but larger and more diverse studies are needed to assess their potential clinical use. The authors of this article used 12 metagenomic datasets of patients with CRC (n = 930), adenomas (n = 210) and healthy controls (n = 976; total n = 2,116) and added six new cohorts (n = 1,625) providing granular information on cancer stage and the anatomic location of the tumours. They improved CRC prediction accuracy based solely on gut metagenomics (average area under the curve = 0.85) and highlighted the contribution of 19 new species and distinct Fusobacterium nucleatum clades. Specific gut species distinguish left-sided versus right-sided CRC (area under the curve = 0.66) with an enrichment of oral-typical microbes. The authors identified strain-specific CRC signatures with the commensal species of Ruminococcus bicirculans and Faecalibacterium prausnitzii, showing subclades associated with advanced CRC. The analysis confirmed that the microbiome can be a clinical target for CRC screening and characterised it as a biomarker for CRC progression.
What do we already know about this subject?
CRC is the third most frequent and the second most lethal tumour type worldwide 2. CRC originates in the epithelial layer of the proximal colon (right colon) or distal colon plus rectum (left colon). Progression from benign precancerous lesion (adenoma) to a malignant tumour (carcinoma) may take several years and is characterised by an accumulation of tumour-cell mutations, alteration in the gut mucosal barrier and intestinal inflammation.
The gut microbiome is proposed as one of the important hallmarks of cancer. Certain microbes have been put forward as major contributors to carcinogenesis, particularly Escherichia coli pks+ and Fusobacterium nucleatum3. Several studies have observed distinct microbiome signatures in CRC patients when compared with patients with adenomas or healthy controls 4. A few metagenomic studies also investigated
microbiome changes along the adenoma-carcinoma sequence and based on the primary neoplasia location, and have suggested links between CRC and oral species. Further evidence points toward the enrichment of oral-typical microbes and of oral biofilm-forming species
in the gut metagenomes of patients with proximal CRC. However, no metagenomic studies have gone beyond characterising already well-known strain-specific factors that influence CRC risk, and no untargeted searches for subspecies and strain-level genomic associations with CRC phenotypes are available.
What are the main insights from this study?
Using 3,741 samples from 18 cohorts and applying new strain-level computational methodologies, the authors investigated the links between faecal microbiota and CRC. They improved CRC prediction accuracy based solely on gut metagenomics, with an average area under the curve (AUC) = 0.85. The five SGBs (Species- level Genome Bins) assigned to the species F. nucleatum were more abundant
in CRC than in the controls: F. nucleatum subsp. animalis,vincentii, nucleatum, polymorphum. This was in addition to other well-characterised CRC-associated microbes such as Parvimonas micra and Bacteroides fragilis. The authors also identified 19 additional uncharacterised SGBs with neither cultivated strains nor taxonomically defined species, which highlighted a more complex CRC-associated
microbial signature than previously thought.
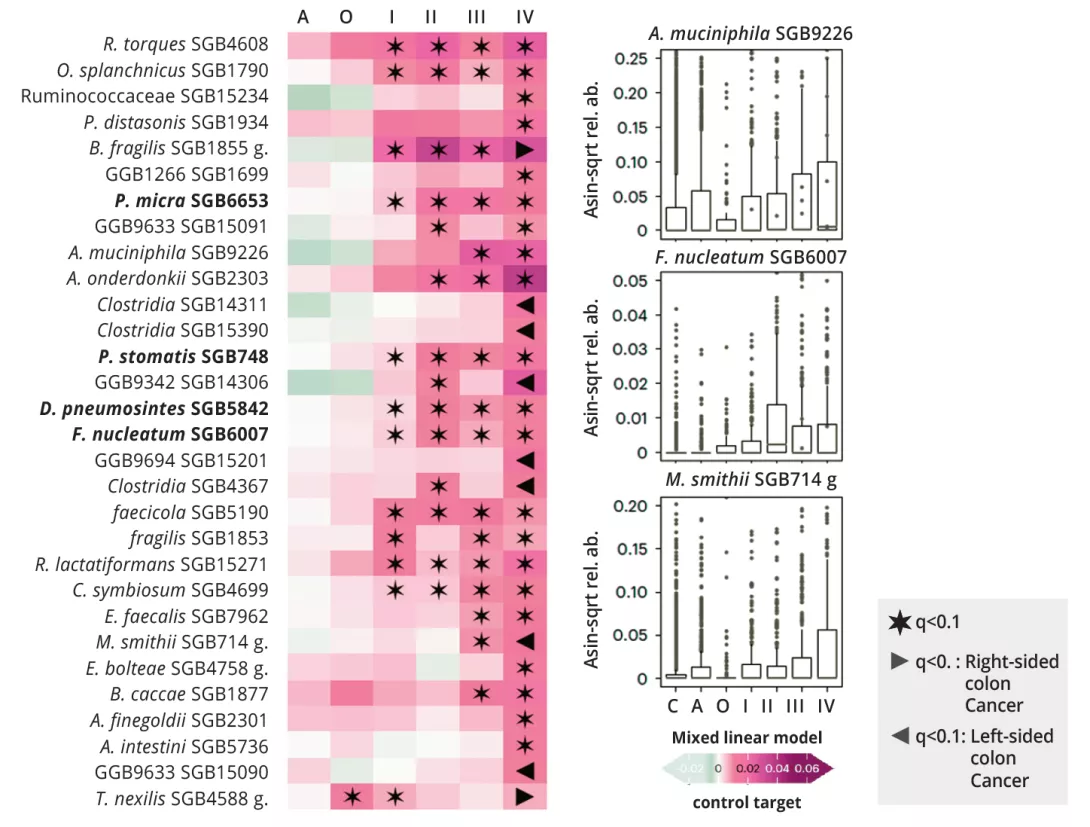
Although interstage microbiome variations during CRC progression are not as strong as those observed between CRC and controls, the authors found several biomarkers for advanced and metastatic CRC, as well as several microbial species consistently and monotonically increasing (or decreasing) from control to cancer or advanced disease. In particular, latestage CRC was enriched in oral-derived species, such as P. micra, already involved in the stimulation of tissue invasion pathways and Hungatella hathewayi, which was shown to promote intestinal cell proliferation in in-vitro experiments (figure 1). Compared with the other stages, metastatic CRC had a higher abundance of Methanobrevibacter smithii, supporting previous findings linking methane producers with stage IV CRC. Stool samples from patients with CRC originating in the right or transverse colon were also enriched in oral species.
These findings strengthen the notion that the number and cumulative abundance of orally derived species are significantly higher in CRC samples than controls and adenomas, but also show that later stages of CRC were particularly enriched in oral species. However, many non-oral bacteria were also associated with CRC, including species previously associated with high cardiometabolic risk. Interestingly, adenoma and later cancer stages were enriched in species linked with poor cardiometabolic health and immune-mediated diseases.
What are the consequences in practice?
This is the largest and most accurate study ever carried out on faecal microbiota associated with CRC. A signature based solely on faecal microbiota offers a relatively good predictive value. In addition, differences between early and late stages have been identified. However, it should be noted that the study did not identify sufficiently accurate markers for the diagnosis of pre-cancerous lesions (adenoma). This work paves the way for microbiota-based tests for diagnosing CRC, but their use in clinical practice still requires validation and, above all, the detection of pre-cancerous lesions needs to be improved.
Figure 1 : Microbial signature according to CRC stage and location of primary tumour.
Image
Key points
Using 3,741 samples from 18 cohorts, the authors investigated the links between faecal microbiota and CRC
A signature based solely on faecal microbiota provides a relatively good predictive value, with an average area under the curve (AUC) = 0.85
However, the study did not identify sufficiently accurate markers for the diagnosis of pre cancerous lesions
Alongside differences between control and CRC subjects, alterations in the microbiota were observed according to the stage and topography of the primary lesion, particularly in terms of the abundance of oral bacteria
CONCLUSION
A signature based solely on faecal microbiota offers prediction with an average area under the curve (AUC) = 0.85. However, the study did not identify sufficiently accurate markers for the diagnosis of pre-cancerous lesions (adenomas). In addition to differences between control and CRC subjects, alterations in the microbiota were observed according to the stage and topography of the primary lesion, particularly in terms of oral bacteria abundance.
By Claire Cardaillac1,2 Martial Caillaud 2 Michel Neunlist 2
1 Department of Gynaecology-Obstetrics and Reproductive Medicine, Nantes University Hospital, Nantes, France 2 University of Nantes, Inserm, TENS, The Enteric Nervous System in Gut and Brain Diseases, IMAD, Nantes, France
Chronic pelvic pain is common, debilitating and particularly affects women. It can be caused by identified lesions, such as endometriosis, or functional syndromes characterised by visceral hypersensitivity, such as irritable bowel syndrome (IBS) or interstitial cystitis. In such cases, peripheral and central sensitisation mechanisms trigger a lowering of pain thresholds and lead to diffuse and difficult-to-treat symptoms.
The gut microbiota plays an increasingly important role in understanding this type of pain. Through its interactions with the immune and nervous systems and metabolism, it exerts a direct effect on the excitability of sensory fibres and pain circuits. Some bacterial metabolites favour neuronal inflammation and hyperexcitability, while others exert a protective effect via anti-inflammatory mediators or endogenous opioids.
In IBS, dysbiosis characterised by a loss of beneficial bacteria (e.g. Faecalibacterium, Roseburia) and increase of opportunistic bacteria has been documented, with experimental evidence of its causal role. In endometriosis, the gut microbiota may contribute to lesion progression and oestrogen modulation, suggesting a bidirectional interaction between the gut microbiota and disease.
These findings are paving the way for new therapeutic avenues including probiotics, prebiotics, postbiotics and even faecal-microbiota
transplantation. Although data remain preliminary, targeting the microbiota appears to offer a promising strategy for improving the management of chronic pelvic pain.
From nociperception to chronic pelvic pain
Pain is defined as an unpleasant sensory and emotional experience, which may or may not be associated with tissue damage. It is referred to as chronic when the pain persists for over three months, resists treatment and leads to changes in functional abilities and social relationships. Chronic visceral pelvic pain is characterised by deep, throbbing and diffuse pain, making its diagnosis complex and imprecise. This type of pain is particularly common in women and may require input from several internal-medicine specialists, i.e. gastroenterology, gynaecology and urology.
Pelvic pain can be caused by several types of organ lesions (e.g. endometriosis) or functional syndromes characterised by visceral hypersensitivity (e.g. irritable bowel syndrome (IBS) or interstitial cystitis). A combination of several painful pelvix condition is often observed in a single patient. Other patients may experience debilitating pain for which no specific cause has been identified. Internal-medicine specialists usually analyse pain as the expression of a single lesion. While it is certainly necessary to treat the injured organ, this may sometimes not be enough to provide relief to patients with chronic pelvic pain. Some patients present with an extensive set of symptoms, combining sensitivity disorders with issues affecting several pelvic organ functions at the same time. Such phenomena are linked to sensitisation mechanisms that appear several months or years after the onset of pain 1. This type of sensitisation is characterised by a lowering of sensitivity thresholds leading to increased pain or pain provoked by stimuli of normally non-nociceptive intensity (e.g. intolerance to the sensation of rectal filling). Pain spreading over time has also been described. In fact, the painful sensation can persist despite the lack
of stimulation (e.g. post-defecation pain). Finally, pain spreading beyond the stimulated area is also observed (e.g. pain during rectal filling causing bladder pain).
On a pathophysiological level, a distinction is made between psychological, adaptive and chronic pain. Acute pain occurs following an initial painful stimulus (heat, pressure, pH variation or algogenic substances) which activates receptors at the endings of the peripheral nociceptive fibres. In the case of the viscera, sensory innervation occurs in the spinal nerves whose endings are located in the muscles and/or mucosa of organs with cell bodies in the dorsal root ganglia 2. Under physiological conditions, activation of Aδ or C afferent fibre receptors generates an action potential (AP) that is translated into nociceptive information in the dorsal root ganglia. This information is then transmitted to the second-order spinal neurons in the dorsal horn. Second-order neurons transmit information to the thalamus via the spinothalamic and spinoreticulothalamic pathways. In the thalamus, the third neuron transmits the message to various areas in the cortex (prefrontal, cingulate,
somatosensory or insular cortex). This third neuron is responsible for transforming nociception into pain, with its affective-emotional, sensitive, cognitive and behavioural dimensions.
In the case of chronic visceral pain observed in conditions such as IBS or chronic inflammatory bowel disease (IBD), particularly
in remission, hypersensitivity of intestinal nociceptive fibres has been documented 3.
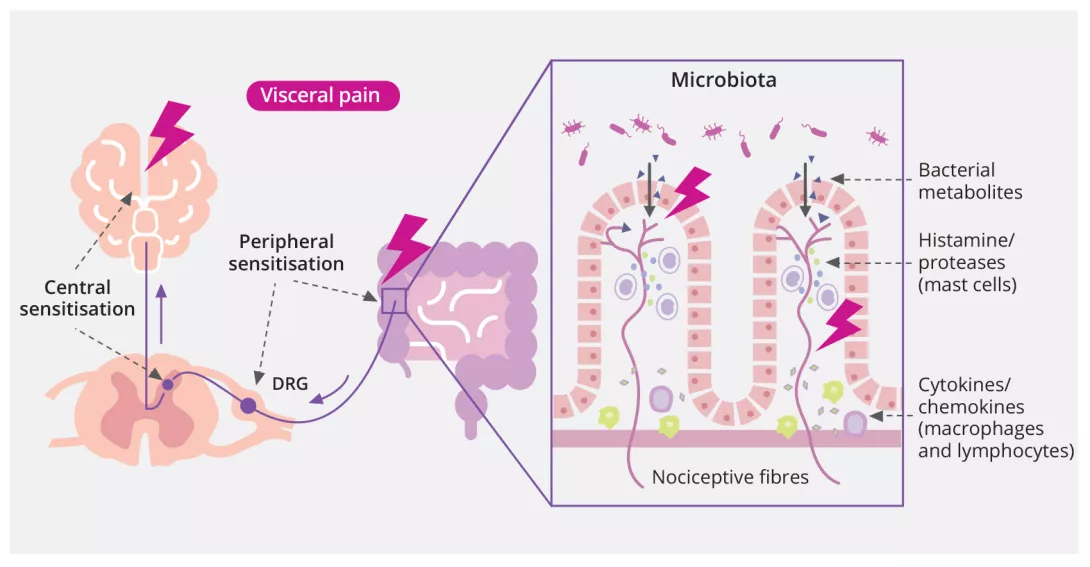
This hypersensitivity may be partly due to gut permeability alterations, thereby increasing the passage of food or bacterial antigens, leading to inflammatory mechanisms with mast-cell recruitment and release of pro-inflammatory mediators such as histamine or proteases. This inflammatory environment could contribute to hyperexcitability in the nociceptive fibres, which in turn contribute to maintaining the inflammatory microenvironment by releasing neuropeptides (Substance P: SP and Calcitonin-Gene Related Peptide: CGRP). These repeated stimuli trigger phenotypic and excitability alterations to the nociceptive neurons in the Dorsal Root Ganglion (DRG), known as peripheral sensitisation. In the spine, repeated APs from DRG neurons increase the release of excitatory neurotransmitters such as glutamate 4. In the long term, this leads to synaptic reinforcement by increasing the number of glutamatergic receptors, combined with dysfunction of the inhibitory systems, resulting in sensitisation of the spinal neurons 4. Thus, central sensitisation is a pathological state of nociception function linked to its dysfunction, with a strengthening of facilitatory systems and lowering of pain-inhibitory systems.
The microbiota, a potential pain modulator
The factors responsible for visceral fibre hypersensitivity are still poorly understood, but the gut microbiota could play a role (figure 1).
Figure 1 : Mechanisms of abdominal pain
Image
The microbiota is defined as all of the microorganisms living in a specific environment in a host. It is mainly composed of bacteria, but also includes viruses, yeasts and protozoa. These micro-organisms may be present without having any impact
on their host (commensalism) or they may interact closely with it.
The number of bacteria colonising the human body (3.8∙1013) is roughly the same as the number of human host cells in adulthood (3.0∙1013) 5. The gut microbiota plays a key role in the two-way communication between the gut and various organs, including the brain. For several years this has been referred to as the microbiota-gut-brain axis. In the past, studies have typically focused on the role of the microbiota in gastrointestinal disorders (irritable bowel syndrome, inflammatory bowel disease). More recently, it has been recognised that dysfunction of this axis is involved in the pathophysiology of many other conditions, including metabolic diseases (obesity, diabetes) and neurological diseases (autism, Parkinson’s disease, depression).
The gut microbiota and the brain communicate with each other using several pathways such as the vagal nervous system, the immune system and the humoral pathways, after modulation of enteroendocrine functions. Nociceptive afferent fibres can also be directly modulated by various bacterial metabolites 6. The main mediators identified are bacterial metabolites (e.g. short-chain fatty acids, secondary bile acids), neurotransmitters and neuromodulators (e.g.: GABA) and bacterial products (e.g.: PAMPs, tryptophan derivatives). Some molecules increase neuronal excitability by activating nociceptors, producing Nerve Growth Factor (NGF) and increasing local inflammation. Others,
however, have the opposite effect (e.g.: GABA) and can inhibit the transmission of the nociceptive message by producing endogenous opioids or anti-inflammatory mediators.
Clinical examples: irritable bowel syndrome and endometriosis
Irritable bowel syndrome
IBS is characterised by chronic functional intestinal disorders, mainly combining abdominal pain and bowel disorders (diarrhoea, constipation or both in alternation). This condition affects around 5-10% of the population, primarily young adult females. The pathophysiology of IBS is not yet fully understood but it has been extensively documented that gut-brain-communication changes lie at the root of digestive motility disorders and visceral hypersensitivity. On a central level, IBS patients experience impaired information processing,
hypervigilance and increased anxiety. In recent years, the gut microbiota has been proposed as one of the causative factors in IBS 7 and several studies have highlighted changes in the composition and diversity of the microbiota in IBS.
For instance, a systematic review showed that the phylum Firmicutes decreased and the phylum Bacteroidetes increased in patients with IBS and diarrhoea 8.
A reduction in the abundance of the genus Bifidobacterium was also found in stool and mucosal samples from IBS patients, along with an increase in the genus Bacteroides. An increase in pathogens (i.e. Escherichia coli and Enterobacterium families) was also observed. An enrichment of certain bacterial taxa such as Enterobacteriaceae, Streptococcus, Fusobacteria, Gemella and Rothia, and a depletion of bacterial genera recognised as beneficial to health, such as Roseburia and Faecalibacterium, were also observed in IBS patients. In IBS, the causal role of these kinds of microbiota changes has been strongly suggested in view of the ability to induce some symptoms in
preclinical models after the transfer of stools from IBS patients 9. In addition, the role of several mediators produced by the intestinal microbiota, such as LPS, short-chain fatty acids and secondary bile acids, has been suggested in chronic abdominal pain, visceral hypersensitivity and gut inflammation 10. The gut microbiota could therefore be a major cofactor in chronic abdominal pain and associated
inflammation.
Endometriosis
Endometriosis is defined as the transplantation of endometrial cells outside the uterine cavity, which may be facilitated by chronic pelvic inflammation. The main symptoms of endometriosis are chronic pelvic pain, gastrointestinal problems and infertility. A systematic review analysed studies of the gut microbiota in women with endometriosis and chronic pelvic pain 11. A total of 28 clinical studies and six animal studies were included in the review. In these human and animal studies, increased gut microbiota diversity was observed in the endometriosis groups. However, there was no clear consensus on the composition of the microbiota associated with endometriosis. None of the studies analysed composition or diversity based on the characteristics of pain.
Animal studies (6/6) confirmed the bidirectional relationship between the gut microbiota and the onset and progression of endometriosis. Endometriosis induction in mice actually induced changes in the gut microbiota.
In the study by Yuan, no early-stage differences were observed after endometriosis induction versus a control group. Differences appeared 21 days after the start of the experiment and increased thereafter, with decreased diversity and richness of the microbiota in the endometriosis group, increased genera Bifidobacterium, Proteobacteria and Verrucomicrobia, decreased Bacteroidetes and Firmicutes phyla and an increase in the Firmicutes/Bacteroidetes ratio, reported 12. Conversely, treatments targeting the microbiota, such as broad-spectrum antibiotics, reduced the volume and weight of endometriosis lesions, induced a decrease in endometrial
lesion cell proliferation and inflammatory markers (cytokines, macrophages) 13. Apart from inflammation, the gut microbiota could contribute to the pathophysiology of endometriosis through its role in regulating oestrogen metabolism. A specific microbiota called the estrobolome actually plays a central role in hormone regulation, especially oestrogen 11. Estrobolome contains bacteria that produce beta-glucuronidase,
which is an enzyme able to modify the active form of oestrogen. Gut microbiota disturbances could therefore lead to increased circulating oestrogen levels and favour the development of endometriosis. However, these studies did not investigate pain modulation.
Therapeutic prospects via the microbiota
The development of therapeutic approaches modulating the composition or function of the gut microbiota are becoming increasingly recognised as playing a complementary role in the current therapies used for the management of chronic functional digestive or pelvic conditions. The basic aim of these approaches is to restore a balanced and functional microbiota (via dietary interventions or prebiotics), or provide bacteria with beneficial effects for the host (probiotics). Specific combinations of probiotics, or specific species and strains 14, appear to have beneficial effects on overall IBS symptoms and abdominal pain [15]. Symbiotic approaches combining pre- and probiotics are also used. Approaches based on the transplantation of faecal microbiota also suggest a therapeutic potential in functional diseases such as IBS 16. In addition, an increasing number of studies are suggesting that the effectiveness of the response to faecal-microbiota transplantation in IBS or to probiotic treatments is influenced by the composition of the microbiota of the recipient.
In the case of endometriosis, two randomised clinical studies have suggested that probiotics were effective in improving pain 17, 18, although one study reported that the efficacy did not last after discontinuing the probiotics.
In general, the effectiveness of these approaches in the management of pelvic functional disorders, although demonstrated in some cases, remains limited by the small population sizes in the studies and, above all, by the wide diversity and variability of symptoms observed in these disorders, as shown in a recent literature review 15.
Endometriosis is linked to disruptions of innate and adaptive immunity, worsened by endometrial dysbiosis, which promotes inflammation and lesion progression. Could this be an avenue for new therapeutic strategies?
In recent years, growing attention has been paid to immune disorders in endometriosis, a condition that affects about 1 in 10 women.
10%
Endometriosis is one of the most prevalent gynecological diseases, affecting up to 10% of women of reproductive age worldwide... ²
190 million
which represents 190 million women, worldwide. ²
These women show several disruptions in innate immunity (rapid, non-specific, without immune memory) and adaptive immunity (antigen-specific). Hence, the relevance of this narrative review, which draws on 198 publications to summarize current knowledge on the immunopathogenesis of endometriosis. 1
The literature confirms that the pathogenesis of endometriosis appears to be driven by disruptions affecting both innate immunity (macrophages, neutrophils, NK cells, complement) and adaptive immunity (T and B lymphocytes). This is true across every stage of development and for all forms of the condition (ovarian, deep infiltrating, extra-genital or adenomyosis).
1st
Endometriosis is the leading cause of subfertility. ²
4 - 12 years
Currently, the average time to diagnosis is between 4 and 12 years. ²
Innate immune cells create an inflammatory microenvironment that supports the survival of ectopic endometrial cells, while dysfunction in adaptive immunity (reduced cytotoxic T-cell activity, Treg-mediated immune tolerance) allows these cells to escape elimination once implanted.
Together, these two mechanisms promote the implantation of endometriotic lesions, their growth, angiogenesis and progressive tissue damage, maintaining a self-perpetuating inflammatory cycle.
Endometriosis encompasses 2 distinct forms:
external endometriosis, characterized by ectopic lesions outside the uterus;
internal endometriosis (adenomyosis), in which endometrial tissue penetrates into the myometrium.
What is the role of the endometrial microbiota?
In women with endometriosis, dysbiosis of the endometrial microbiota is observed: an increase in pathogenic bacteria such as Escherichiacoli, Shigella and Streptococcus, and a decrease in protective Lactobacillus species.
This dysbiosis is associated with activation of the complement system, which may enhance local inflammation and promote the attachment of endometrial cells to the peritoneal mesothelium.
Due to chronic inflammation, macrophages that should be in “destruction” mode (M1 phenotype) shift to an anti-inflammatory and healing mode (M2 type). Instead of eliminating displaced endometrial cells, they “calm” the immune response, support tissue repair and promote lesion survival.
Beyond advancing knowledge, understanding the mechanisms of endometriosis immunopathogenesis paves the way for targeted immunotherapy. Goal: directly modulate dysfunctional immune components.
Among the strategies under study are immunomodulators, cytokine/chemokine inhibitors, gene therapy, nanotechnology, immune checkpoint targeting (PD-1/PD-L1, CTLA-4) and therapies guided by macrophages and NK cells. Probiotics may also play an important role, as oral administration of Lactobacillus gasseri activates NK cells and reduces lesion size in a mouse model.
If you’re not sleeping well, your gut bacteria might be to blame. Your gut microbiota, the billions of microorganisms living in your gut, is in constant communication with your brain, and this conversation directly affects the quality of your sleep. 1
night shifts and jet lag are often associated with increased intestinal permeability and inflammation;
and imbalances in the gut microbiota are observed in several disorders frequently linked to poor sleep (depression, Parkinson’s, Alzheimer’s); etc.
Three communication pathways
How do gut bacteria communicate with the brain? Gut bacteria produce compounds such as:
serotonin (the “happiness hormone”),
melatonin (the “sleep hormone”),
and GABA (a calming neurotransmitter),
which enter the bloodstream and travel to the brain.
But that’s not all: gut bacteria also act on the vagus nerve—a direct connection between the gut and the brain—and influence the brain regions associated with sleep. A stressed microbiota means a frazzled brain and a sleepless night ahead.
The third communication pathway is inflammation. Poor sleep triggers an inflammatory reaction in the gut, which weakens its lining and, in turn, affects the nervous system, including the brain.
Thus, the gut-brain axis enables two-way communication, creating the risk of a vicious circle that can take a toll on your nights.
1 in 10
Insomnia affects 1 in 10 adults. ²
2 in 10
adults experience occasional symptoms of insomnia. ²
Anti-insomnia bacteria?
How can you return to restful sleep? Since traditional sleeping pills come with a list of side effects as long as a sleepless night, researchers are looking to the microbiota for novel treatments.
Prebiotics and (sidenote:
симбиотические
Тесная и взаимовыгодная связь между двумя или более организмами
) (prebiotics + probiotics) can improve perceived sleep quality and extend deep sleep phases.
In severe cases, (sidenote:
Fecal Microbiota Transplantation (FMT)
A therapeutic procedure to restore the gut microbiota by transferring fecal bacteria from a healthy donor to a recipient.
Explorehttps://www.science.org/doi/10.1126/scitranslmed.abo2750) offers promising remission rates, particularly in patients with long COVID.
Thus, personalized sleep medicine may one day pass through your gut.
In the meantime, eating well, especially fiber-rich foods, means nourishing your gut microbiota and increasing the odds you’ll get a good night’s sleep. Ultimately, it may be true that those who eat well, sleep well.
At nursery, babies meet their first peers... and their peers’ gut bacteria, which they’ll actively exchange. This plays just as big a role in the development of their gut flora as the microbiota inherited from their own family.
Worried your baby might catch a virus at nursery? You’re not entirely wrong—but the surprising reality is far more upbeat. It’s true that nursery is a true hub for the exchange of microbes among infants. But far from being bad news, it’s actually a boon for their health.
A major Italian scientific study 1, microTOUCH-baby, has recently confirmed this. For a year, researchers followed 43 infants in three public nurseries in Trento, as well as their parents, siblings, pets, and nursery staff—134 subjects in total. They analyzed the composition of each subject’s gut microbiota at regular intervals.
The results? Infants start nursery with a gut microbiota partly inherited from their mother and father and enriched by any siblings. Very quickly, babies begin to share their gut bacteria.
After one year, microorganisms received from nursery peers account for a larger portion of their gut flora than those transmitted by their own parents. Over the months, the transmission network becomes increasingly complex: certain bacterial strains spread from parent to baby, then to the baby’s playmate, then to the playmate’s parents... like an invisible game of pass-the-parcel.
Babies who have siblings at home have a more diverse microbiota and are less likely to acquire new strains on arriving at nursery, since the space is already taken.
Infants who receive antibiotics see their flora temporarily collapse and then rapidly replenish itself with bacteria from their peers, as if their microbiota, depleted by the treatment, were trying to rebuild itself quickly, much faster than what is observed in adults.
Other findings will reassure moms: the influence on a child’s gut microbiota of the mode of delivery (vaginal or cesarean) or the possible administration of antibiotics shortly before birth appears to have disappeared by 10 months, the median age of entry into nursery in this study.
A catalyst for microbial exchange
In short, social interactions in early childhood actively contribute to the development of the gut microbiota, which plays a key role in long-term health. So the next time your baby comes home from nursery with a runny nose, remember that they also have some fantastic new residents in their gut!
Microbiota transmission between infants during their first year in nursery is intense, suggesting social interactions during early childhood are key drivers of gut microbiota development in infants.
An infant’s microbiota develops gradually after birth. The mother is the primary source of microorganisms, but she is far from being alone.
To assess the role of early social interactions, particularly in nursery, researchers launched a longitudinal metagenomic study 1, microTOUCH-baby, in three public nursery centers in Trento, Italy. The study involved 43 infants, 7 of their siblings, 39 mothers and 30 fathers, 5 pets living in the home, and 10 nursery staff members.
When they entered nursery (median age 10 months), the infants’ microbiota was heavily influenced by that of their mother and father, but still differed significantly from that of adults. The presence of siblings at home was also a source of enrichment. In contrast, the influence of birth practices (mode of delivery, peripartum antibiotics) on microbial diversity was no longer statistically significant at this age.
As early as the first month of nursery, microbiota transmission between babies began. Eight strains spread very efficiently: initially detected in no more than one infant, after a few months, they were present in more than half of the group.
After three months in nursery, a convergence was observed in the infants’ gut microbiota: diversity between children decreased (-7% during the first quarter), and the proportion of strains acquired from nursery peers (28.4%) ultimately surpassed those acquired from family (20.0%).
In total, the study identified more than 565,000 instances of strain sharing over 15 months, with complex chains of transmission. Pets also shared strains with infants, but to a more limited extent.
Unsurprisingly, antibiotic treatment was the factor that most influenced transmission: it reduced the retention of existing strains but was followed by a massive influx of new strains, more pronounced in the infants than in the adults. Exposure in nursery could contribute to this rapid recovery of microbial diversity after treatment.
Infants with siblings acquire significantly fewer strains at nursery than only children. Early acquisition via siblings could “saturate” the potential for acquiring new strains.
In the study, certain species, such as the beneficial Bifidobacterium longum subsp. infantis, typically found in breastfed children, was present only in the infants. Other highly transmissible species included fiber-degrading bacteria, which suggests these social transmissions may promote healthy microbiota development.
Thus, social interactions such as those in nursery appear to be essential to microbiota development, acting, according to the authors, as a “microbial enrichment hub” beyond the family circle.
Your breast milk is not just food, it is a living ecosystem. Every feed delivers bacteria straight into your baby’s gut. New science now shows exactly which ones arrive, take hold, and shape your child’s health from the inside out.
You already know breast milk is remarkable. But scientists have just revealed something that goes deeper than nutrition: your milk is alive with bacteria, and those bacteria travel directly into your baby’s gut, take up residence, and begin shaping their health within the first weeks of life.
A major new study 1 in Nature Communications, following 195 mother-baby pairs across six months, used technology powerful enough to tell individual bacterial “fingerprints” apart, and traced them, one by one, from milk to baby.
Among all the bacteria scientists found, one stood out: Bifidobacteriumlongum. It was present in the guts of 98 out of every 100 babies at one month of age.
But what makes it remarkable is not just how common it is, it’s what it does. Babies whose guts were dominated by this species, especially a subspecies called B. longum subsp. infantis, had a gut microbiome that held remarkably steady over the following months.
It settled, rather than swinging. Why? Because this bacterium has evolved a special ability to break down the natural sugars in breast milk, sugars that exist, it now seems, precisely to feed it.
The longer mothers breastfed exclusively, the more this species flourished. Babies who stopped earlier showed less stable communities taking hold. What you feed your baby shapes who moves in, and who stays.
Disclaimer
At the Biocodex Microbiota Institute, we recognize that breastfeeding, including prolonged breastfeeding, is not always possible or suitable for every mother and family. This article is intended to share the latest scientific findings on the subject, while respecting the diversity of feeding journeys and individual circumstances.
From your milk to their gut: a direct line of inheritance
Here is where the research becomes genuinely astonishing. Using a technique that can tell apart bacterial “twins”, strains so similar they look identical to standard tests, scientists found something never confirmed before with this precision: the exact same strain detected in a mother’s breast milk was also found, weeks later, living in her baby’s gut. Not just a similar species. The same genetic identity. Your bacteria know your baby’s address, and they deliver themselves there.
They also discovered something unexpected about direction. Some shared bacteria were species normally found in the mouth, suggesting that when your baby feeds at the breast, microbes from their mouth travel back into the milk. Breastfeeding is not a one-way delivery. It is a conversation between two microbiomes, flowing in both directions with every feed.
Birth mode leaves its mark here too. Babies born vaginally retained their gut bacteria for significantly longer, their microbial community at six months looked more like it had at one month.
Babies born by C-section showed a more fluid picture, with fewer strains persisting. Neither is a verdict. But how a baby enters the world shapes the microbiome they carry through it.
Every baby in the study, including the two-thirds who had never received a single antibiotic, carried genes linked to antibiotic resistance. This sounds alarming. It isn’t. These genes, known collectively as the resistome, are a normal, ancient feature of the human gut, far older than antibiotics themselves. What scientists set out to understand was simply: where does a newborn’s resistome come from?
Resistome
The collection of antibiotic resistance genes living in a microbiome. Ancient and normal, these genes existed long before antibiotics were developed. Babies carry them from birth. What this study shows is that breastfeeding helps keep them in check.
The answer, in significant part, is breast milk. Mothers and their babies shared far more resistance genes with each other than unrelated pairs did, clear evidence that feeding is a transmission route. But here is what matters most: babies whose guts were dominated by Bifidobacterium, exactly the bacteria that breast milk cultivates, carried substantially fewer resistance genes than those with other microbial communities.
Breastfeeding doesn’t just build a thriving microbiome. It actively displaces a less desirable one. Every feed is, in the most literal biological sense, an act of protection.
Breastfeeding is universally recommended. But which live bacteria does milk actually transmit, and can they reshape the infant gut resistome? Strain-level metagenomics now answer both, with direct implications for perinatal counselling.
Breastfeeding guidance has long rested on binary choices: breast vs. formula. A landmark study in Nature Communications by Ferretti, Allert et al. dissolves that simplicity entirely 1.
Using (sidenote:
Shotgun Metagenomics
This is a high-resolution sequencing method that analyzes all the genetic material from every microbe in a sample. Unlike older techniques that just identify bacterial families, it allows for precise identification down to the species level and reveals the functional genes those bacteria possess.
) on 507 samples from 195 mother–infant pairs, the team tracked bacteria not just at species level but at strain level; the genetic resolution required to prove transmission, not merely infer it. What they found reframes breastfeeding as an active, strain-specific microbial intervention with measurable consequences for the infant (sidenote:
Resistome
The complete set of antimicrobial resistance genes (ARGs) harbored by a microbiome. In this study, the infant gut resistome was significantly shaped by maternal breast milk, even in antibiotic-naive infants.
).
Bifidobacterium longum was present in 98.2% of infant stool samples at one month, but prevalence alone understates its role. Infants whose guts were dominated by B. longum, and particularly by its subspecies B. longum subsp. infantis, maintained significantly more stable microbiome composition between one and six months than those dominated by other species.
The mechanism is specific: B. longum subsp. infantis carries the enzymatic machinery to degrade human milk oligosaccharides (HMOs), giving it a decisive competitive advantage in the breastfed gut.
Its mean relative abundance surged from 3.2% at one month to 23.8% at six months. Infants with non-bifidobacteria-dominated guts showed the most volatility.
The clinical read: breastfeeding duration is not just a nutritional variable; it is a determinant of microbiome architecture.
Twelve confirmed transmissions, and what they reveal about the gut–milk axis
Twelve instances of strain-level sharing between maternal milk and infant gut; same species, identical genetic fingerprint; demonstrate that breast milk is a bona fide transmission route.
Shared taxa spanned commensals (B. longum, B. bifidum), gut-associated species (Phocaeicola vulgatus), and typical oral residents such as Streptococcus salivarius and Rothia mucilaginosa, the latter two suggesting retrograde colonisation from the infant’s oral cavity back into the milk during suckling, a biologically plausible bidirectional axis.
Most notable was the detection of Klebsiella pneumoniae as a confirmed shared strain. No infants showed clinical manifestations, consistent with silent commensal carriage; nonetheless, this finding signals that culture-independent, strain-level milk surveillance may add meaningful risk stratification in high-risk neonatal settings beyond what standard culture screens can offer.
Delivery mode compounds this picture: 19.4% of infant gut strains at one month persisted to six months, and vaginally born infants retained significantly more of them than those born by C-section (p = 0.018), evidence that birth mode shapes not just early colonisation, but the durability of the microbial community across the first half-year of life.
The resistome is inherited and breastfeeding can modulate it
Every infant carried antibiotic resistance genes (ARGs) at one month, including the 67% who had no recorded pre-, peri-, or postnatal antibiotic exposure. Resistance classes for tetracycline, MLS (macrolide-lincosamide-streptogramin), aminoglycoside, and beta-lactams were all present. This is not a signal of clinical failure; it is the baseline ecology of the human neonatal gut, assembled through mechanisms independent of antibiotic selective pressure and largely invisible to standard clinical workups.
What this study adds is the transmission axis and, critically, a modifiable countermeasure. Mother–infant pairs shared significantly more ARGs than permuted pseudo-pairs (p < 0.016).The dominant shared genes were MACB (MLS class), ACRD (aminoglycoside), and TETQ (tetracycline). Sharing was highest in the two pairs with confirmed strain transmission events, providing a mechanistically coherent explanation. Yet infants with bifidobacteria-dominated guts carried markedly fewer ARGs than those dominated by other species (p = 7.6×10⁻¹⁰).
The implication for practice is direct: supporting Bifidobacterium colonisation through exclusive breastfeeding and, where indicated, B. longum subsp. infantis-containing probiotics does not only enrich the microbiome, it also suppresses the resistome.
Clinicians now have strain-level, resistome-level evidence that the how and how long of breastfeeding counselling carries consequences that extend well beyond nutrition.
The gut microbiota may play an important role in the onset and progression of vitiligo. Hippuric acid, a metabolite produced by the microbiota, may be a key mediator of oxidative stress… and a potential biomarker or even a therapeutic target?
Vitiligo, an autoimmune skin disease, is characterized by the destruction of melanocytes, leading to depigmented patches. However, cutaneous oxidative stress—a key factor in the progression of the disease—appears to be influenced by the gut microbiota. Here’s a breakdown of a study that examines the mechanisms at work.1
Oxidative stress linked to the gut microbiota
The first step in the researchers’ work involved analyzing lesions in patients and in a mouse model. This revealed, in the depigmented areas, an overexpression of genes associated with oxidative stress and responses to reactive oxygen species (ROS). This confirms that these processes are crucial in the pathogenesis of the disease.
Next step: the researchers discovered that mice with vitiligo exhibit a significant accumulation of ROS in the skin, as well as mitochondrial abnormalities in their melanocytes. Eliminating the gut microbiota with antibiotics reduced the abnormal accumulation of ROS and the mitochondrial abnormalities in the melanocytes, resulting in a significant improvement in depigmentation. Thus, the gut microbiota appears to directly regulate the skin’s oxidative stress status.
Vitiligo around the world
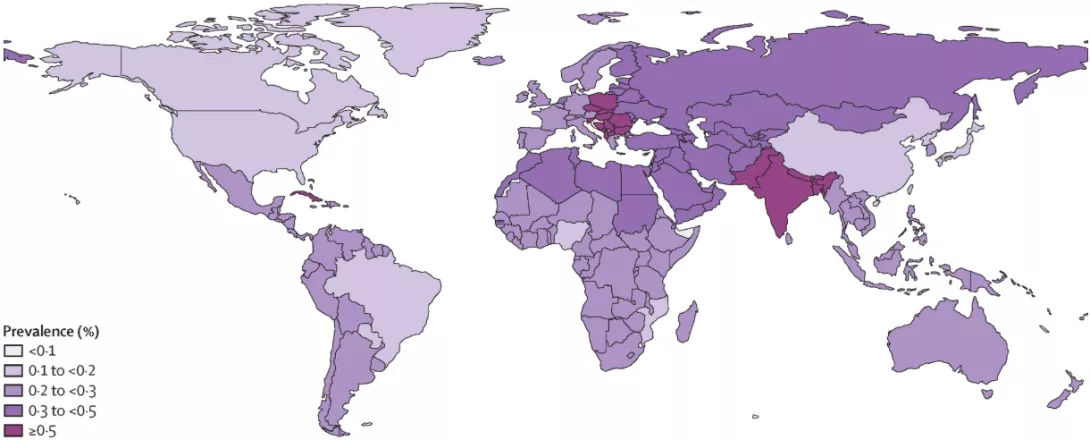
The global lifetime prevalence of vitiligo diagnosed by a physician or dermatologist is estimated at 0.36% in the general population, 0.67% in the adult population, and 0.24% in the pediatric population.2
Among adults, prevalence estimates range from 0.43% in East Asia to 0.98% in Central Europe.2
Among children, the prevalence of vitiligo ranges from 0.16% in East Asia to 0.35% in South Asia and 0.35% in Central Europe.2
Image
From the gut microbiota to the skin
Subsequent research by scientists shows that the microbiota of mice with vitiligo is imbalanced (increased Clostridiales, decreased Verrucomicrobiae). Transferring this dysbiotic microbiota (through cohabitation of animals or fecal transplantation) exacerbates depigmentation. Conversely, administering probiotics slows the progression of the disease, suggesting a potential therapeutic approach.
But how is the gut microbiota linked to the skin? Metabolomic analysis of fecal, blood, and skin tissues from mice identified a key factor: hippuric acid, a metabolite derived from the microbiota, accumulates excessively in the feces, serum, and skin of mice with vitiligo. Injections of hippuric acid are sufficient to reproduce the accumulation of ROS and exacerbate depigmentation in mice. And in humans? Serum levels of hippuric acid are found to be higher in patients with vitiligo.
A mechanistic hypothesis
This leads to the following hypothesis: in mice with vitiligo, the intestinal mucosal barrier is weakened (due to a reduction in goblet cells responsible for mucus production and a decrease in mucosal thickness), which increases intestinal permeability. This increased permeability would facilitate the passage of hippuric acid into the bloodstream and then to the skin. Hippuric acid would induce oxidative stress by directly binding to two proteins (NOS2 and MAPK14); this direct molecular interaction would then promote the production of ROS in skin tissues.
Thus, intestinal dysbiosis would orchestrate cutaneous oxidative stress in vitiligo via hippuric acid. These results also suggest that probiotics may play a role in slowing the progression of the disease.
The gut microbiota and sleep interact with each other in both directions through metabolic, neural, and immune pathways. Does this open the door to new therapeutic strategies for sleep disorders?
What if there is a bidirectional relationship between sleep and the gut? To go beyond simple correlational studies1, this review delves into the literature on the microbiota-gut-brain axis and its role in sleep regulation to summarize the potential mechanisms linking the composition and function of the gut microbiota to sleep disorders.
18%
The estimated prevalence of obstructive sleep apnea (OSA) in the adult population is 18%.
10%
The estimated prevalence of insomnia in the adult population is 10%.
3%
The estimated prevalence of restless legs syndrome (RLS) in the adult population is 3%.
Sleep Disorders and the Gut-Brain Axis
Different sleep disorders are associated with changes in the composition of the gut microbiota and its metabolites:
- Insomniacs show reduced microbial diversity, with (though results vary by study) a decrease in the abundance of certain bacteria (such as Ruminococcaceae) correlating with a decrease in their metabolites (fewer secondary bile acids, produced by bacteria from liver bile acids).
- There is also less diversity in patients suffering from obstructive sleep apnea, and (sidenote:
Fecal Microbiota Transplantation (FMT)
A therapeutic procedure to restore the gut microbiota by transferring fecal bacteria from a healthy donor to a recipient.
Explorehttps://www.science.org/doi/10.1126/scitranslmed.abo2750) from individuals suffering from hypoxia can disrupt the sleep cycles of healthy animals.
- Night work and jet lag also cause significant changes in the microbiota, increasing intestinal permeability and inflammation.
- Narcolepsy may be associated with an imbalance between immunosuppressive and immunostimulatory microorganisms.
- In the case of restless leg syndrome, the multiplication of bacteria in the small intestine may play a role.
Dysbiosis is also observed in sleep-related disorders: in major depressive disorders, the composition of the gut microbiota is associated with sleep quality; in Parkinson’s disease, (sidenote:
Mendelian randomization
An approach that exploits natural genetic variation to test causal relationships between a biological factor (e.g., cholesterol, vitamin D, BMI) and a disease (e.g., heart attack). Researchers use genetic variants associated with the biological factor of interest (e.g., patients with alleles that increase LDL cholesterol vs. patients without) to test whether there is a causal relationship between the biological factor (LDL cholesterol) and the disease (heart attack). The random distribution of alleles in the population reduces biases (confounding factors, etc.), mimicking some of the advantages of a randomized trial.
) studies suggest a causal link with gut bacteria; in Alzheimer’s disease, sleep disturbances are directly related to the accumulation of beta-amyloid protein, in parallel with changes in the bacterial flora that could be potential diagnostic and even therapeutic biomarkers.
0,03%
The estimated prevalence of narcolepsy in the adult population is 0.03%.
>50%
More than one in 2 people with dementia (including Alzheimer’s disease) suffer from insomnia.²
Two-way communication
The review also highlights three main bidirectional communication pathways through which the gut-brain-microbiota axis coordinates sleep:
- Metabolic and endocrine pathways: secondary bile acids and (sidenote:
Short chain fatty acids (SCFA)
Short chain fatty acids (SCFA) are a source of energy (fuel) for an individual’s cells. They interact with the immune system and are involved in communication between the intestine and the brain.
Silva YP, Bernardi A, Frozza RL. The Role of Short-Chain Fatty Acids From Gut Microbiota in Gut-Brain Communication. Front Endocrinol (Lausanne). 2020;11:25.) produced by bacteria affect sleep through systemic circulation. In addition, the microbiota produces or regulates key molecules of the wake-sleep cycle, such as GABA, serotonin, tryptophan and melatonin.
- Neural pathways: gut bacteria and their metabolites interact with the gut nervous system and cooperate with vagal nerve pathways, influencing brain areas and circuits related to sleep. In addition, the microbiota and its metabolites modulate the stress response and the corticosterone rhythm, influencing wakefulness-related hyperactivity.
- Immune pathways: Sleep deprivation triggers systemic and gut inflammation, weakening the gut barrier and affecting the central nervous system.
In high-income European countries, obstructive sleep apnea (OSA) is the most costly sleep disorder (€184 billion), followed by insomnia (€158 billion), restless legs syndrome (RLS) (€79 billion), narcolepsy (€905 million) and REM sleep behavior disorder (RBD) (€436 million). Direct and indirect costs account for 48% and 52% of the total, respectively, with no data available on informal care costs.3
Sleep disorders are very common in people with Parkinson’s disease, with up to 98% of patients experiencing them at some point. REM sleep behavior disorder (RBD) is seen in about 46% of patients with Parkinson’s disease.
Restless legs syndrome (RLS) affects 15-20% of patients with Parkinson’s disease, although early-onset RLS does not predispose to the later development of Parkinson’s disease. However, severe RLS may be an early warning sign of the disease.
Modifying the Microbiome to Improve Sleep
Since traditional methods of treating sleep disorders often involve side effects, microbiome-targeted therapies represent promising strategies:
FMT offers promising remission rates for insomnia, especially in patients suffering from long-term COVID or fibromyalgia.
Is science heading towards precision medicine in the field of sleep?
Is science heading towards precision medicine in the field of sleep?