Press review #1: Gut microbiota

By Dr Nguyễn Bá Mỹ Nhi
Director of OBGYN Center, Tam Anh Hospital, Ho Chi Minh City, Vietnam

Gut microbiota composition in women with polycystic ovary syndrome

The gut microbiota is increasingly viewed as an invisible organ-like system that not only plays an important role in a woman’s wellbeing but also affects the pathophysiology of some disorders such as polycystic ovarian syndrome (PCOS). Knowing about microbial metabolite pathways may elucidate effective treatments.

A recent meta-analysis that included 948 women with PCOS from 14 studies explored the relationships between gut microbiota among women from different regions and with different testosterone levels. Key findings revealed distinct gut microbiota compositions in PCOS patients compared with their healthy counterparts, and significantly different gut microbiota between PCOS patients with higher testosterone levels and those with lower testosterone levels. Also, gut bacterial genera differed among PCOS patients from different regions; European patients had high Alistipes levels, whereas Chinese patients had high Blautia and Roseburia levels.

These findings support current evidence showing that PCOS patients have fewer different types of bacteria and a less balanced microbial community compared with healthy women. The data also confirm the abundance in PCOS patients of specific bacterial genera such as Escherichia/Shigella and Alistipes, which are associated with insulin resistance and inflammation. This study implies that the gut microbiome is linked to various metabolic and hormonal disturbances associated with PCOS, which is compatible with previous research. Importantly, it demonstrates differences in bacterial taxa between Chinese and European women with PCOS, which may assist with personalised treatment strategies. Further research to determine PCOS-associated bacteria strains may enhance anti-PCOS microbial therapies and studies in different geographical regions would promote the global treatment of PCOS.

To conclude, characterising gut microbiota in PCOS patients from different countries may enable gut microbiota to act as a biomarker to distinguish different subtypes of PCOS, and thereby improve the clinical diagnosis and treatment of PCOS.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Press review Off

Press review #1: Vaginal Microbiota

By Dr Nguyễn Bá Mỹ Nhi
Director of OBGYN Center, Tam Anh Hospital, Ho Chi Minh City, Vietnam

The role of the vaginal microbiota in women’s health

The human body hosts trillions of microorganisms, collectively known as the microbiome, residing in various locations and coexisting in a complex symbiotic partnership. Importantly, the vaginal microbiota influences women’s reproductive and overall health. Understanding this ecosystem could revolutionise the prevention and treatment of these conditions.

This review highlights the links between dysbiosis of the vaginal microbiota and gynaecological disorders, as well as pregnancy-related complications. Specifically, reductions in lactobacilli and an increased vaginal microbiota diversity are associated with human papillomavirus (HPV) infection, the formation of cervical lesions, and cervical cancer. A loss of vaginal Lactobacillus dominance can create a proinflammatory environment that compromises successful embryonic implantation, leading to infertility. An imbalance in the vaginal microbiome can trigger inflammation leading to pregnancy complications. Having fewer Lactobacillus species in the vaginal microbiome increases the risks of premature rupture of membranes, preterm birth, miscarriage, and ectopic pregnancy. Vaginal dysbiosis may contribute to insulin resistance, a hallmark of gestational diabetes mellitus, and greater diversity in bacterial composition has been found in severe preeclampsia. Testing for Prevotella bivia colonisation during pregnancy may help to predict and mitigate against hypertensive disorders during pregnancy.

This review underscores the key relevance of the vaginal microbiome in women’s reproductive and overall health. The composition of this microbiome can impact everything from fertility and pregnancy outcomes to infection susceptibility. The article covers various aspects of vaginal microbiota, including its relationship with immune system function, inflammation, and pathogen defence, and thereby offers a broad, holistic understanding of its role with generalisable insights into women’s health at large. Enhanced knowledge around how the vaginal microbiome influences health presents an important advance for early disease detection and prevention, instead of treating infections or conditions after they appear. However, long-term study data are needed to clarify the long-term effects of vaginal microbiome imbalances. Moreover, while probiotics and other microbiomebased interventions show promise for maintaining a healthy vaginal microbiome, probiotic strains, dosages, and delivery mechanisms have yet to be standardised for clinical application. Much work remains to be done.

In sum, having fewer vaginal Lactobacillus species and increased vaginal microbial diversity is associated with obstetric and gynaecological complications. This review highlights the possibility of using microbiome-based diagnostics to detect imbalances in vaginal flora, potentially before symptoms manifest. Early intervention may prevent adverse consequences.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Press review Off

The male genital microbiota impact on women’s health

By Prof Jean-Marc Bohbot
Director, The Fournier Institute, Paris, France

Tout ce que vous avez toujours voulu savoir sur le microbiote du sexe des hommes (sans jamais oser le demander)

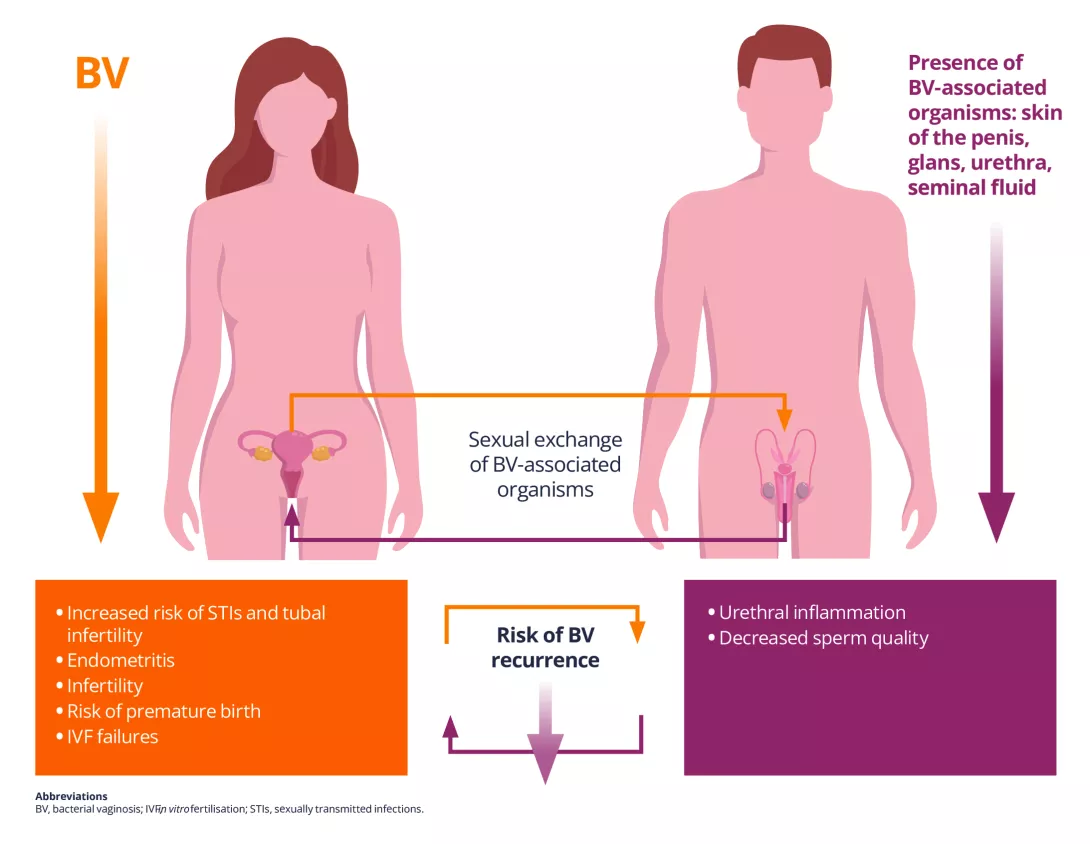
Talk about vaginal infections, fertility, or pregnancy complications often focuses solely on women. But there is another important player: the male urogenital tact (MUGT). The wide variety of microbes in the MUGT can significantly affect female reproductive and vaginal health (Figure 1). Understanding these influences may improve outcomes for women, especially those with persistent vaginal infections, fertility challenges, and pregnancy complications.

Figure 1. Consequences of exchanges of bacteria associated with vaginosis during sexual contact between males and female

Image

What do we know about the male genital microbiota?

The MUGT includes several distinct microbial environments: the skin of the penis, the urethra, semen, and the urinary tract. Each has a unique bacterial community, influenced by factors like circumcision, sexual practices, hygiene, and lifestyle.

Penile skin and foreskin

The skin of the penis harbours bacteria similar to those found on other cutaneous (skin) surfaces — mainly Corynebacterium and Staphylococcus genera1, 2. In uncircumcised men, the area under the foreskin (the balanopreputial sulcus) is dominated by anaerobic bacteria such as Anaerococcus, Peptoniphilus, Finegoldia, and Prevotella, some of which are also found in women with bacterial vaginosis (BV)1, 2. Circumcision significantly reduces these anaerobes, which may explain why women with circumcised partners have a lower risk of BV2.

Urethra

Sampling the urethra directly is painful, so most studies use the first-void urine as a proxy to study urethral microbiota. This fluid contains a mix of bacteria like Lactobacillus, Streptococcus, Sneathia, Veillonella, Corynebacteria, and Prevotella3. Interestingly, some of these are linked to BV (e.g. Gardnerella vaginalis) and aerobic vaginitis (S. agalactiae)4.

Semen

Semen is not just sperm — it also includes fluids from the prostate and seminal glands. Studies show that a Lactobacillus-dominated seminal microbiota is linked to better sperm quality, while other bacteria (e.g. Ureaplasma, Mycoplasma, Prevotella, and Klebsiella pneumoniae) are associated with lower fertility5.

Urine

The male urinary microbiota is less studied, but lower levels of Streptococcus, Lactobacillus, Pseudomonas, and Enterococcus genera have been found in men with abnormal sperm concentration compared with men with normal sperm concentration6. Men with abnormal sperm motility may have high levels of Dialister micraerophilus bacteria, which contribute to a proinflammatory sperm microenvironment6.

MUGT microbiota vary with circumcision status, sexual practices, and the composition of the female partner’s vaginal microbiota7.
Interestingly, the urethral microbiota of homosexual men does not seem to be modified by the type of sexual intercourse (oral or anal)8. Bacterial exchanges between partners during sexual contact are the rule; why these exchanges lead to vaginal dysbiosis in some cases and not others is unclear.

Seminal microbiota are also influenced by several physiological functions (age, hormonal changes) and lifestyle or epigenetic factors
(tobacco, alcohol, obesity, high-fat diet, exposure to toxins)5. These modifiable factors are potential targets for intervention.

How does the MUGT impact female health?

The transmission of microorganisms responsible for bacterial and viral sexually transmitted infections (STIs) including HIV and herpes simplex virus infection during sexual contact is the most obvious consequence of how the MUGT impacts female health. The female complications of bacterial STIs (gonorrhoea, infections by Chlamydia trachomatis or M. genitalium) are well known (inflammation and infection of the upper genital tract, risk of tubal infertility).

Many studies have shown that the epidemiological profile of women with BV is comparable to that of women with STIs, suggesting possible sexual transmission of the bacteria involved in BV. The presence of BV-associated bacteria in the foreskin and urethra of partners of women with BV and a concordance of vaginal and male urethral bacterial strains support the sharing of these strains or sexual transmission of BV.

Treating the male partner with oral antibiotics (metronidazole) has had very limited impact on recurrence rates in women with recurrent
BV, although combining metronidazole with a topical antibiotic applied to penile skin in partners of women with BV may reduce the risk of recurrence9.

The impact of the MUGT on uterovaginal health is not limited to passive bacterial transfer. Seminal fluid contains proinflammatory substances (such as prostaglandins) that can interfere with immune responses and inflammation within the female genital tract10.

KEY POINTS

  • The male genital microbiota plays an influential but underrecognised role in female reproductive health, particularly in recurrent genital infections and fertility challenges.
  • Routine STI screening may miss important bacteria that are not traditionally classified as pathogens but disrupt the female genital microbiota.
  • Male-partner treatment for recurrent BV may need to go beyond oral antibiotics, incorporating topical therapies and addressing shared risk factors.

CONCLUSION

The male urogenital microbiota matters — not just for men’s health, but for women’s too. While research is still evolving, it is clear that male partner dynamics, lifestyle, and microbial exchange influence female urogenital health. The evidence increasingly supports a more holistic, couple-based approach to managing reproductive concerns, by incorporating male partner care into routine sexual and reproductive health strategies to improve outcomes for both partners, especially in cases of persistent or recurrent vaginal infections. Encouraging healthier habits in men — including quitting smoking or improving the diet — might improve semen microbial health and reduce the risk of negative outcomes for their female partners.

Sources
1. Gonçalves MFM, Fernandes AR, Rodrigues AG, et al. Microbiome in male genital mucosa (prepuce, glans, and coronal sulcus): a systematic review. Microorganisms 2022; 10: 2312.
2. Onywera H, Williamson AL, Ponomarenko J, et al. The penile microbiota in uncircumcised and circumcised men: relationships with HIV and human papillomavirus infections and cervicovaginal microbiota. Front Med (Lausanne) 2020; 7: 383.
3. Zuber A, Peric A, Pluchino N, et al. Human male genital tract microbiota. Int J Mol Sci 2023; 24: 6939.
4. Toh E, Xing Y, Gao X, et al. Sexual behavior shapes male genitourinary microbiome composition. Cell Rep Med 2023; 4: 100981.
5. Chatzokou D, Tsarna E, Davouti E, et al. Semen microbiome, male infertility, and reproductive health. Int J Mol Sci 2025; 26: 1446.
6. Osadchiy V, Belarmino A, Kianian R, et al. Urine microbes and predictive metagenomic profiles associate with abnormalities in sperm parameters: implications for male subfertility. F S Sci 2024; 5: 163-73.
7. Mehta SD, Nandi D, Agingu W, et al. Longitudinal changes in the composition of the penile microbiome are associated with circumcision status, HIV and HSV-2 status, sexual practices, and female partner microbiome composition. Front Cell Infect Microbiol 2022; 12: 916437.
8. Chambers LC, Tapia KA, Srinivasan S, et al. The relationship between insertive oral and anal sex and select measures of the composition of the urethral microbiota among men who have sex with men. Sex Transm Dis 2024; 51: 407-14.
9. Vodstrcil LA, Plummer EL, Fairley CK, et al. Male-partner treatment to prevent recurrence of bacterial vaginosis. N Engl J Med 2025; 392: 947-57.
10. Adefuye AO, Adeola HA, Sales KJ, et al. Seminal fluid-mediated inflammation in physiology and pathology of the female reproductive tract. J Immunol Res 2016; 2016: 9
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Gynecology General Medicine Off

The Foundation for Endometriosis Research: a catalyst for research on endometriosis in France

The Biocodex Microbiota Institute partners with a variety of professional organizations, including medical societies, patient associations, and research foundations involved in women’s health. In this issue, we look at the work done by the Foundation for Endometriosis Research and talk to their experts who discuss the importance of the female microbiota in research and clinical practice.

Founded in France in 2021 by the ENDOmind Association under the aegis of the Foundation for Medical Research, the Foundation for Endometriosis Research aims to accelerate research on a disease that affects one in 10 women: endometriosis. Each year, the Foundation funds research projects aimed at understanding the pathology of endometriosis, improving diagnosis and developing more effective treatments.

In 2024, the Foundation for Endometriosis Research Executive Committee decided to more clearly define its research priorities for endometriosis and maximise its research impact. To this aim, the Foundation coconstructed and co-funded an innovative collaboration with the Curie Institute in Paris, seeking to compare the cellular microenvironments of endometriosis lesions and ovarian cancer. This ambitious project is starting in 2025 and illustrates the Foundation’s desire to encourage cross-disciplinary and innovative research
approaches.

Furthermore, the Foundation for Endometriosis Research has initiated a multidisciplinary scientific investigation with European experts on the links between microbiota and endometriosis. The Foundation will call for expressions of interest later in 2025, with the objective of launching new research work at the start of 2026, with financial support.

By focusing its efforts on strategic themes, the Foundation for Endometriosis Research confirms its role in accelerating research and ultimately contributing to improving the quality of life for the millions of women affected by this still little-known disease.

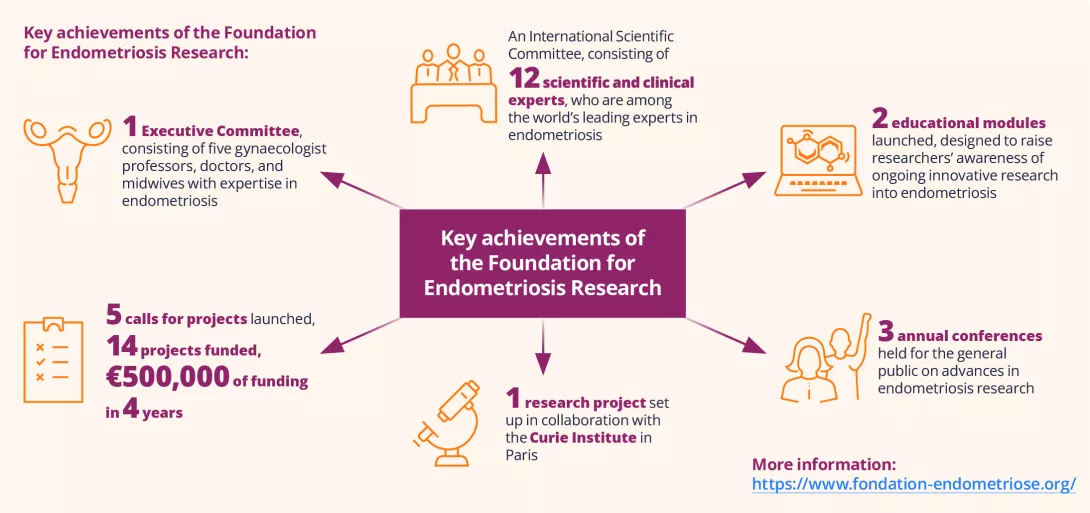
Key achievements of the Foundation for Endometriosis Research:

Image
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article General Medicine Gynecology Off

Endometriosis, Digestive Symptoms, and the Microbiome: Perspectives of a Gynaecologist and a Gastroenterologist

Prof Andrew Horne
Professor of Gynaecology and Director of the Centre for Reproductive Health at the University of Edinburgh in the UK, with specialisation in the management of endometriosis.

Dr William Fusco
Gastroenterologist and microbiome clinical researcher at the Agostino Gemelli Polyclinic, Rome, Italy.

What is the prevalence of endometriosis?

A.H.: Endometriosis is surprisingly common – as common as asthma and diabetes. It affects an estimated 1 in 10 women.

W.F.: In my practice of irritable bowel syndrome (IBS), it’s even more common – certainly more than 25%.

What are the signs and questions to ask to avoid missing a diagnosis?

A.H.: Signs are varied and diagnosis can be difficult. The main symptom is chronic pelvic pain, which can often be debilitating, disrupting life and work. But, patients can also present with painful sex, chronic fatigue, diarrhoea and/or constipation and urinary symptoms. Any cyclical symptom can be a red flag for endometriosis.

W.F.: Increased peristalsis and softer stools during menstruation are normal, but significant and cyclical diarrhoea may not be so. Pain is expected, but not to the point of being bedridden.

A.H.: Another symptom that causes alarm is infertility. But I reassure patients with endometriosis: two-thirds of them won’t have trouble getting pregnant, and those who do generally respond well to surgery or IVF.

W.F.: I would add that endometriosis is chronic, but that doesn’t mean it’s untreatable. It’s important that any specialist involved with the care of these patients reinforces that message.

How common are digestive symptoms in women with endometriosis?

A.H.: The true prevalence isn’t known, but nearly all my patients have digestive symptoms – bloating, bowel changes, heartburn. Lesions on the bowel wall explain some symptoms, but many have superficial peritoneal disease, making the link harder to define.

W.F.: I have observed similarly, and would state that inflammatory bowel disease (IBD) is four times more common in women with endometriosis compared with the general population (4% vs 1%). IBD and endometriosis are both autoimmune conditions; having one increases the risk of the other.

Is there a need for multidisciplinary management?

A.H.: Endometriosis is a systemic inflammatory disorder. As gynaecologists, we’re not equipped to manage digestive symptoms. In Edinburgh, I’ve recently set up a joint gynaecology–gastroenterology clinic.

W.F.: When the abdominal pain strictly relates to menstruation, the gastroenterologist may find it difficult to add much. When the relationship is more loosely defined, we should investigate. Persistent digestive symptoms despite treatment may signal coexisting IBS. Also, be mindful of medications, particularly nonsteroidal anti-inflammatory drugs (NSAIDs). Occasional use is fine in young patients, but chronic use may require a proton pump inhibitor (PPI), which can cause dysbiosis. There’s no universal rule — we must tailor care to each patient.

Are gut and vaginal microbiota involved?

A.H.: There’s growing interest in the role of the gut and vaginal microbiomes in endometriosis. Some studies suggest associations, but they’re small and flawed. We need large cohort studies. I believe the microbiome plays a role, but it’s still unclear as to which comes first — microbiome changes or endometriosis. If microbiota drive symptoms, this could open the path to new treatments.

W.F.: It’s an exciting field. In patients with endometriosis, we observe gut dysbiosis with reduced short-chain fatty acids like acetate, propionate and butyrate that protect gut permeability. The same pattern can be seen in other gastroenterological conditions, like IBS or IBD, but we don’t yet understand the relationship. Maybe one day, we’ll personalise care by restoring exact missing strains. For now, we don’t know what causes what, so mechanistic studies are needed.

Should we recommend specific diets to patients with endometriosis?

W.F.: There’s no universal diet for endometriosis and we shouldn’t offer false hope. Allergies, lactose intolerance, and coeliac disease might be involved. The best step is to refer patients to a nutritionist.

A.H.: No specific “endometriosis diet” exists, but many patients report symptom relief after dietary changes. In my clinic, patients work with a dietitian to carefully adjust their diets. In our international survey of 2,500 patients with endometriosis, some found relief by stopping consumption of alcohol and caffeine, or foods containing gluten. However, without guidance, dietary restriction can be harmful.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Off

Women’s vulvovaginal microbiota: how can it help in clinical practice?

By Dr Pedro Vieira Baptista
Hospital Lusíadas Porto, Porto, Portugal; Department of Gynecology-Obstetrics and Pediatrics, Faculdade de Medicina da Universidade do Porto; Faculty of Medicine and Health Sciences, Ghent University, Ghent, Belgium

Photo: Endométriose : une clé de sa progression au sein du microbiote intestinal

The world of the human vaginal microbiome is a fascinating one, despite the limited knowledge about it. Evolution led to a unique scenario in which dominance by specific species of lactobacilli is the optimal state during reproductive years, despite huge interindividual variations – and even in the same woman over time. Understanding the vaginal microbiome and its potential is the key to improving women’s health in areas such as sexually transmitted infections and recurrent vaginitis. Also, of utmost importance, it may be the answer to a problem to which there have been no satisfactory answers until now: preterm labour. In this article, we discuss the vaginal microbiome through an evolutionary lens, highlighting the apparent lack of a continuum between species. We discuss the current knowledge but also focus on future possibilities.

Historical perspective

The beginning of the long journey towards the understanding of the vaginal microbiome can be attributed to Albert Döderlein, at the end of the 19th century. In his book Das Scheidensekret und seine Bedeutung für das Puerperalfieberhe pointed out that “normal”, healthy women have the vagina dominated by Grampositive bacilli, which he named Lactobacillus acidophilus.

Key points
  • The study of the vaginal microbiome is still evolving despite huge progress over the last decades.
  • The optimal human vaginal microbiome in reproductive-aged women is dominated by lactobacilli.
  • Non-dominance of the human vaginal microbiome by lactobacilli is associated with an increased risk of sexually transmitted infections, cervical cancer, and negative obstetrical outcomes.
  • Future tests may allow a more accurate diagnosis of vaginitis and evaluation of the risk associated with specific dysbiotic profiles.
  • While microbiome research is advancing rapidly, it is crucial to distinguish between investigational tests and their clinically relevant applications

This concept still shapes contemporary interpretations of the vaginal microbiome, but the reality is probably far more complex.

Understanding of vaginitis is still incomplete, and its management mostly empirical, despite being one of the most common causes for  women to seek a medical appointment1.

In 2011, Ravel et al. published one of the most important and mind-changing papers in terms of understanding of the human vaginal  microbiome. In that paper they demonstrated that asymptomatic is not synonymous with “normal” (leading also to the question of what 
is a “normal” – or, probably more accurate, “optimal” – vaginal microbiome) and that there are striking differences according to ethnicity2.

Diversity is the rule in nature, but the human vagina seems to be an exception: the accepted “optimal” vaginal microbiome is dominated by one or two species of lactobacilli (low alpha diversity). If we think about other organs or anatomical regions, dominance by one species 
is usually synonymous with disease (infection). If we perform the same exercise considering any ecological system, it represents the last 
step before collapse (e.g. monocultures of plants never occur in nature, and when performed artificially they must be limited in time). We can look for further explanations for this apparent “abnormality” (or “exception”) in nature, but it does seem to lead to a dead end. 

Should we, instead, change the focus of our lens and investigate gene pools rather than species or genera to overcome this apparent 
biological abnormality

The ultimate goal of living beings seems to be passing genes to the next generations and evolution seems to be much driven by this 
primordial “instinct”. Therefore, we can easily assume that the human vaginal microbiome should be a fulcral part of the end-product 
of evolution to optimise the reproductive process. If this premise is correct, we can expect

  1. evolutionary congruence (as has been shown, for instance, in the gut);
  2. any differences should be more or less easily explained (mating process, diet, geographical location, etc.) and, naturally
  3. higher similarity in closely related species.

Surprisingly, none of the three premises are satisfied. In nature, phylogeny cannot be related with the vaginal pH (a very indirect marker of the vaginal microbiome composition), and dominance by lactobacilli is unique to the human species. Even when comparing humans with other primates, the differences are huge and, currently, not easily explainable3,4. What made the human vagina so unique? Was it the fruit of random events or the evolutionary corollary of the continuous ovarian cycle, high risk of lacerations and infection at birth, or agriculture and the consequent high consumption of starch3?

The microbiome and pregnancy

One issue seems to be beyond doubt: lactobacilli are fundamental for the success of pregnancy – but it is not so clear if the same 
applies to achieving a pregnancy5.

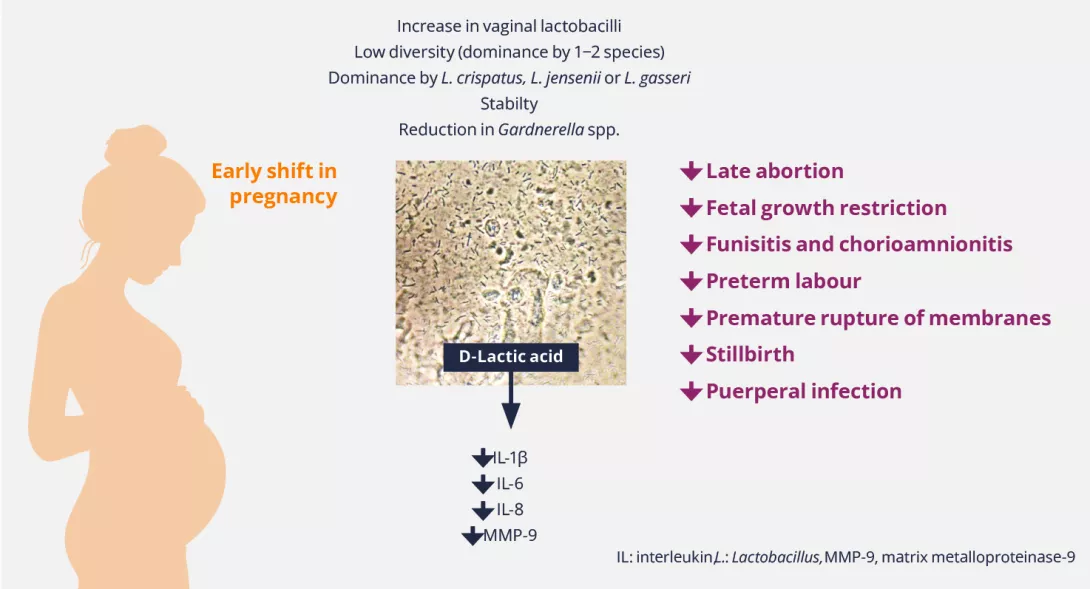
The available data clearly show that a vagina not dominated by lactobacilli during pregnancy is associated with negative obstetrical and puerperal outcomes, including preterm labour, premature rupture of membranes, and puerperal infections (Figure 1). Of note, one million babies die every year from prematurity-related complications6.

We are used to repeating that lactobacilli have a protective role and that their presence is desirable, but to assume that means we must ignore some obvious facts, such as that this dominance does not occur in children, during breastfeeding, nor in postmenopausal women. Therefore, we can theorise that our symbiotic relation with lactobacilli serves us a purpose during the reproductive years. We can consider that this purpose includes a reduction in the risk of sexually transmitted infection (STIs) (which pose a risk to the success of reproduction and to the offspring), of ascending genital infections (and consequent abortion, stillbirth, and preterm birth), as well as of puerperal complications. The role of the microbiome in achieving pregnancy seems to be more limited. For instance, populations with high rates of vaginal dysbiosis do not seem to be less fertile7

Figure 1. Vaginal lactobacilli dominance is associated with beneficial obstetrical and puerperal outcomes

Image

In the same way, the impact of the cervicovaginal microbiome on the outcome of fertility treatments is also unclear5.

One of the biggest evolutionary differences between humans and other mammals has to do with delivery – the difficult balance between being born with a large cephalic perimeter and negotiating it with a pelvis that had to adapt to bipedalism. Humans have the most difficult deliveries – perhaps surpassed only by hyenas. Can this hold the key to understanding the uniqueness of the human vaginal microbiome? Whatever the evolutionary purpose was, for most women of reproductive age, even out of pregnancy, the dominance of lactobacilli in the vagina is the desirable state. But lacking lactobacilli, despite representing a dysbiotic state, is not synonymous with disease.

Our understanding of the role of the vaginal microbiota is still very limited. Even apparently simple questions, such as how lactobacilli
colonise the vagina still does not have a clear answer.

The vulvovaginal microbiome in heath and disease

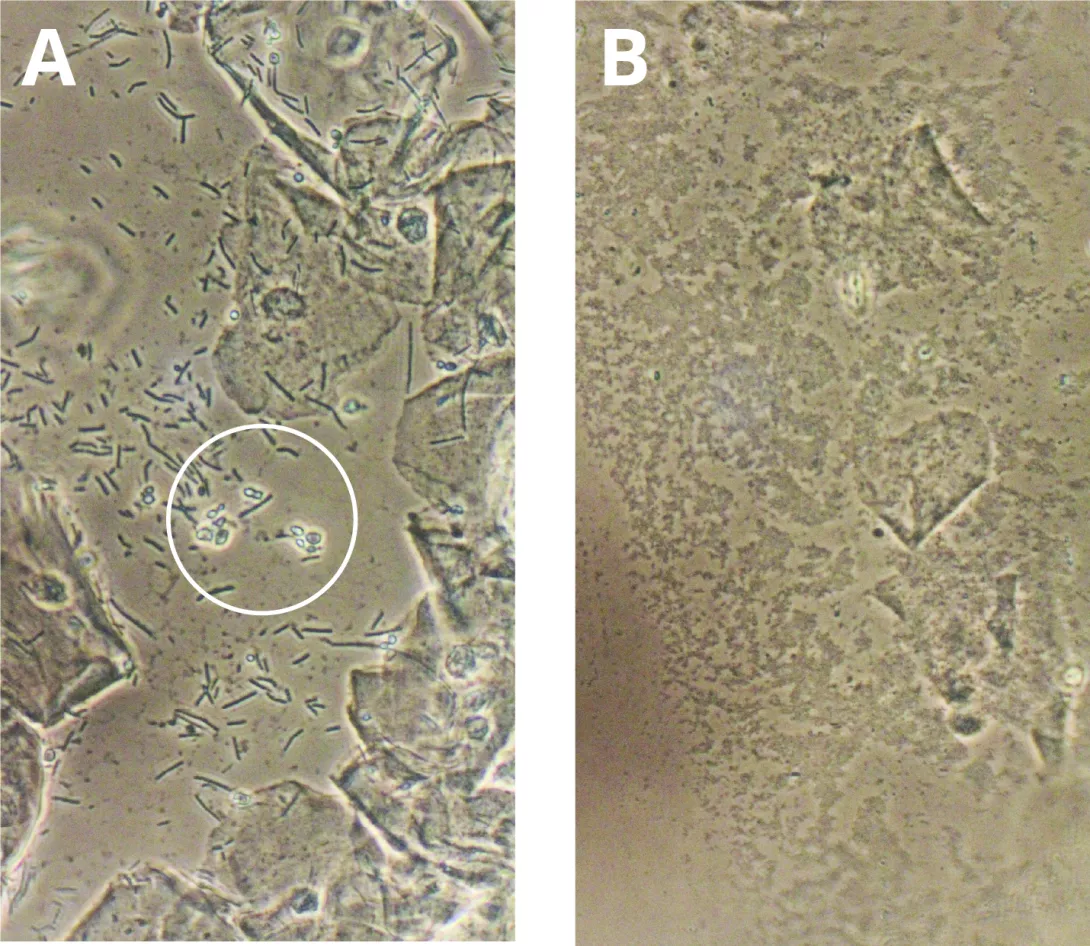
The most noticeable effect of an altered microbiome is vaginitis. Most women will suffer at least one episode of candidiasis and, in some populations, more than half of reproductive-aged women have bacterial vaginosis (BV), asymptomatic most of the time (figure 2A and 2B). We have a limited understanding of what drives these shifts (“normal” – colonisation/asymptomatic state – symptomatic)8.

Figure 2. Microphotographs of wet mount microscopy preparations (phase contrast 400x)

(A) Normal lactobacilli, presence of Candida spp. blastospores (circle); (B) Bacterial vaginosis
(absence of lactobacilli and overgrowth of anaerobic and facultative bacteria).
Image

The vaginal microbiome may confer different profiles of risk or protection.

However, the bacterial profile of the vagina,regardless of symptoms, may confer differentprofiles of risk or protection. In general, it is considered that Lactobacillus spp. tendto confer health benefits. However, not all species are equal and only a limited number of the existing species are usually found in dominating states in the vagina. L. iners, with a significantly smaller genome and different metabolic profile, is usually associated with dysbiotic or transition states9.

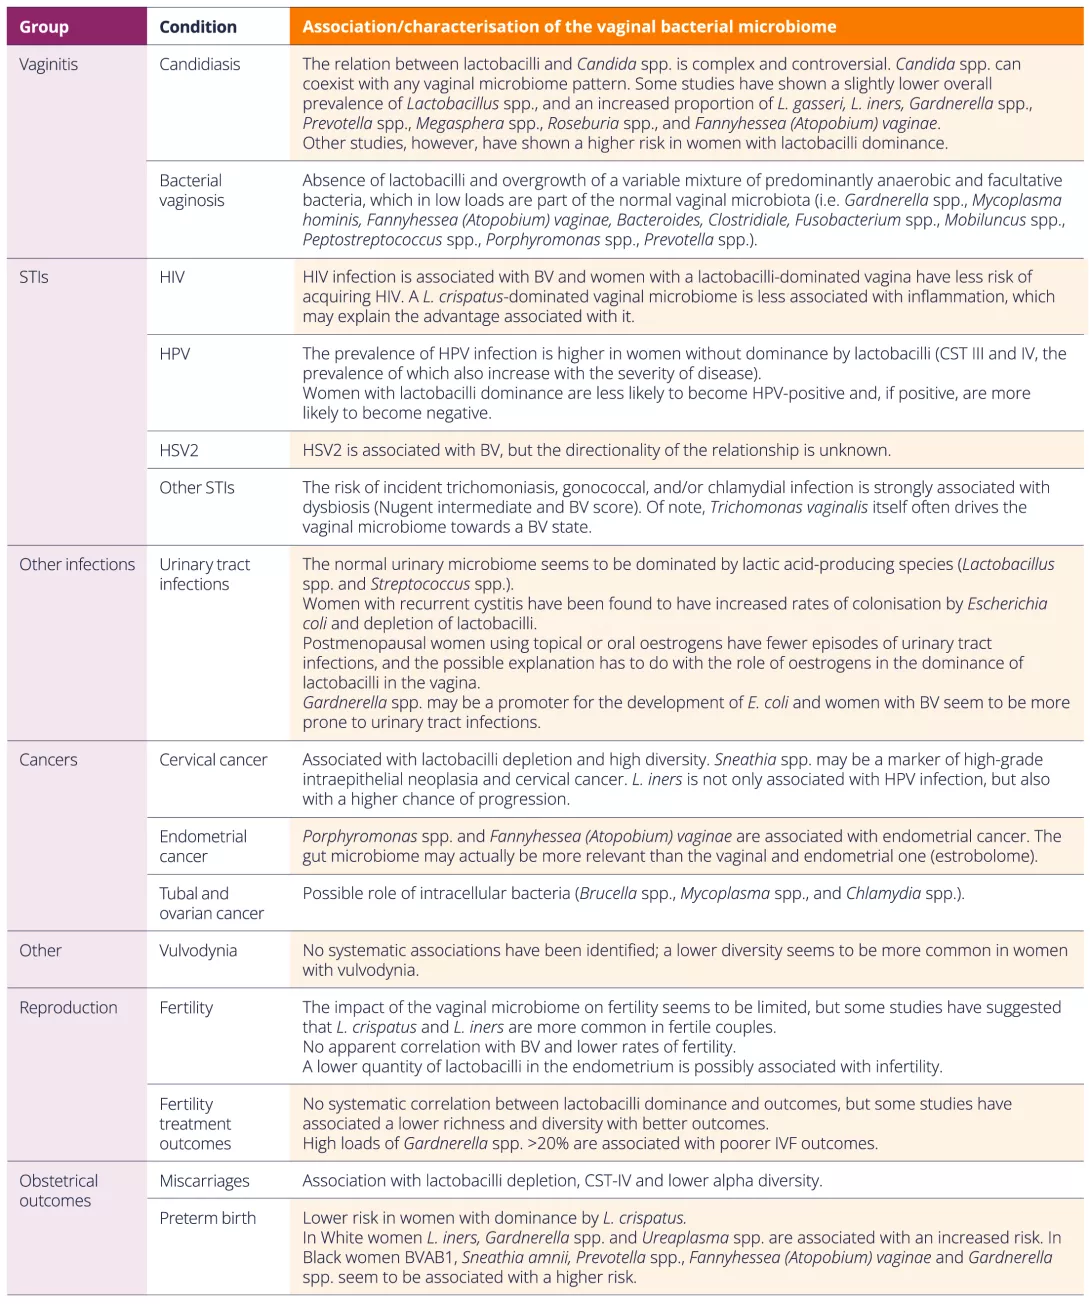
Table 1. Gynaecological and obstetrical conditions and their associations with the vulvovaginal microbiome.

Image

Little is known about the relationship between Candida spp. and the vaginal microbiome.

While there are no current recommendations to treat asymptomatic dysbiosis (e.g. BV), it has been associated with obstetrical and non-obstetrical complications (including risk of acquiring STIs [HPV, HIV])8 (Table 1).

Once efficacious (preferably non-antibiotic) strategies are available, it may be advisable to screen and treat dysbiosis in women at increased risk of STIs or even in those infected with HPV. This, however, may prove more complex than it appears. The STI-like behaviour of BV has long been acknowledged, but recent data have confirmed it, as well as suggesting that reduction of recurrences may require treatment of partners, which may represent a great obstacle to prevention strategies10.

BV is a common syndrome, in which there is depletion of lactobacilli and an overgrowth of several strictly and facultative anaerobic bacteria, associated with formation of a biofilm that seems to contribute to the frequent relapses after treatment. The composition of BV is variable from woman to woman – and probably even in the same woman over time11. Currently it is possible to diagnose BV using molecular tests, but it is expected that with the increasing knowledge of the vaginal microbiome, these tests will allow for the “profiling” of BV, the evaluation of the resistome, and a more rationale choice of treatments8.

The relationship between Candida spp. and the vaginal microbiome is very complex and far from fully understood. While candidiasis can exist with any vaginal microbiome, it tends to be more common with lactobacilli dominance (and the consequent low pH)12.

Several gynaecological conditions have been associated with specific microbiome characteristics and, almost systematically, a reduction in lactobacilli confers an increased risk for STIs and gynaecological cancers (even of the upper genital tract). However, a causal relationship between the microbiome deviations and the specific conditions is not always straightforward. We can, however, expect to one day assess or modulate the risk of cancer through the evaluation of the vaginal microbiome – especially for cervical cancer13.

The interest and knowledge in the vulvar microbiome is more recent and the amount of data is scarce, but its role in entities such as vulvodynia, vulvar dermatoses, vulvar intraepithelial neoplasia and cancer is being studied14-16.

What’s next?

Giant strides are being made towards the understanding of the vulvovaginal microbiome. Until we fully understand the microbiome, we can start by respecting it and its functional role, recognising that each woman is unique (and that this uniqueness is mutable), avoiding
unnecessary use of antibiotics and antiseptics, and properly diagnosing STIs and vaginitis, rather than relying on empiricism. Accurate diagnosis will minimise wrong treatments, with a potential long-term impact.

At this stage, it is essential to distinguish what is investigational and what is clinically relevant. We are in a process of learning and attempting to use investigational techniques and concepts in clinical practice that often leads to unnecessary testing, expenses, and
treatments – for instance, metagenomics is a very useful research tool, but it currently has no place in the clinical evaluation of vaginitis.

In the last two decades we have amassed a huge quantity of information, which will soon translate into better health care for women, including specific dietary recommendations, and pre- and probiotics. We can expect that this knowledge will substantially reduce preterm labour, gynaecological cancers, as well as the recurrence of vaginitis and cystitis.

The next chapters will undoubtedly be the most exciting ones!

CONCLUSION

The human vaginal microbiome is still incompletely understood and some of our current assumptions may need to be updated or adapted as new data emerge. Its full understanding and the potential to manipulate it may be unravelled once the apparent lack of evolutionary logic is completely understood.

However, we can be certain that lactobacilli are of benefit for most reproductive-aged women and that they are fundamental for the success of pregnancy, regardless of geography or ethnicity.

The increasing knowledge in this field is leading to progress in the diagnosis and management of vaginitis and, in the near future, it will
enable the reduction of the risk of serious issues, such as STIs and preterm labour.

Sources
1. Sobel JD. Automated microscopy and pH test for diagnosis of vaginitis - the end of empiricism? NPJ Digit Med 2023; 6: 167.
2. Ravel J, Gajer P, Abdo Z, et al. Vaginal microbiome of reproductive-age women. Proc Natl Acad Sci U S A 2011; 108 Suppl 1: 4680-7.
3. Miller EA, Beasley DE, Dunn RR, et al. Lactobacilli dominance and vaginal pH: why is the human vaginal microbiome unique? Front Microbiol 2016; 7: 1936.
4. Yildirim S, Yeoman CJ, Janga SC, et al. Primate vaginal microbiomes exhibit species specificity without universal Lactobacillus dominance. ISME J 2014; 8: 2431-44.
5. Brandão P, Gonçalves-Henriques M. The impact of female genital microbiota on fertility and assisted reproductive treatments. J Family Reprod Health 2020; 14: 131-49.
6. Solt I. The human microbiome and the great obstetrical syndromes: a new frontier in maternal-fetal medicine. Best Pract Res Clin Obstet Gynaecol 2015; 29: 165-75.
7. Pezzulo C, Nilsen K, Carioli A, et al. Geographical distribution of fertility rates in 70 low-income, lower-middle-income, and upper-middle-income countries, 2010-16: a subnational analysis of cross-sectional surveys. Lancet Glob Health 2021; 9: e802-12.
8. Vieira-Baptista P, Stockdale CK, Sobel J. International Society for the Study of Vulvovaginal Disease recommendations for the diagnosis and treatment of vaginitis. Lisbon: Admedic 2023.
9. Petrova MI, Reid G, Vaneechoutte M, et al. Lactobacillus iners: Friend or foe? Trends Microbiol 2017; 25: 182-91.
10. Vodstrcil LA, Plummer EL, Fairley CK, et al. Male-partner treatment to prevent recurrence of bacterial vaginosis. N Engl J Med 2025; 392: 947-57.
11. Swidsinski A, Amann R, Guschin A, et al. Polymicrobial consortia in the pathogenesis of biofilm vaginosis visualized by FISH. Historic review outlining the basic principles of the polymicrobial infection theory. Microbes Infect 2024; 26: 105403.
12. Swidsinski A, Guschin A, Tang Q, et al. Vulvovaginal candidiasis:
histologic lesions are primarily polymicrobial and invasive and do not contain biofilms. Am J Obstet Gynecol 2019; 220: 91.e1-8.
13. Mitra A, Gultekin M, Burney Ellis L, et al. Genital tract microbiota composition profiles and use of prebiotics and probiotics in gynaecological cancer prevention: review of the current evidence, the European Society of Gynaecological Oncology prevention committee statement. Lancet Microbe 2024; 5: e291-e300.
14. Ventolini G, Vieira-Baptista P, De Seta F, et al. The Vaginal Microbiome: IV. The role of vaginal microbiome in reproduction and in gynecologic cancers. J Low Genit Tract Dis 2022; 26: 93-8.
15. De Seta F, Lonnee-Hoffmann R, Campisciano G, et al. The Vaginal Microbiome: III. The vaginal microbiome in various urogenital disorders. J Low Genit Tract Dis 2022; 26: 85-92.
16. Sacinti KG, Razeghian H, Awad-Igbaria Y, et al. Is vulvodynia associated with an altered vaginal microbiota?: a systematic review. J Low Genit Tract Dis
2024; 28: 64-72.
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article General Medicine Gynecology Off

Microbiota changes in womanhood

What happens to your microbiota as you move through adulthood and why does it matter? From hormonal shifts to chronic diseases, cancer risk, mental health, and libido, scientific research reveals that imbalances in gut, vaginal, skin, and even seminal microbiota can deeply affect women’s health. How do hormones, contraceptives, stress, or aging shape your microbial ecosystems? Can daily habits or diet help restore balance?

Explore the gut-brain axis, intimate microbiota, fertility, and inflammation to understand how supporting your microbiota can promote well-being, prevent disorders, and improve quality of life at every stage of adult womanhood.

Vaginal, intimate balance & microbiota

The female microbiota plays a crucial role in sexual health, menstrual health, fertility, and vaginal diseases. How do hormones, contraceptives, and microbial imbalances shape these areas? Discover the latest scientific insights into the connections between the microbiota and intimate health.

Sexual health, STDs & microbiota

Long overlooked, the links between sexual health, STDs, and the vaginal microbiota are now a growing focus in research, highlighting how microbial ecosystems may influence infection risk, protection mechanisms, and overall intimate balance. 

Contraception & microbiota

Emerging studies suggest contraceptives may alter the vaginal and gut microbiota, potentially affecting infection risk, inflammation, and reproductive health. How do hormones, IUDs or pills shape our intimate microbial ecosystems?

Menstrual health & microbiota

Menstruation triggers shifts in hormones, immunity, and microbial balance. Emerging research reveals how the vaginal and gut microbiota may influence pain, endometriosis, and infections. Could microbes help us better understand menstrual health?

Fertility, pregnancy & microbiota

The role of the microbiota in fertility and pregnancy is a growing area of research. Could a balanced vaginal and gut microbiota improve conception rates and reduce risks of miscarriage or complications during pregnancy?

Vaginal diseases & microbiota

Vaginal health is strongly influenced by the microbiota. Imbalances can lead to pathologies such as bacterial vaginosis, yeast infections and cystitis. What role do these microbial changes play in the development and treatment of vaginal diseases?

Women's hormones & microbiota

Hormonal changes throughout a woman’s life, particularly during menopause, can significantly impact the vaginal, gut, and skin microbiota. How do these shifts influence health ?

Can managing the microbiota help balance hormones for better well-being? Discover the latest research here.

Hormonal balance and microbiota

Hormonal changes, such as those during menopause, influence the microbiota, impacting vaginal, gut, and skin health. How do these shifts affect overall well-being, and can managing the microbiota help maintain hormonal balance?

Menopause & microbiota

Menopause triggers hormonal changes that affect the microbiota, particularly in the vaginal and gut areas. How do these shifts influence inflammation, urinary health, and overall well-being, and what new solutions are emerging to manage them?

Photo: A pro-cancer bacterium in the breast

Chronic diseases, cancers & women's microbiota

Can gut microbiota imbalances increase the risk of cancer, chronic inflammation, or infertility? Disruptions in gut, vaginal, or seminal microbiota may impact IBD, IVF outcomes, and tumor progression opening new avenues for prevention, diagnosis, and therapeutic innovation. Maintaining microbial balance could become a key pillar of Women lifelong health.

Microbiota and cancer: from risk factors to treatment

How does the gut, breast or vaginal microbiota influence cancer risk and treatment? Discover how microbial balance impacts breast and cervical cancer, from pain management to immunotherapy success. Science reveals powerful new allies in cancer care.

Infertility & microbiota

Can microbiota imbalances cause infertility? Discover how gut, vaginal and seminal dysbiosis may affect fertility, IVF outcomes and embryo health. New research reveals microbial targets to support conception and reproductive health in couples.

Inflammation & microbiota

Can an imbalanced microbiota trigger inflammation? From IBD and psoriasis to arthritis or vaginal and urinary issues, explore how gut, skin, and vaginal microbiota shape chronic inflammation and how they may hold the key to predicting and improving treatments.

Prevention & microbiota

Can the microbiota help prevent cancer, infertility, or IBD? Discover how gut, vaginal and seminal microbiota imbalances known as dysbiosis may impact women’s health, and how restoring microbial balance could support disease prevention or even help diagnose. 

Actu PRO Maladie d’Alzheimer : un rôle facilitateur du microbiote intestinal ?

Gut-brain connection in women’s health

Can your gut microbiota affect your mood, stress levels, or even your libido? Many women wonder why they feel anxious, low, or disconnected and science points to the gut-brain axis. Discover how imbalances in gut and vaginal microbiota can disrupt mental and hormonal health, and which daily habits help restore balance and well-being naturally.

Effects of microbiota on mental health

Can gut bacteria influence women’s mental health? In adult life, anxiety, depression and mood swings may be linked to gut microbiota imbalances. Discover how the gut-brain axis shapes emotional well-being and opens new paths for prevention and care.

Effects of microbiota on libido

Can gut microbiota affect female libido? In adult women, low sex drive may be linked to gut dysbiosis, mood disorders, or even the gut-brain axis. Explore how microbial imbalances could influence sexual health and what science reveals about restoring desire.

Microbiota: daily habits that make a difference

What daily habits help keep your microbiota healthy? From gut-friendly foods to intimate hygiene, discover fun, science-backed tips to support a balanced gut and vaginal microbiota and boost overall health and well-being in adult women.

What women know (and don't know)

about their vaginal microbiota

What is the link between microbiota and women’s health? The International Microbiota Observatory, based on a survey of 7,500 people across 11 countries, explores women’s knowledge, perceptions and behaviours of their gut, vaginal, and urinary microbiota. The 2024 edition reveals a global lack of awareness, growing interest in the role of microbiota in hormonal, digestive, and intimate health, and a strong demand for better prevention, education, and support. Dive into the full report to discover key insights, data highlights, and what women worldwide really know about their microbiota.

Discover the 2024 International Microbiota Observatory survey

Explore the results
BMI 25.13
Summary
Off
Hide image
Off
Article

Practices that put your vaginal microbiota at risk

Drinking parties, multiple partners, antibiotics, intimate hygiene products... What are the risk factors for female students’ vaginal microbiota, and which vaginal flora are most at risk?

The vaginal microbiota

A woman’s vaginal microbiota undergoes changes over the course of her life, sometimes to the point of shifting type, as shown by a study 1 including 125 sexually active women aged 18 to 25 in the south of France (Montpellier).

There are five types of vaginal community 2 (Community State Types, or CSTs), which can be divided into three groups in terms of vaginal health, as in this study:

  • Three optimal types dominated by lactobacilli: CST I dominated by Lactobacillus crispatus, CST II by L. gasseri, and CST V by L. jensenii
  • One suboptimal type, CST III, dominated by another lactobacillus (L. iners), which is much more vulnerable to dysbiosis
  • One non-optimal type, characterized by its low lactobacillus content (CST IV)

Lactobacilli, guarantors of stability

The study’s first finding was that bacterial communities dominated by lactobacilli — rod-shaped bacteria known to be most beneficial to women’s intimate health — are more stable over time. In other words, vaginal microbiota rich in lactobacilli such as L. crispatus, L. gasseri, L. jensenii, or L. iners are more difficult to disrupt.

A balanced vaginal microbiota dominated by these lactobacilli will limit the proliferation of pathogens, but if too much stress is put on the microbiota, pathogens can proliferate anyway.

Have you heard of dysbiosis?

Read more

Drinking parties, disrupted vaginal flora

The second finding was the list of factors that can wreak havoc on our vaginal flora.

In the 125 students studied, alcohol was identified as the factor with the strongest and most consistent effect, promoting suboptimal flora and increasing vagina’s vulnerability to infections, particularly by facilitating proliferation of pathogenic bacteria.

Partners, hygiene, and antibiotics

Other factors may also influence the transition from one vaginal bacterial community to another:

  • A higher number of sexual partners may increase the risk of maintaining (or switching to) non-optimal flora, thereby promoting the development of vaginal infections that can progress to bacterial vaginosis. 
     

Studies have shown that genital microbiota can be transferred between sexual partners, potentially destabilizing the resident microbial community.

  • The effects of intimate hygiene products (creams, tablets, capsules, gels, and wipes) on women’s health appear to vary from one woman to the next, with possible circular changes from one type of flora to another. 

The study indicates that probiotics can cause temporary disturbances in the vaginal microbiota. However, they are not among the covariates analyzed in this study.
Intimate hygiene products, for their part, are associated with varying effects on bacterial communities, depending on the type of microbiota present. 

  • As for antibiotic use — whether local treatments for bacterial vaginosis (genital application of metronidazole) or systemic treatments (oral antibiotics) — it appeared to be only loosely associated with transition to a different type of vaginal flora. This absence of an effect surprised the researchers: were the samples taken too far apart to “capture” any short-lived change in flora linked to antibiotics?

In any case

This study shows the fragility of the vaginal flora and its constant state of balance. While vaginal microbiota dominated by lactobacilli appear to be resilient, women should avoid pushing it too far at happy hour, since a student lifestyle that involves too much alcohol can put their microbiota at risk.

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Off

Diabetes prevention: is Candida a good candidate?

There may be a window of opportunity during childhood when the enrichment of the microbiota with certain microorganisms, particularly Candida, is necessary for the development of pancreatic β-cells and, therefore, for the prevention of type 1 or type 2 diabetes and certain metabolic disorders.

In zebrafish (Danio rerio), a bacterial protein promotes the proliferation of β cells in the islets of Langerhans. But what about mammals? Β-cells are necessary for sufficient insulin production, and their proliferation increases rapidly after birth, at the same time as the gut microbiota diversifies.

Is this a mere coincidence or is there a genuine correlation, as in zebrafish? A British team 1 has settled the question by showing in mouse pups that postnatal β-cell development is stimulated by bacterial and fungal species during short colonization windows, periods also critical for metabolic health.

830 million The number of people living with diabetes rose from 200 million in 1990 to 830 million in 2022. ²

14% In 2022, 14% of adults aged 18 years and older were living with diabetes, an increase from 7% in 1990. ²

In mice and humans

By eliminating and restoring microbiota at different pre- and postnatal periods in mouse pups, the team identified a critical period (from 10 to 20 days after birth) during which the gastrointestinal flora is essential for the establishment of a normal mass of β cells. These observations were confirmed by experiments with antibiotics and antifungals, highlighting the involvement of bacteria and fungi in maintaining glycemic balance.

These early alterations in the microbiota have lasting repercussions on metabolism, including decreased carbohydrate tolerance, elevated blood sugar levels, and reduced insulin secretion. All of these imbalances can increase the risk of diabetes.

And in humans? Fecal samples from human infants aged 7 to 12 months (but not from other age groups) strongly stimulated β-cell mass in mice. Humans therefore also appear to have a window of colonization by microorganisms that promote β-cells.

This is yet another argument in support of the much-publicized 1,000-day window of opportunity for future health and the prevention of metabolic diseases such as obesity.

59% More than half (59%) of adults aged 30 years and over living with diabetes were not taking medication for their diabetes in 2022. Diabetes treatment coverage was lowest in low- and middle-income countries. ²

2 million In 2021, diabetes and diabetes-related kidney disease caused over 2 million deaths. In addition, around 11% of cardiovascular deaths were caused by hyperglycemia. ²

Bacteria and fungi responsible

The comparison of microbial communities capable of inducing (or not) β-cell development has identified bacterial and fungal taxa involved in the case of mice: Escherichia coli, Enterococcus gallinarum, and Candida dubliniensis. The latter proved to be the most effective, thanks to a mechanism involving macrophages and β-cells, which allows the recognition of specific signals from the cell wall of commensal yeasts.

Lastly, not only does C. dubliniensis reduce the prevalence and severity of diabetes in mouse models, but it also helps restore the β-cell population after ablation or underdevelopment following antibiotic treatment. By disrupting gut microbiota during early childhood, these treatments can alter glycemic regulation and interfere with the maintenance of stable body weight. Could C. dubliniensis be used prophylactically to make up for losses induced by antibiotic treatment, particularly in individuals predisposed to type 1 or type 2 diabetes or obesity?

Since 2000

Mortality rates from diabetes have been increasing. By contrast, the probability of dying from any one of the 4 main non-communicable diseases (cardiovascular diseases, cancer, chronic respiratory diseases or diabetes) between the ages of 30 and 70 decreased by 20% globally between 2000 and 2019. ²

In April 2021

WHO launched the Global Diabetes Compact, a global initiative aiming for sustained improvements in diabetes prevention and care, with a particular focus on supporting low- and middle-income countries. ²

Preventing or even reversing β cell loss?

This study shows that there may be a critical window in young children, between 7 and 12 months, during which certain bacteria and fungi are necessary for the development of β-cells in the pancreas. If this developmental window is missed, β-cell development may be compromised, leading to dysfunction and an increased risk of metabolic diseases such as obesity and diabetes.

However, the mechanisms identified by the authors of the study have the potential to prevent or even reverse the loss of β-cells, provided intervention comes early and takes into account the key role of the gut microbiota.

Xpeer course: Early establishment of gut microbiota

Learn more
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Gastroenterology General Medicine

Fewer uterine polyp recurrences if vaginal microbiota balanced before surgery

According to a new study, in women scheduled for endometrial polyp removal, a vaginal microbiota imbalance could lead to recurrence. This discovery paves the way for preventive treatments.

The vaginal microbiota Probiotics Prebiotics: what you need to know

According to a new study, in women scheduled for endometrial polyp removal, a vaginal microbiota is well balanced before removing uterine polyps? According to a study published in the European Journal of Obstetrics and Gynecology, this may be the case. The authors, researchers at Nanning University in China, demonstrated that the presence of a vaginal dysbiosis was a major risk factor for the recurrence of polyps after surgical removal. 1

Up to 40% of women Are thought to suffer from endometrial polyps, more often during their fertile years, but also after menopause. ²

In 1/3 of women Uterine polyps resolve naturally. ²

The link between dysbiosis and recurrence results from the impact of this microbial imbalance on the vagina and uterus, two anatomical areas closely connected in terms of immunity and microecology.

Nearly 700 women enrolled

To obtain this result, the researchers collected vaginal secretion samples from 679 women aged 25 to 50 who were undergoing “hysteroscopic resection,” a procedure to remove endometrial polyps. 

What are endometrial polyps?

Endometrial polyps (or uterine polyps) are growths ranging in size from a few millimeters to several centimeters that appear on the lining of the uterus or on the cervix. They are often asymptomatic, but can cause abnormal bleeding, pain, or infertility. In women with infertility problems, it is generally recommended they be surgically removed by “hysteroscopic resection” to increase the likelihood of pregnancy.

This procedure involves inserting a small camera-equipped device called a hysteroscope under local or general anesthesia to view the inside of the uterus, then removing any polyps with an electric scalpel or laser.

After the procedure, the women were followed for two years and the researchers identified a recurrence of polyps in 105 of them.

An analysis of the secretions indicated that women who had vaginal dysbiosis before the operation were 3.3 times more likely to experience a recurrence. This was also the case for women with endometriosis.

An analysis of the microbiotes vaginauxindicated that, in women who suffered from recurrence, the density and diversity of bacteria, as well as the presence of Lactobacilli, were significantly lower than in those with no recurrence. There were also more pathogenic microorganisms, such as the bacterium Gardnerella vaginalis and the fungus Candida, which cause vaginosis and yeast infections, respectively.

The researchers also observed increased activity of certain enzymes, such as leukocyte esterase, a sign of persistent inflammation in the vagina, which can promote infection spreading upward to the uterus.

Decline in Lactobacillus, a key factor in recurrence

How are these abnormalities in the vaginal microbiota involved in the recurrence of polyps? The researchers believe the answer lies with Lactobacillus.

Under normal circumstances, these bacteria produce bacteriocins, substances capable of destroying pathogens, as well as lactic acid, which acidifies the vaginal environment and stabilizes microbiota. They also synthesize molecules called glycerophospholipids, which in turn promote secretion by the body of anti-inflammatory messengers called prostaglandins. Lastly, they increase the synthesis of proteins that are involved in the integrity of the vaginal wall.

Thus, by reducing the risk of infection and inflammation after surgery, Lactobacillus may help protect against polyp recurrence.

This beneficial action is all the more important in women with a history of chronic microbial imbalances or endometriosis, for whom the risk of recurrence is significantly higher.

Between 10%-15% and 58.1% The recurrence rate of uterine polyps after resection, depending on the study. ¹

95% Of uterine polyps are benign.¹

Towards preventive treatments

The researchers highlight the importance of maintaining the balance of the vaginal microbiota, particularly the long-term dominance of Lactobacillus, in cases of uterine polyps. They suggest several possible preventive treatments:

  • a combination of probiotiques and antimicrobials, which would make it possible to tackle immediate pathogenic imbalances while promoting long-term microbial health;
  • lactic acid-based gels or vaginal suppositories;
  • bacteriophages, viruses capable of selectively destroying pathogenic bacteria without disrupting the microbiota;
  • prebiotics and omega-3 fatty acids, which promote balanced microbiota.

These modulation strategies could also improve overall vaginal health by reducing the risk of persistent infection.

While studies are still needed to evaluate the effectiveness of these interventions, these avenues are promising. Keep informed!

Female anatomy, microbiotas and intimate hygiene

Learn more
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Off