A bacterium that prevents diabetes mellitus?

For the time being, this dream has only been validated in test tubes and in mice, not yet in humans. However, the A. indistinctus bacterium may improve insulin resistance in people with pre-diabetes.

The gut microbiota Type 2 diabetes

(sidenote: Diabetes mellitus Chronic disease that occurs either when the pancreas does not produce enough insulin or when the body cannot effectively use the insulin it produces. Over time, diabetes can damage blood vessels in the heart, eyes, kidneys and nerves. ) is all about sugar, and more specifically, blood sugar levels ( (sidenote: Glycemia Blood sugar level. ) ). The aim is to avoid peaks (i.e., hyperglycemia) following meals. In healthy individuals, (sidenote: Insulin Hormone produced by the pancreas tasked with lowering blood sugar levels to around 1 g/L.  ) regulates blood sugar levels at around 1 g/L. In diabetic patients, the body fails in this regard, either because the pancreas does not produce enough insulin (type I diabetes mellitus), or because the body resists insulin’s commands (type II diabetes mellitus). The gut microbiota appears to be involved in the insulin resistance observed in type II diabetes, but the mechanisms involved remain unclear. Or rather “remained” unclear, since a study published in the prestigious journal Nature has shed some light on the subject.

Micro-sugars promote insulin resistance

The researchers concluded that the richer our stools are in certain molecules, the greater our resistance to insulin. The feces of insulin-resistant volunteers contained far more (sidenote: Carbohydrates A family of macronutrients that includes sugars (i.e., simple carbohydrates), which often have a sweet taste and include glucose, fructose, galactose, maltose, lactose, and sucrose; and starches (i.e., complex carbohydrates). ) , particularly tiny (sidenote: Sugars Fructose, galactose, mannose and xylose. ) produced by bacteria. These micro-sugars are far from harmless. They promote fat accumulation, stimulate our immune system to the point of causing inflammation (admittedly mild, but prolonged and harmful), and ultimately lead to insulin resistance.

2 million deaths related to diabetes mellitus (1.5 million) and diabetes-related kidney disease (0.5 million) in 2019.

422 million diabetic patients in 2014, compared with 108 million in 1980.

+3% Between 2000 and 2019, there was a 3% increase in diabetes mortality rates by age.

Image

The bacteria involved

Two types of bacteria seem to be involved:

  • bacteria of the Lachnospiraceae family, which are associated with a higher production of these tiny sugars and insulin resistance; and
  • Bacteroidales (Bacteroides, Alistipes, and Flavonifractor), which reduce levels of these sugars and insulin resistance.

A direct effect of the “friendly” Bacteroidales has even been measured in test tubes, where they devour the micro-sugars. The most gluttonous? The bacterial species Alistipes indistinctus consumes the widest variety of micro-sugars. It also works in obese mice, where a pinch of A. indistinctus lowers the amount of micro-sugars in mice’s stools, lowers blood sugar levels, and makes the mice more sensitive to insulin. 

Although human trials are clearly essential before any recommendations can be made, these findings have two main implications:

• Lachnospiraceae may be a biomarker of pre-diabetes; and

• the probiotic A. indistinctus may improve insulin sensitivity in pre-diabetic individuals.

The gut microbiota

Learn more
Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News

Partnerships

Since its creation, the Biocodex Microbiota Institute has forged strong partnerships with patient associations, learned societies and public health organizations. Together, we pursue a common goal: to inform, educate and raise awareness of the importance of the microbiota to our health.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Off

Can antibiotics promote the growth of harmful bacteria in the gut?

Antibiotics are lifesavers, but they can also have unexpected consequences. A new research shows how antibiotics can promote the growth of harmful bacteria in the gut and points the way to new treatments.

Antibiotic resistance is a pressing global public health concern that resulted in 1.27 million deaths worldwide in 2019 1. One approach to prevent these infections, particularly Carbapenem-resistant Enterobacteriaceae (CRE), is to understand what drives the colonization of the intestine by these bacteria.

Your gut is home to a diverse community of beneficial bacteria that help prevent harmful pathogens like CRE from taking hold. Healthy gut bacteria have mechanisms to prevent the colonization of pathogens, such as production of beneficial molecules, also called metabolites, like (sidenote: Short chain fatty acids (SCFA) Short chain fatty acids (SCFA) are a source of energy (fuel) for an individual’s cells. They interact with the immune system and are involved in communication between the intestine and the brain. Silva YP, Bernardi A, Frozza RL. The Role of Short-Chain Fatty Acids From Gut Microbiota in Gut-Brain Communication. Front Endocrinol (Lausanne). 2020;11:25. ) ). Broad-spectrum antibiotics disrupt these mechanisms and promote the growth of antibiotic-resistant bacteria.

40%–50% CRE infections are associated with mortality rates as high as 40%–50%

Antimicrobial resistance: a global threat, an international response

Learn more

The yin-yang effect!

Are Broad-spectrum antibiotics responsible for increased risk of infection with CRE? Yes, according to the 2023 study published in Nature Communication by a researcher from Imperial College London 2.

Eight broad-spectrum antibiotics were tested on faecal samples from healthy human donors:

  • meropenem
  • imipenem/cilastatin
  • ertapenem
  • piperacillin/tazobactam
  • ciprofloxacin
  • ceftriaxone
  • ceftazidime
  • and cefotaxime

These antibiotics are known to promote susceptibility to CRE intestinal colonisation. The researchers used a specific growth medium to measure: 1) the impact of the antibiotics on the abundance of gut commensal taxa from the faecal microbiota, 2) nutrients and microbial metabolites concentration in the faecal cultures.

The study showed that broad-spectrum antibiotics, often used to treat infections, can disrupt the balance of your gut microbiota. They reduce the population of beneficial bacteria (including Bifidobacteriaceae and Bacteroidales), making it easier for CRE to flourish.

What was even more interesting is that when piperacillin/tazobactam were tested in a mouse model, these antibiotics not only affected the bacteria but also altered the environment in gut. They increased the availability of certain nutrients, like amino acids, that support the growth of CRE. This nutrient-rich environment becomes a breeding ground for the resistant bacteria.

On the flip side, these antibiotics decreased the concentration of microbial metabolites, such as butyrate or propionate, some of which inhibit the growth of CRE. When these metabolites are depleted, CRE has fewer obstacles in its path.

Antibiotic resistance

Antibiotic resistance is a major global threat, and the emergence of formidable pathogens CRE poses a serious challenge to public health. Understanding the role of the gut microbiota in antibiotic resistance is paramount.

Short-chain fatty acids (SCFAs) are key metabolites produced by beneficial gut bacteria that act as guardians of gut health. However, the indiscriminate use of broad-spectrum antibiotics can disrupt the gut microbiota, leading to a decrease in SCFA production and an increase in the growth of antibiotic-resistant bacteria.

As medical professionals, we must be aware of the intricate interactions within the gut microbiota. By carefully considering the impact of antibiotics on the delicate balance of the microbiota, we can take a step closer to combatting antibiotic resistance effectively and preserving the health of our patients. 

What is the World AMR Awareness Week?

Each year since 2015, the WHO organizes the World AMR Awareness Week (WAAW), which aims to increase awareness of global antimicrobial resistance.

Held on 18-24 November, this campaign encourages the general public, healthcare professionals and decision-makers to use antimicrobials carefully to prevent the further emergence of antimicrobial resistance.

Recommended by our community

"Congratulations on the wonderful medical profession"  -@PhucTra01451784 (From Biocodex Microbiota Institute on X)

"I salute your efforts"  -@EmmanuelMedical (From Biocodex Microbiota Institute on X)

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News General Medicine Gastroenterology Pediatrics Off

Fecal transplant: “where, when, how much” needed to optimize effects on IBS?

What is the best combination of factors for fecal transplantation as a treatment for irritable bowel syndrome (IBS)? According to Norwegian researchers and clinicians, a transplant dose of between 60 g and 90 g into the small intestine, rather than the colon, and ideally repeated.

IBS

44% Only 2 out of 5 people said their doctor had informed them of the appropriate behaviors to adopt to preserve their microbiota balance

Between 2015 and 2020, fecal microbiota transplant (FMT) as a treatment for irritable bowel syndrome (IBS) was tested in seven randomized controlled trials (RCTs). The outcomes of these RCTs varied considerably, probably due to differences in the protocols used. A Norwegian team studied the effects of FMT dose, repetition, and area of administration, using the same protocol as in their previous RCT, which saw very good results (long-standing effects up to three years after FMT, with only a few mild adverse effects). The transplant came from the same (sidenote: Super-donor A donor with high microbial diversity, whose microbiota quality conditions FMT results. In this case, a healthy, non-smoking 40-year-old Caucasian male born vaginally, breastfed, who had taken only a few courses of antibiotics during his life, took no medication regularly, had a normal BMI, exercised regularly, and took sport-specific dietary supplements (which made his diet richer than average in protein, fiber, minerals, and vitamins). ) .

Symptoms improved with repeated FMT

This new study included 186 patients suffering from irritable bowel syndrome, randomized into three groups receiving a 90 g fecal transplant (versus 30 g or 60 g in the previous RCT) either to the colon, to the duodenum, or twice to the duodenum with a one-week interval.

In the year following the FMT, the researchers observed a much lower prevalence of (sidenote: Assessed using the IBS-SSS, the Birmingham IBS Symptom Questionnaire (BSQ) and the Fatigue Assessment Scale (FAS). ) , regardless of the group and the time elapsed since FMT: present in 75% of patients on the day of transplantation, they affected 17%-32% (depending on the group) after 3 months, and 24%-41% after one year. Similarly, (sidenote: Assessed using the IBS Quality of Life Instrument (IBS-QoL) and Short-Form Nepean Dyspepsia Index (SF-NDI) questionnaire. ) improved in all three groups, regardless of the time elapsed since FMT. Moreover, repeating transplantation improved the beneficial effects on symptoms and quality of life.

Your IBS Diagnosis Check List

Learn more

Favoring the small intestine over the colon

An analysis of fecal samples (16s rRNA) taken at baseline and at 3, 6, and 12 months after FMT showed a significant reduction in dysbiosis in all treatment groups. Bacterial profiles changed considerably following FMT for all three groups and at all observation dates, with differences between the groups. These changes notably concerned six bacteria linked to symptoms and fatigue, such as Alistipes spp., implicated in several diseases such as depression, anxiety, and chronic fatigue syndrome, or Holdemanella biformis, which has anti-inflammatory effects.

Transplanting into the small intestine enables the colonization of beneficial bacteria over the long term, unlike transplanting into the colon, where the effect appears to be more transient. Conversely, while the beneficial effect increased with dose in the previous RCT (greater effect at 60 g than at 30 g), the 90 g dose has no additional benefit compared with the 60 g already tested: the optimal dose would therefore be between 60 g and 90 g.

Explain fecal transplantation to your patients with this dedicated content: 

Summary
Off
Sidebar
On
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
News Gastroenterology Off

Microbiota: essential to health, but limited global awareness

What do our fellow citizens know today about the role of microbiota? What do they know about how to take care of their microbiota? What role do healthcare professionals play in informing patients? To answer these questions, the Biocodex Microbiota Institute commissioned Ipsos to conduct a major international survey on the subject: the International Microbiota Observatory. To carry out this survey, Ipsos questioned 6,500 people in 7 countries1 . The survey was conducted from March 21 to April 7, 2023. The results were presented on June 27, World Microbiome Day.

Very little knowledge of the word “microbiota”

As a general rule, knowledge of microbiota is fairly low: only 1 in 5 people say they know the exact meaning of the term microbiota (21%), while the rest admit to knowing the term by name only (43%). More than 1 in 3 people say they’ve never even heard of the word (36%). Moreover, when we dig deeper into their level of knowledge, the notions are superficial. While a small majority claim to know the intestinal microbiota (53%, but only 24% know exactly what it is), other types of microbiota are much less well known: whether it’s vaginal microbiota (45% of interviewees know the term, but only 18% know exactly what it is), oral microbiota (43% know it by name, but 17% know what it is) or skin microbiota (40% know the term, but only 15% know what it is). Others are even less well known, such as urinary microbiota (only 14% know exactly what it is), pulmonary microbiota (13% know exactly what it is) and ENT microbiota (11% know exactly what it is).

And relatively poor knowledge of the role and importance of microbiota

Around 3 out of 4 interviewees are aware that a risk of microbiota imbalance can have major consequences for health (75%), that our diet has major consequences on the balance of our microbiota (74%) and that our microbiota play a real role in immune defense mechanisms (72%). For the rest, knowledge remains very moderate. More than 1 in 3 people are unaware that antibiotics have an impact on our microbiota (34%). Nearly 1 in 2 people are unaware that microbiota are made up of bacteria, fungi and viruses (46%), and that they enable the gut to deliver essential health information to the brain (47%). 1 in 2 people think that when our microbiota is unbalanced or malfunctioning, there’s not much we can do about it (47%). Finally, the vast majority of those interviewed were unaware that many diseases, such as Parkinson’s, Alzheimer’s and autism, could be linked to microbiota (75%).

1 in 5 people know what the word microbiota means (21%)

24% said they know exactly what gut microbiota is

1 in 3 people have been informed by a healthcare professional that antibiotics can upset the microbiota balance (33%)

The beginning of awareness?

More than 1 in 2 people today say they have adopted behaviors in their daily lives to maintain the balance of their microbiota (57%). This new awareness is to be applauded, but it should also be put into perspective. Firstly, because only 1 in 7 people say they do this “a lot” (15%), while most of the others say they do it only “a little” (42%). Secondly, 43% of those questioned said they had not adopted any specific behavior. The results of the International Microbiota Observatory show that there’s still a lot to be done in this area.

Information provided by healthcare professionals: a game-changing vector of information!

Fewer than 1 in 2 patients say that their doctor has ever explained to them how to maintain balanced microbiota (44%, but only 19% have had this explained to them more than once), or prescribed probiotics or prebiotics (46%, but only 21% say they have done so several times). Only a minority of those interviewed claim to have been made aware by their doctor of the importance of having a well-balanced microbiota (42%). Finally, only 1 in 3 said their doctor had ever taught them what microbiota was and what it was used for (37%, and only 15% had had this explained to them several times).

The information provided by doctors when prescribing antibiotics illustrates just how inadequate it still is to make patients aware of the risks of treatment in terms of microbiota imbalance. Prescribing antibiotics should be an opportunity to provide essential information on the microbiota, but in many cases it isn’t. When prescribing antibiotics, for example, the patient’s microbiota is at risk. When antibiotics are prescribed, less than 1 in 2 patients say that their doctor has informed them of the risk of digestive problems associated with antibiotics (41%). Only 1 in 3 were given advice on how to minimize the negative consequences of taking antibiotics on their microbiota (34%) or informed that taking antibiotics could have negative consequences on the balance of their microbiota (33%).

What the survey shows is that once a patient has received all the information on the subject, and repeatedly, his or her relationship with microbiota changes significantly, and stands out from the average. More than 9 out of 10 people (95%) who have received repeated information from their healthcare professional have adopted behaviors to keep their microbiota balanced, compared with 57% of all those surveyed. Repeated information from a healthcare professional therefore has a very strong impact on knowledge levels and behaviors.

This exclusive survey reveals both a general lack of understanding of how the microbiota affects our health and the essential role of healthcare professionals in imparting knowledge.

1 in 2 patients say that their doctor has ever explained to them how to maintain balanced microbiota

95% of people having received information repeatedly from their healthcare professional have adopted behaviors to limit the risk of microbiota imbalance

vs 57% Overall

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Article Gut microbiota

The impact of gravity on irritable bowel syndrome

By Dr. Maria Teresa Galiano
Gastroenterology and Endoscopy Service, Servimed, Bogota, Colombia

In a recent paper [1], it has been suggested that IBS may result from ineffective anatomical, physiological, and neuropsychological gravity management systems designed to optimize gastrointestinal form and function, protect somatic and visceral integrity, and maximize survival in a gravity-bound world.

Could you comment on this hypothesis with your clinical point of view?

This hypothesis is very interesting. I think it can be considered among the multiple hypotheses that seek to explain irritable bowel syndrome. However, it must be tested. Studies must be conducted to prove that physical alterations due to the changes in gravity affect gastroenterological physiology. I think it may be true that gravity affects an organism’s physiology and that we are usually in balance with this permanent force to which humans and all living things on Earth are subjected. The consequences arising when this equilibrium is altered can include IBS.

Do you agree with the author explaining that consequences of gravity result in gut microbiota alteration?

I agree with the author that gravity can alter gut microbiota and that it can also alter its functioning, including fermentation. I think it can also alter the volume of gas that acts upon the bowel wall. This also must be tested in the corresponding studies, but I agree with the author’s point regarding gut microbiota’s susceptibility to gravity.

Would you share this hypothesis with your patients?

I would share this hypothesis with patients to whom I believe this hypothesis may apply based on their physiopathology and as a possible explanation for their symptoms. As a matter of fact, I see in changes in my patients when they travel to places that are at sea-level and come back to Bogota where I live. Bogota is located 2,600 meters above sea-level. When these patients return to Bogota, they exhibit more symptoms because of changes in barometric pressure. Changes in barometric pressure cause changes in sensation, distension, and gas in the bowels. On many occasions, I explain their symptomatology based on the changes in their physiology that result from the different altitudes that they experience. The changes that occur due to variations in the equilibrium with the force of gravity could be used to explain these patients’ symptoms.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Expert opinion Irritable bowel syndrome

Vaginal Microbiota #19

By Pr. Satu Pekkala
Academy of Finland Research Fellow, Faculty of Sport and Health Sciences, University of Jyväskylä, Finland

Cervical cancer: the walls are closing in on Lactobacillus iners

Shi W, Zhu H, Yuan L, et al. Vaginal microbiota and HPV clearance: A longitudinal study. Front Oncol 2022; 12: 955150.

High-risk human papillomavirus (HRHPV) is the leading cause of cervical cancer. Sexual activity, smoking, and oral contraception are among the many factors that influence initial infection, the resolution or the onset of HR-HPV, and potential progression to cancer. In recent years, the vaginal microbiota has been added to this list. The value of this study is therefore clear, since it monitored the cervical microbiota of HR-HPV infected Chinese women presenting histologically confirmed, and mostly low-grade, cervical lesions. A 16S rRNA analysis of the microbiota of the 73 participants in the study (aged between 24 and 68 years) showed that HPV had disappeared in 45 of the women (61.6%) by the end of the twelve-month study period. The clearance or otherwise of the virus was not due to differences in the patients’ age, the stage of the disease, the HPV subtype, the type of vaginal bacterial community, or vaginal microbiota diversity. Instead, certain bacterial species seem to be involved: women depleted in enterococcus ASV_62 and enriched in Lactobacillus iners at baseline were less likely to have HPVHR clearance at month twelve. The only exception was 22 women who underwent surgical treatment (conization) for highgrade lesions, perhaps because the immediate impact of lesion resection on HPV clearance masked the impact of the flora. A possible link between L. iners and HR-HPV had previously been reported by a meta-analysis suggesting a two- or even three-fold higher risk of persistent HR-HPV when the vaginal microbiota is dominated by L. iners. This bacterium appears to be both flexible and adaptable, dominating the vaginal microbiota of certain women during menstruation or episodes of bacterial vaginosis. On the other hand, a vaginal microbiota dominated by L. iners (CST III) is frequently reported as one of the most common types of vaginal bacterial community among Asian child-bearing age women. Therefore, it is not yet clear from the current literature whether this particular strain of Lactobacillus should be considered beneficial, pathogenic, or both. Further work is also needed to clarify the mechanisms by which L. iners promotes persistent HPV infection or lesion progression, especially since the current study involved a small number of patients.

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Press review

Gut Microbiota #19

By Pr. Satu Pekkala
Academy of Finland Research Fellow, Faculty of Sport and Health Sciences, University of Jyväskylä, Finland

Microbial metabolism of 5-ASA in inflammatory bowel disease

Mehta RS, Mayers JR, Zhang Y, et al. Gut microbial metabolism of 5-ASA diminishes its clinical efficacy in inflammatory bowel disease. Nat Med 2023; 29: 700-9.

Inflammatory bowel disease (IBD) is treated with 5-aminosalicylic acid (5-ASA). However, more than half of the patients do not respond to the treatment. Previous studies have suggested that this is partly due to that 5-ASA can be metabolized by gut bacteria into N-acetyl 5-ASA that is clinically ineffective. In this elegant study Mehta et al. aimed at identifying the gut microbial enzymes that generate N-acetyl 5-ASA. The human stool samples were analyzed using multi-omics. The untargeted metabolomic analyses of the samples pre-5-ASA and post-5-ASA administration revealed potential microbial mediators of the anti-inflammatory effects of 5-ASA. These included a decrease in 2-aminoadipate, a bacterial metabolite that has been linked to greater oxidative stress. In addition, 5-ASA seemed to alter nicotinate metabolism, which may also explain some anti-inflammatory effects. The authors further sought to identify the microbial enzymes that potentially metabolize 5-ASA. By combining metatranscriptomics and metabolomics, they identified three Acetyl-CoA C-acetyltransferases (Acyl-CoA NAT) that associated with the N-acetyl 5-ASA levels in 5-ASA users. In addition, some thiolases were identified as potential candidate enzymes. The candidate enzymes were then heterologously expressed in Escherichia coli and their biochemical activity was measured. Firmicutes CAG:176 thiolase and Faecalibacterium prausnitzii acyl-CoA NAT were able to acetylate 5-ASA using acetyl-CoA. Ultimately, a metagenomic analysis of the stool samples revealed that the gut microbial 5-ASA-inactivating acetyltransferases associated with greater risk of treatment failure in 5-ASA users. Altogether, the findings of this study can help in advancing the possibility of microbiome-based personalized treatment of IBD.

Image

Helicobacter pylori and colorectal cancer

Ralser A, Dietl A, Jarosch S, et al. Helicobacter pylori promotes colorectal carcinogenesis by deregulating intestinal immunity and inducing a mucus-degrading microbiota signature. Gut 2023; 72: 1258-70.

Helicobacter pylori infection can lead to gastric cancer and increase the risk for colorectal cancer (CRC). However, mechanistic data on the latter is lacking. In this paper, Ralser and co-workers identify in a rodent model the underlying mechanisms of how H. pylori infection contributes to CRC. When the authors infected Apc mice that are excellent animal models bearing multiple intestinal neoplasia with H. pylori, an increased tumor burden in the small intestine and colon was observed. It is known that the T-cell immune response of the host contributes to gastric carcinogenesis, and therefore, the authors studied these responses in the intestines. They found a reduction in regulatory T cells and pro-inflammatory T cells as well as an increase in IL-17A, which is shown to be one of the main players in the immune response to H. pylori. The infected mice were characterized by higher abundance of so-called pro-inflammatory gut microbes, and mucus degrading bacteria, such as Akkermansia. By studying transcriptomic profiles of the intestinal epithelial cells, they found that H. pylori induced the activation of NF-κB and STAT3 pathways. Activation of these pathways has been previously shown also in CRC patients. Interestingly, germ-free mice infected with H. pylori scarcely showed activation of STAT3 signaling suggesting that H. pylori induced carcinogenesis in the small intestine is partly dependent on the gut microbiome. Ultimately, the authors show that H. pylori induced colorectal carcinogenesis can be prevented by eradication of the bacterium with antibiotics. The authors conclude that implementation of H. pylori status into preventive measures of CRC should be considered.

Image

Viral diversity in the healthy infant gut

Shah SA, Deng L, Thorsen J, et al. Expanding known viral diversity in the healthy infant gut. Nat Microbiol 2023; 8: 986-98.

In infancy, the gut microbiome contributes to the maturation of the immune system to protect against chronic disease later in life. While it is known that bacteriophages (i.e., bacteria infecting viruses) can control the growth of bacterial populations, the gut viromes have not been extensively studied. By using metagenome sequencing, this study analyzed 647 viromes of a Danish cohort of 1-year-old infants. The first striking finding was that infant gut vOTUs were largely absent from gut virus databases. This suggests that the infant gut harbors specialized viruses distinct from the adult gut. The most predominant viral clades of the infants were largely undescribed. However, vertebrate-infecting ssDNA anelloviruses (Anelloviridae) and bacterial ssDNA microviruses (Petitvirales) were among the most abundant. In addition, virulent caudoviral families Skunaviridae, Salasmaviridae, β-crassviridae and Flandersviridae were also well represented in the infant viromes. Overall, temperate viruses were less prevalent than the virulent ones despite being found in more children. Family-level abundance was not significantly linked to phage lifestyle as determined by integrase as an indicator of a temperate lifestyle. However, temperate caudoviral families were genetically more diverse than the virulent families. Prediction analysis of the bacterial hosts of the viromes showed that Bacteroides, Faecalibacterium and Bifidobacterium were the three most prominent host genera in the infants’ gut. Of these, Bacteroides-infecting families were more often virulent and host specific. While no clear conclusions were provided, the study increases the knowledge on phage taxonomy and aids in the development of future infant gut virome research.

Image
Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Press review Gut microbiota

Highlights from the 55th Espghan

By Dr. Tania Mahler
MD, Pediatric Gastroenterology & Nutrition - Chronic Pain & Functional Gastrointestinal Disorders - Qualifications in mindfulness and medical hypnosis for functional GI disorders. Clinical adjunct at Queen Fabiola Children’s University Hospital, Belgium

At the ESPGHAN (European Society of Pediatric Gastroenterology Hepatology and Nutrition) 2023 meeting held in Vienna, 4,300 participants from all over the world gathered. Following the challenging period of the Covid-19 pandemic, this event offered a revitalizing experience, as attendees were able to engage in live presentations and have faceto-face discussions This in-person interaction proved to be significantly more enjoyable and enriching than virtual alternatives. Various research groups focused their work on the gut microbiome and presented compelling data in the field of pediatrics.

The microbiome’s impact on health and disease is widely recognized, so it is evident that also pediatric clinicians and researchers try to get a better understanding of how we can manipulate the microbiome and how by using the signature of the microbiome we can detect disease in an early stage. This review aims to shed light on several key topics that have been extensively discussed.

Recommendations for the use of probiotics in selected pediatric gastrointestinal disorders

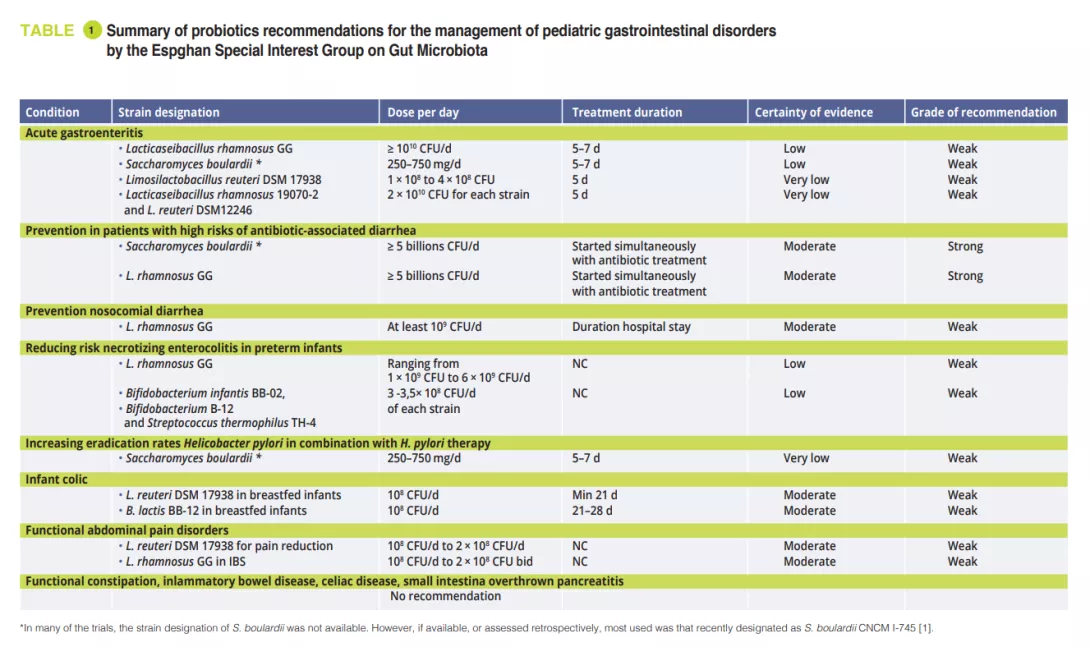
In February 2023, the Espghan special interest group on gut microbiota published recommendations for the use of probiotics for the management of selected pediatric gastrointestinal disorders based on systematic reviews and/or meta-analyses using the modified Delphi-process [1]. At the meeting of the special interest group on gut microbiota and modifications Prof. Szajewska showed us the results of this work. Only a few specific probiotic strains proof some utility in certain conditions. In the original paper [1] you find a clear overview of the actual recommendations.

FMT in adolescents suffering from refractory IBS

Dr De Bruijn from the group of Amsterdam UMC reported in the plenary session of the highest scoring abstract their study on the efficacy of FMT in adolescents with refractory IBS in a randomized double-blind placebo controlled trial [2]. Her talk was fascinating but also stirred a lot of reactions in the audience when she showed a slide from a patient receiving syringes with fecal material. To our knowledge only one other pediatric study has evaluated FMT to relieve abdominal bloating, another feature of disorders of the gut-brain interaction and which is often present in IBS [3].

The chronic pain in IBS can have an enormous impact on the functioning of children and adults leading to absenteeism at school and work and a poor quality of life. The origin of the disease is multifactorial and can best be explained by the biopsychosocial model. One of the key role factors is dysbiosis of the gut microbiota. In adults’ different studies have been published over the positive effect seen with FMT [4].

In pediatrics non-pharmacological treatments as education, hypnosis, mindfulness are more effective than pharmacological therapy [5]. Still in approximately 25% of patients’ symptoms persist. Pre-, pro-, and synbiotics are tested with various outcomes to correct the dysbiosis in IBS. Changing to FODMAP diet can also influence the gastrointestinal flora [5]. But in specific groups of patients FMT could be, if safe, the ultimate treatment to effectively restore a healthy gastrointestinal microbiome. In the study of De Bruijn et al., 32 patients with refractory IBS between 16 and 21 years old were recruited and randomized. One group received allogeneic (healthy donor) and the other group autologous (own) fecal infusions by nasogastric tube at baseline and 6 weeks later. Clinical efficacy was defined as the proportion of patients with a reduction of more than 50 points in the IBS Severity-Scoring-System (IBS-SSS). Patients were evaluated 12 weeks and 6 months after TMF. Both groups had similar IBSSSS at baseline. After the first evaluation there was no statistical difference, but at 6 months of follow-up there was improvement in 60% of the patients that received allogeneic TMF versus 25% in the autologous group (p = .048). Secondary outcome included health-related quality of life (QoL). Total QoL score at baseline did not differ between groups but became significantly better after allogeneic TMF. No adverse events were recorded. Allogeneic TMF seems an exciting way to treat refractory IBS in youth, but further studies are needed.

Image

Microbiota and IBD

In the gastroenterology session on IBD a Czech group presented a study that had as aim to evaluate if the changes in microbiota in CD was due to the anti-TNFα treatment or was the result of decreased mucosal inflammatory activity [6]? Therefore, they compared children on anti-TNFα treatment with active Crohn’s disease (CD) and juvenile idiopathic arthritis (JIA). Their results showed that mucosal healing in CD was essential to obtain changes in the bacteriome. The antiTNFα treatment in JIA had no impact on the bacteriome of these patient group. Schwerd et al. followed 20 newly diagnosed pediatric CD patients treated first with exclusive enteral nutrition (EEN) with stool sampling [7]. Fifteen out of twenty patients went in remission. They demonstrated clear temporal and individual intestinal microbial and metabolite changes with reduced abundance of Lachnospiraceae and enriched unsaturated long chain fatty acids. Ex vivo fermentation with an EEN-like media and subsequent transfer in gnotobiotic mouse models showed a protective effect in contrast to the fiber-rich media and to those colonized directly with patient’s baseline microbiota. Based on those results they concluded that EEN-modulated patient microbiomes are regulating intestinal inflammation. They also elaborated on the possibility of using a low-fiber diet for long-term remission. A multicenter study in the UK (children and adults) studied the possibility to use a Crohn’s Disease TReatment-with-EATing (CD-TREAT) solid food diet to create a more palatable diet that could influence gut inflammation by changing the gut bacteria [8]. The diet is personalized for each patient but excludes specific dietary components such as gluten, lactose, alcohol. The 55% of patients adhering to this regime had a significant lower fecal calprotectin and had microbial and metabolic changes in the same line as patients under successful EEN. This was not seen in those not respecting the diet. Based on those findings, it could be interesting to use autologous feces of successfully treated EEN CD patients for FMT. The group of Schwerd analyzed this possibility using autologous capsule FMT. They concluded that this approach was unsuitable since there was still a to high pathogen burden and a to low microbiota diversity [9].

The Cologne group had a very interesting poster on the follow-up of 2 cases of very early IBD refractory to steroids and antiTNFα treatment. The first patient has ulcerative colitis and is now 3 years in total remission with weekly administered enema of donor stool preparation. The second patient with CD is only in partial remission after one year of follow-up [10].

Combined efforts of scientific researchers and clinicians will further unravel the mystery of the gut microbiota and will eventually bring new ways to treat and to prevent diseases.

Sources

1. Szajewska H, Berni Canani R, Domellöf M, et al. Probiotics for the Management of Pediatric Gastrointestinal Disorders: Position Paper of the ESPGHAN Special Interest Group on Gut Microbiota and Modifications. J Pediatr Gastroenterol Nutr 2023; 76: 232-47
2. De Bruijn C, Zeevenhoven J, Vlieger A, et al. Efficacy of fecal microbiota transplantation in adolescents with refractory irritable bowel: a randomized, double-blind, placebo-controlled trial. J Pediatr Gastroenterol Nutr 2023; 76(S1 Suppl 1): 1-1407
3. Wang YZ, Xiao FF, Xiao YM, et al. Fecal microbiota transplantation relieves abdominal bloating in children with functional gastrointestinal disorders via modulating the gut microbiome and metabolome. J Dig Dis 2022; 23: 482-92
4. El-Salhy M, Winkel R, Casen C, et al. Efficacy of Fecal Microbiota Transplantation for Patients with Irritable Bowel Syndrome at 3 Years After Transplantation. Gastroenterology 2022; 163: 982-94.e14
5. Mahler T, Hoffman I, Smets F, et al. The Belgian consensus on irritable bowel syndrome: the paediatric gastroenterologist view. Acta Gastroenterol Belg 2022; 85: 384-6
6. Hurych J, Mascellani Bergo A, Lerchova T, et al. The faecal microbiome and metabolome changes in Crohn’s disease are associated with decreased mucosal inflammatory activity. J Pediatr Gastroenterol Nutr 2023; 76 (S1 Suppl 1): 1-1407
7. Schwerd S, Häcker D, Siebert K, et al. Exclusive enteral nutrition initiates protective functions in the gut microbiota and metabolome to induce remission in pediatric Crohn’s disease. J Pediatr Gastroenterol Nutr 2023; 76 (S1 Suppl 1): 1-1407
8. Macdonald J, Wilson D, Henderson P, Din S, e Chantges in faecal microbiome and metabolome are more pronounced in Crohn’s disease patients who adhered to the CD-TREAT diet and responded by calprotectin. J Pediatr Gastroenterol Nutr 2023; 76 (S1 Suppl 1): 1-1407
9. Hölz H, Heetmeyer J, Tsakmaklis A, et al . Autologous fecal microbiota transfer in pediatric Crohn ́s disease patients under treatment with exclusive enteral nutrition harbors major challenges - a feasibility test. J Pediatr Gastroenterol Nutr 2023; 76 (S1 Suppl 1): 1-1407
10. Fritz T, Huenseler C, Broekaert I. Safety and efficacy of long-term faecal microbiota transfer in very early onset inflammatory bowel disease. J Pediatr Gastroenterol Nutr 2023; 76 (S1 Suppl 1): 1-1407

Summary
Off
Sidebar
Off
Migrated content
Désactivé
Updated content
Désactivé
Hide image
Off
Congress review Gut microbiota